
Evidence date · 2023-05-03 · Research note 1 of 3
1 2 3
See current Track status →
The immune system changes with age in two related ways. Its responses can become less effective, while background inflammation rises. That combination may leave older adults less able to control infections and less responsive to vaccination. A review published on May 3, 2023, asks whether senolytics — drugs intended to remove cells locked in a stress-related state — could address part of this problem.
The review is not a new human trial, and it does not show that senolytics restore immune function. Its contribution is to connect several lines of early research: studies of senescent cells, small human pilots in age-related disease, infection experiments in mice, and proposed ways to recognize target cells more selectively. The central question is whether clearing harmful cellular signals could improve the immune system without disrupting the useful work that immune and tissue cells also perform.
When a useful repair response lingers
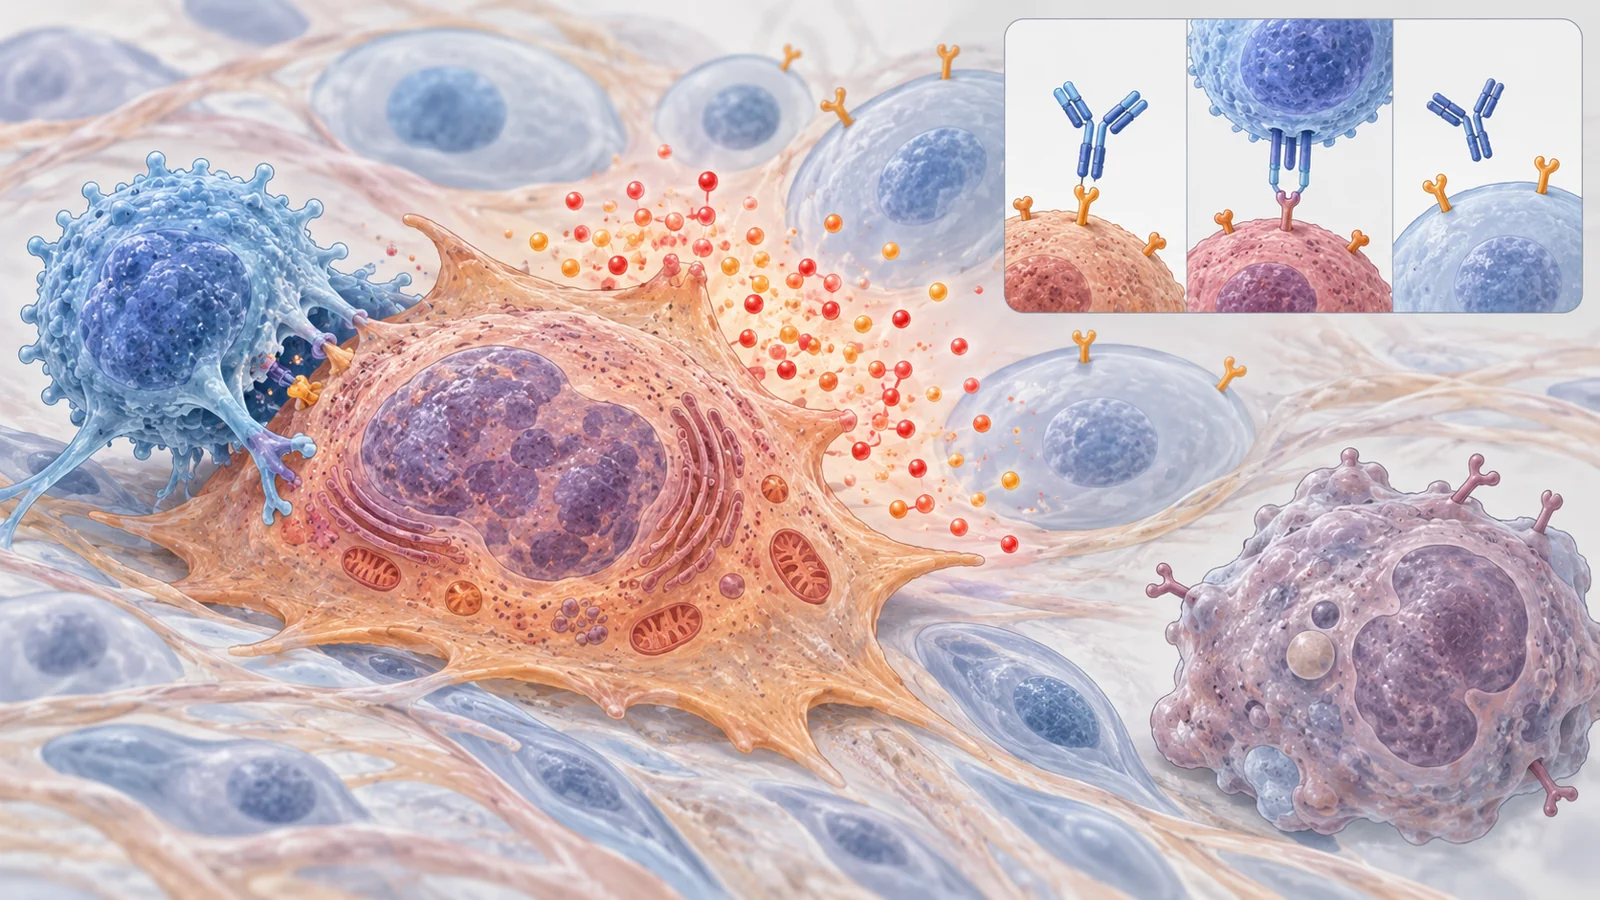
Cellular senescence is a state of stable growth arrest. After stresses such as DNA damage or telomere shortening, a cell can stop dividing and change its behavior rather than immediately dying. Senescent cells may release a mixture of cytokines, chemokines, proteases, growth factors, and other molecules known as the senescence-associated secretory phenotype, or SASP. These signals can influence nearby cells and recruit immune activity.
Senescence is not automatically harmful. In animal models, senescent cells and their signals can help organize tissue remodeling and repair. A short-lived senescence response may therefore be part of a normal recovery process. The problem considered by the review is persistence. As senescent cells accumulate and become harder for the immune system to clear, inflammatory signals may remain active for too long. This can contribute to inflammaging, a state of chronic immune activation associated with weaker innate and adaptive responses.
The immune system is involved on both sides of this process. Senescent immune cells may themselves respond poorly to pathogens or fail to clear damaged material efficiently. Senescent cells in other tissues may release signals that alter immune behavior. Removing senescent immune cells is therefore not the same task as removing senescent fibroblasts or other tissue cells. The location, identity, and function of the target could affect both the possible benefit and the risks of treatment.
Early human studies measured different things
The human evidence discussed in the review does not form a single test of immune rejuvenation. It comes from small studies of different diseases, using different outcomes.
One pilot investigated dasatinib plus quercetin, often abbreviated D + Q, in 14 people with idiopathic pulmonary fibrosis. Participants received intermittent treatment over three consecutive days in three weeks. The study reported a moderate improvement in physical-function testing one and two weeks after treatment. The improvement was also observed several days after drug administration, although the study could not establish how long any benefit lasted.
Other measures moved differently. The pilot did not report improvements in pulmonary function, disease-specific quality of life, or circulating SASP components. Because the study was single-armed and open-label, it had no placebo comparison. The physical-function result could not by itself show that senescent cells had been removed or that immune aging had improved. The review also notes that the absence of a change in circulating SASP markers raises the possibility that any benefit came through mechanisms other than senolysis.
A second pilot treated nine people with diabetic kidney disease with a three-day oral course of D + Q. Eleven days later, the study reported reductions in senescent-cell burden and SASP-related factors. Those are biologically relevant observations, but they are not interchangeable with improved physical function, better organ performance, or greater resistance to infection. A marker change can indicate that a cellular process has shifted without establishing what the patient will feel or what disease outcome will follow.
The review places these pilots alongside a different kind of result. In a phase II randomized controlled trial involving 177 people with knee osteoarthritis, the senolytic candidate UBX0101 did not improve pain compared with placebo. The disease, drug, endpoint, and study design differed from the D + Q pilots, so the findings should not be pooled into a broad verdict about senolytics. Together, however, they show why the field needs to separate physical performance, molecular or cellular markers, symptoms, organ function, and immune outcomes rather than treating them as equivalent evidence.
What infection experiments add
Animal infection studies make the immune-aging hypothesis more specific because they examine what happens after exposure to a pathogen. They still do not establish protection in humans, but they can reveal how senescent cells might alter an immune response.
In one set of experiments discussed by the review, older mice treated with fisetin, D + Q, or genetic removal of senescent cells had approximately half the mortality of untreated mice after exposure to common pathogens. The work proposed that senescent cells can act like an inflammation amplifier or rheostat. Older animals may begin with more inflammation and then mount an exaggerated response to infection, producing more tissue damage.
The model has important limits. The coronavirus experiment used mouse hepatitis virus A59, which is related to SARS-CoV-2 but is not the human virus. A result in that system can motivate research into the biology of infection without establishing that a senolytic would protect older people from COVID-19 or any other human respiratory infection.
A separate experiment used a sublethal influenza infection in mice to examine immune-cell behavior. In older mice, regulatory T cells marked by FoxP3 were more prevalent in the lungs, and levels of transforming growth factor beta were higher in airway samples. Treating the mice with D + Q reduced both FoxP3-expressing cells and transforming growth factor beta, while shifting T-cell differentiation toward a type associated in the study with healing and restoration of balance. The aged response became more similar to the response of younger mice in the tested model.
Survival and immune-cell behavior answer different questions. A survival result suggests that removing senescent cells may change the severity of an infection in an animal model. The influenza findings offer a possible explanation involving tissue immune regulation. Neither result demonstrates that older humans would fight infections more effectively after treatment, and neither establishes that the same immune changes would be safe or beneficial across pathogens.
Clearing the wrong biology can create new problems
A senolytic intended to remove harmful cells has to contend with two kinds of unwanted effect. The first comes from senescence itself. Cells in this state can support wound repair and tissue remodeling when their activity is temporary. In mouse models, limited SASP exposure helped neighboring cells become more plastic during regeneration, while prolonged exposure and abnormal clearance were associated with tumor formation. Removing every senescent cell indiscriminately could therefore interfere with useful repair functions.
The second problem comes from the treatment. Existing drugs may affect cells that are not senescent or may interfere with immune pathways. Dasatinib, for example, was associated with cytomegalovirus reactivation in a group of leukemia patients after hematopoietic stem-cell transplantation. The review describes this as a setting where the drug’s effect on immune function could be observed directly. Other compounds, including quercetin, fisetin, and navitoclax, had not been associated with the same viral-reactivation pattern in the evidence discussed, so one drug’s risk should not be generalized to the entire class.
Off-target toxicity is also compound-specific. Dasatinib and quercetin have been linked to adverse effects in human studies; the review particularly associates fluid retention and suppression of blood-cell production with dasatinib. Navitoclax inhibits BCL-xL, a protein involved in the survival of both senescent cells and platelets. Earlier clinical work with navitoclax recorded substantial low platelet counts, although bleeding was limited in the cited study. A therapy designed to improve immune defenses could therefore produce competing biological effects if it alters blood cells or immune signaling too broadly.
Targeting senescent cells more precisely
One response to these problems is to improve the way target cells are recognized. Current senolytics generally aim to exploit vulnerabilities shared by senescent cells, regardless of their tissue or immune-cell identity. A more selective approach would try to recognize a surface feature enriched on the relevant senescent population and spare healthy cells.
The review discusses CD26 as one possible example. Activity of the senescence-associated enzyme beta-galactosidase helped lead researchers to CD26, a surface protein found at higher levels on peripheral blood mononuclear cells from older people in the cited work. Antibodies against CD26 selectively removed CD26-expressing cells in cell experiments through antibody-dependent cellular cytotoxicity, and related targeting had been explored in mouse cancer models. The evidence does not establish that CD26 uniquely identifies harmful senescent immune cells in people. It shows how a surface marker might become a starting point for a more directed strategy.
Engineered immune cells offer a different design. Instead of giving a small molecule that enters the body and acts through several molecular targets, researchers can program a T cell to recognize a chosen surface protein. In a proof-of-principle study described by the review, CAR T cells directed against the urokinase-type plasminogen activator receptor, or uPAR, eliminated senescent cells and reduced liver fibrosis and damage in mice. Here, the engineered T cells were being used to remove senescent tissue cells; the approach was not a demonstration that senescent immune cells had been safely cleared in humans.
uPAR is also present at low levels in some healthy tissues, including bronchial epithelium. That makes target selection a safety problem as well as an engineering problem. An antibody or CAR T cell must recognize enough of the intended population to be useful while avoiding healthy cells that share the marker. The same principle applies when the desired target is a senescent immune cell rather than a senescent cell in an organ. Location, marker density, immune context, and the duration of cell removal could all shape the outcome.
What this could change
The most concrete future use raised by the review is preparation for vaccination. Older people can have lower antibody levels and weaker vaccine-specific T-cell reactivity, so a treatment given before vaccination might, in principle, reduce the inflammatory or cellular conditions that blunt the response. The proposed pathway is straightforward: remove or suppress harmful senescent-cell activity, allow a more favorable immune response to develop, and potentially improve later protection against infection.
That remains a research possibility, not an established clinical benefit. Human studies would need to show that a pre-vaccination senolytic actually improves vaccine responses in older adults while avoiding viral reactivation, blood-cell toxicity, unwanted loss of useful repair functions, and other off-target effects. If those conditions are met, senolytics could become a way to prepare an aging immune system for vaccination rather than a general promise to reverse aging. The review’s significance lies in defining that possibility clearly and showing why immune aging demands evidence about both cellular clearance and the quality of the resulting defense.
Key Sources
- Primary source: The ageing immune system as a potential target of senolytics.
DOI or Journal Page · Review or Meta-Analysis · 2023-05-03