
Evidence date · 2025-03-20 · Research note 2 of 2
1 2
See current Track status →
Since the previous research note · Earlier expectation not tested
Track continuity
Since the previous research note: How MEDI5752 directs CTLA-4 blockade toward activated T cells with PD-1
Previous expectation: A more selective dual-checkpoint antibody might deliver clinical benefit with acceptable safety for people with advanced cancer.
What this study adds: The 2025 review explains the wider rationale for pairing PD-1/PD-L1 and CTLA-4 blockade and makes broad claims about response. It does not supply a test of MEDI5752's selectivity, dose, benefit, or safety forecast in the provided abstract.
What changed in this study
Some cancers respond poorly to treatment that blocks a single immune checkpoint, one of the restraints on immune activity. A 2025 mini review describes why researchers are exploring antibodies aimed at two checkpoints: PD-1/PD-L1 and CTLA-4. T cells are immune cells involved in responses against cancer. Blocking these checkpoints at different stages as T cells become active may strengthen that response. Whether that approach improves outcomes for patients is a separate question from whether an antibody can recognize both targets.
One antibody can recognize two targets
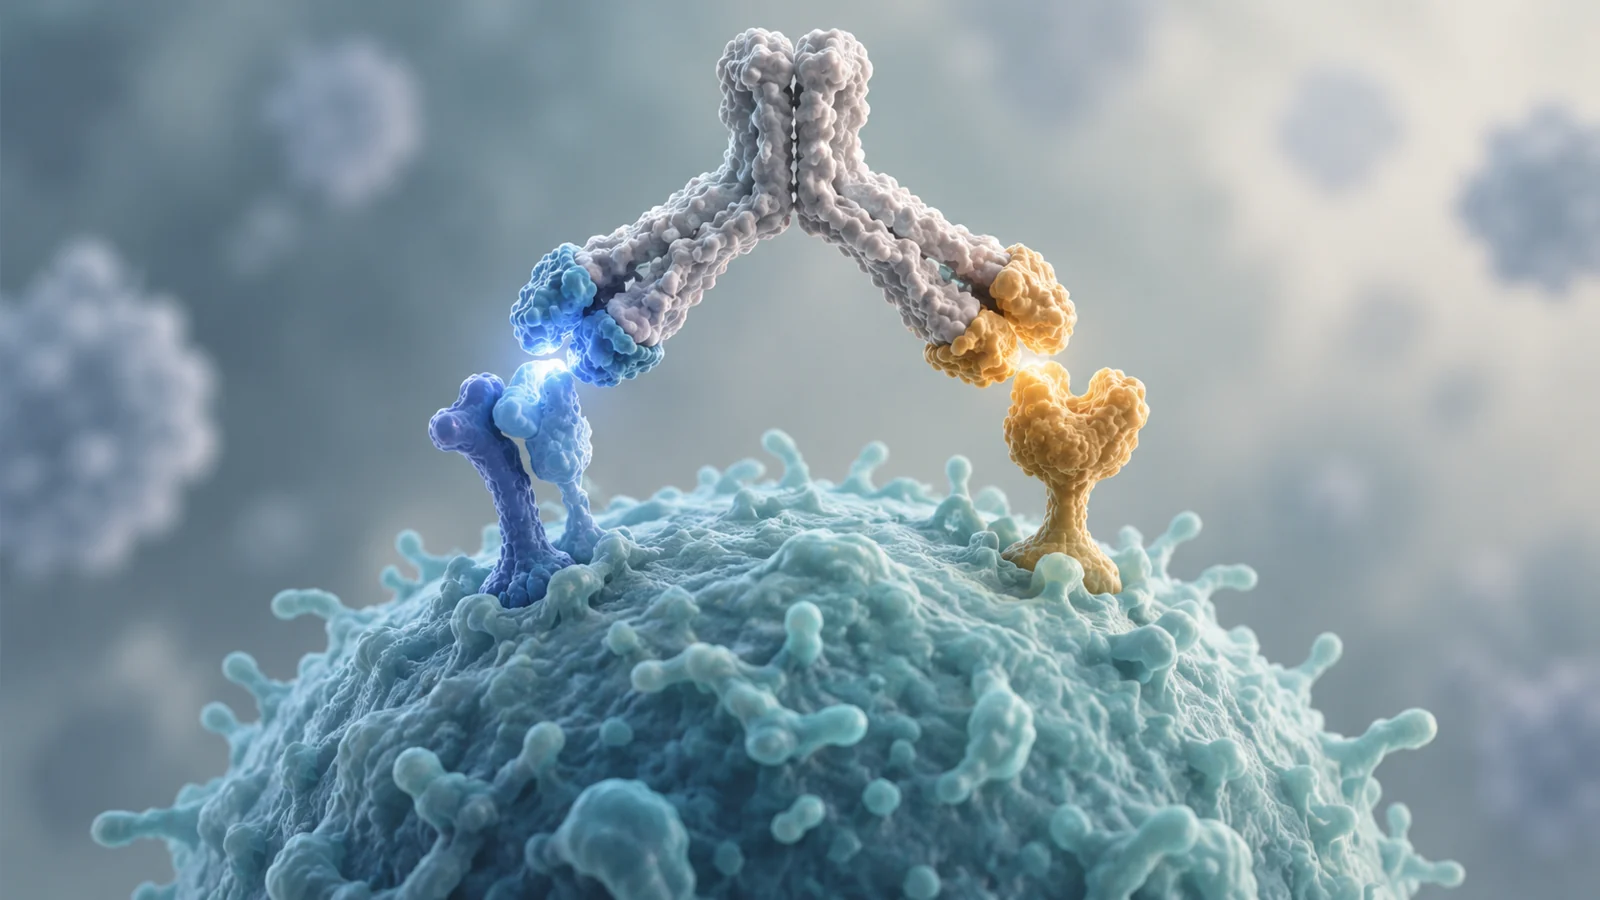
A bispecific antibody can recognize two different molecular targets, or two separate sites on one target. That two-target recognition is a feature of the antibody; by itself, it does not show that treatment works better or is safer.
The review discusses bispecific antibodies alongside immune checkpoint inhibitors, which block signals that restrain immune activity. Its central pairing is PD-1/PD-L1 and CTLA-4. The authors describe these checkpoints as acting at different phases of T-cell activation. Their rationale is that blocking both could affect immune activity at more than one phase, potentially increasing responses against cancer cells.
What the review’s clinical claims can tell us
The authors say bispecific antibodies have shown better clinical results than monoclonal antibodies, which are designed around one target, and argue that combining checkpoint inhibition may increase response rates and antitumor effects. These are broad claims in the supplied abstract. It gives no effect sizes, named patient groups, or adverse-event rates to show how large or consistent any difference is, or how safety compares.
The evidence here therefore supports the rationale for studying dual targeting, but it cannot establish an optimal dose or benefit for a particular cancer type. The review does not itself test this two-target strategy in patients. The promise rests on a biological strategy; its value for patients depends on results from studies that can demonstrate reproducible benefit and acceptable safety.
What two-target antibodies could change in cancer care
For people whose cancers respond poorly to single-checkpoint inhibition, an antibody that targets both PD-1/PD-L1 and CTLA-4 could eventually offer another way to activate an antitumor response. That option would matter if patient studies show that the approach works consistently and its safety is acceptable. The review gives researchers a reason to investigate the pairing, while leaving those clinical conditions to be established.
Key Sources
- Primary source: Bispecific antibodies (bsAbs) directed against PD-1/PD-L1 and CTLA-4; a mini review.
DOI or Journal Page · Review or Meta-Analysis · 2025-03-20