
Evidence date · 2024-12-11 · Research note 1 of 3
1 2 3
See current Track status →
Regenerative treatments built from mesenchymal stromal cells, often called MSCs, face a practical contradiction. These cells help maintain tissues, can differentiate into several cell types and regulate immune responses. Yet a treatment may require a large supply. The review notes that regenerative protocols may need roughly one to two million cells per kilogram of body mass, while MSCs can be scarce in their native niches. Expanding them in culture helps solve the supply problem, but prolonged culture can weaken the very functions that make them useful.
That is why cellular senescence matters in cell therapy. Senescence is a stress-linked state in which a dividing cell enters a prolonged, generally irreversible arrest of the cell cycle while also changing its metabolism and secretions. A review published on December 11, 2024, surveys attempts to delay or alter this state in MSCs. Its practical question is not simply whether cells can be made to look younger under a microscope. It is whether enough cells can be prepared while retaining the functions a therapy needs, with risks that can be controlled.
Why expansion can work against the cells
Culture is not a neutral holding environment. As MSCs undergo repeated divisions and encounter stresses such as nutrient limitation, hypoxia or oxidative damage, their appearance and behavior can change. The review describes increased senescence-associated beta-galactosidase activity and persistent expression of proteins such as p53, p21 and p16. Surface markers associated with MSC identity and function, including STRO-1, CD106 and CD146, can also decline during senescence.
These measurements are useful clues, but the practical problem is functional. Senescent MSCs may proliferate less, differentiate less effectively, migrate less efficiently and show altered immune-regulating activity. The review also connects long-term culture with reduced alkaline phosphatase and osteocalcin expression, alongside less efficient bone formation. A lower level of one marker would therefore not demonstrate that every relevant function has been restored.
The tension is especially important because expansion is part of preparing a therapy, not a side issue after the biology is settled. Cells from older donors already tend to show reduced proliferation, differentiation capacity and stemness compared with cells from younger donors. The more extensively a population must be expanded, the more carefully its functional state has to be monitored.
How a stressed cell changes its neighborhood
One connected pathway begins with reactive oxygen species, or ROS. Small amounts of ROS normally participate in cellular signaling. Excess ROS, however, can damage DNA and disrupt the systems that repair or limit that damage. The review describes a feedback loop in which accumulating oxidative stress pushes MSCs toward senescence, while senescent cells produce more ROS and become still more vulnerable to molecular injury.
Mitochondria add another layer to the problem. Their dysfunction can disturb the cell’s energy balance, while insufficient mitophagy allows damaged mitochondria to remain in the cell. The review links defective clearance of these mitochondria with further metabolic stress and ROS accumulation. Changes involving PARKIN, sirtuins and energy-related signaling are discussed as parts of this broader interaction rather than as a single switch that determines whether an MSC is healthy or senescent.
The consequence is more than slower division. Senescent cells can develop a senescence-associated secretory phenotype, known as SASP. This involves the release of inflammatory and tissue-remodeling signals, including cytokines and growth-related factors. In MSCs, the secretory pattern can shift from an anti-inflammatory profile toward a more inflammatory one, changing how the cells interact with nearby tissue.
That shift matters because MSCs may produce therapeutic effects through paracrine signaling as well as through their presence at an injury site. The review notes that their survival after systemic administration can be very limited, while the factors they release can influence other cells. A cell that remains alive but sends a changed set of signals may therefore be functionally different from the intended treatment cell.
Three interventions change different things
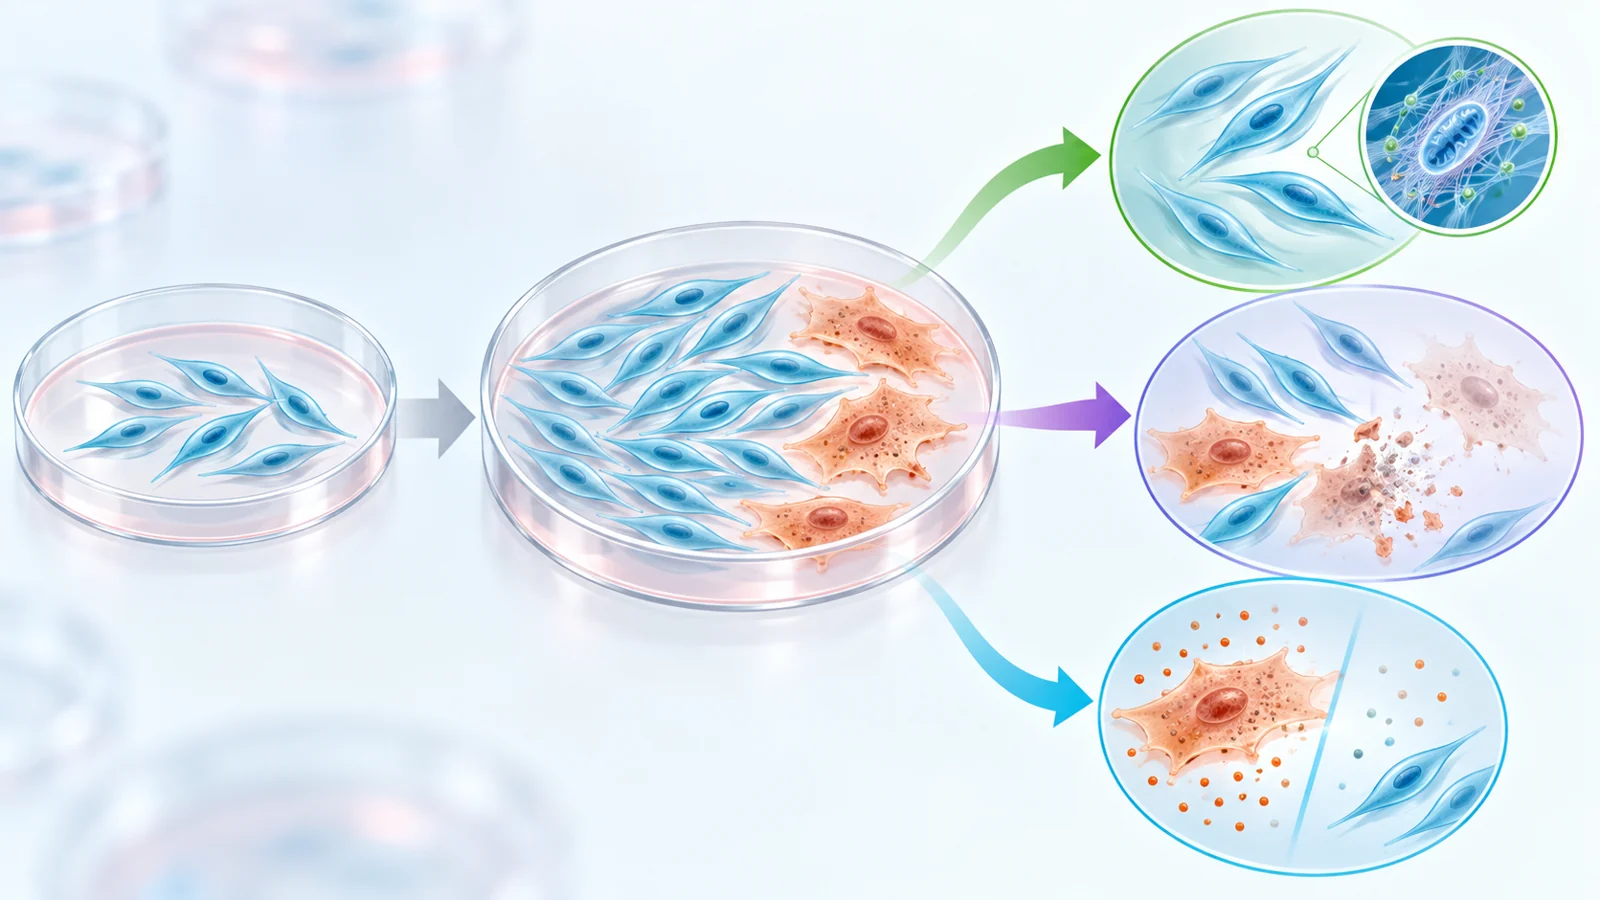
The review describes several strategies for dealing with this problem, but they should not be treated as interchangeable forms of rejuvenation. Some approaches try to preserve or restore cellular function. Others eliminate cells that have entered a harmful state. A third group changes what those cells secrete.
Mitochondria-targeting and antioxidant approaches belong to the first category. Melatonin is one example discussed in the review. In murine models, melatonin-treated senescent MSCs were reported to support better ischemic recovery and new blood-vessel formation than untreated controls. The review connects this result with reduced ROS accumulation, increased SIRT1 expression and activation of mitophagy. This is evidence of improved function in a mouse setting; it does not show that the same cells have been completely returned to a youthful state or that patients would receive the same benefit.
Senolytics pursue a different result. These agents are intended to eliminate susceptible senescent cells, often by promoting apoptosis through pathways involving the BCL-2 family. The review discusses examples such as dasatinib, quercetin and fisetin in studies of different cell types. Removing a senescent cell is not the same as repairing that cell. It changes the composition of the cell population and may leave a different group of surviving cells to provide the treatment.
Senomorphics take another route by suppressing the SASP. The cell remains present, but its inflammatory output is reduced. This could be relevant when the MSC secretome contributes to the intended therapeutic effect, yet the altered secretions of senescent cells are harmful. The tradeoff is that SASP suppression may require continuing exposure, potentially creating different side-effect concerns from an intermittent senolytic treatment.
Preserving function, eliminating selected cells and changing inflammatory secretion are therefore three different biological achievements. A reduction in senescence markers, a smaller senescent-cell population or a quieter secretome does not independently establish complete reversal of cellular aging. The relevant outcome depends on which cells remain, what they do and whether that behavior matches the intended use.
More antioxidant activity is not automatically better
The review also highlights why these strategies cannot be optimized by simply maximizing a biochemical change. ROS are not only damaging by-products. At low intrinsic levels, they can support normal signaling and processes such as bone-forming differentiation. Excessive removal of ROS may interfere with differentiation, suppress adipogenic potential or even promote a senescent state in proliferating cells.
Some SIRT1-directed approaches illustrate a related constraint. Resveratrol or NAD-based strategies were reported to improve stemness-related properties in early-passage MSCs and rescue some impairments in senescent cells, but the review notes that these effects may require high concentrations or prolonged exposure. The concentration and duration of treatment are part of the biological result, not merely technical details.
This evidence concerns controlled treatment of cells or experimental models. It does not support taking melatonin, resveratrol, NAD or an antioxidant supplement to rejuvenate MSCs in a person. A laboratory exposure that changes a cultured cell population cannot be translated into a personal treatment recommendation without evidence about delivery, dose, safety and clinical effect.
Translation depends on control and safety
Senescence itself has a protective role. By stopping damaged cells from continuing through the cell cycle, it can help limit tumor formation. Any intervention that weakens this safeguard, changes growth control or removes a damaged-cell response could create an oncogenic concern. The review identifies possible oncogenesis as an important off-target risk, but this is a safety issue to investigate, not a reported cancer incidence caused by the approaches discussed.
Cell heterogeneity creates a separate obstacle. MSCs can come from different tissues, donors and culture conditions, and the review emphasizes that this variation limits standardization. Findings involving bone-marrow MSCs, adipose-derived MSCs, mouse cells or a particular experimental exposure cannot automatically be assumed to apply across all MSC sources and therapeutic goals.
The review brings together cell experiments, animal models and references to clinical-trial work involving different agents and biological settings. Those categories are not interchangeable. An existing approval for a drug, or a clinical reference involving MSCs, does not establish approval or efficacy for a treatment designed to suppress or reverse MSC senescence. From the December 2024 perspective, the field still needs interventions that are safe, reproducible, effective and tunable, with patient benefit demonstrated in the relevant treatment context.
What more reliable cell therapies could offer patients
More dependable MSC preparations could make future regenerative treatments more useful. The potential benefit is practical: producing enough cells while retaining their tissue-supporting, differentiation-related and immune-regulating functions could make a cell therapy more consistent from preparation to treatment.
That outcome remains conditional on controlling the biology safely and reproducibly across cell sources, manufacturing conditions and intended uses. It also depends on showing that preserved function translates into meaningful benefit for patients. The prospect is not evidence that these approaches extend human lifespan; it is the possibility of making cell-based repair therapies more reliable when the remaining safety and translation problems are solved.
Key Sources
- Primary source: Suppressing the Aging Phenotype of Mesenchymal Stromal Cells: Are We Ready for Clinical Translation?
DOI or Journal Page · Review or Meta-Analysis · 2024-12-11