
Evidence date · 2025-07-15 · Research note 3 of 3
1 2 3
See current Track status →
Since the previous research note · Earlier expectation not tested
Track continuity
Since the previous research note: What the TIGIT immune brake reveals in myeloma and other blood cancers
Previous expectation: TIGIT blockade might help people with blood cancers if its immune effects translated into safe clinical benefit.
What this study adds: This July 2025 review examines solid tumors and places disappointing human monotherapy results beside combination signals and antibody-design questions. Its stated study selection excludes blood cancers.
What changed in this study
Some anti-TIGIT antibodies slowed tumors in mice, especially when paired with another checkpoint treatment. In people, however, treatment aimed at TIGIT alone produced disappointing results, and combination trials have not delivered a uniform answer. One design choice may help explain the gap: an antibody can block TIGIT, but its other end can also recruit immune cells that may remove the very cells the treatment is meant to help.
TIGIT is a receptor on immune cells that helps dampen their activity. Blocking it is intended to ease that restraint. A July 2025 review brings together animal studies, human trial reports and mechanistic research to examine why that simple aim can lead to different outcomes. The review does not report a new treatment trial; its evidence spans different antibodies, tumor models, patient groups and comparisons.
Two immune brakes meet at an activating signal
TIGIT is not simply another version of PD-1, a better-established immune checkpoint. Both can restrain immune responses, and cancer-fighting T cells may carry both receptors. But their internal signaling differs. PD-1 can directly dampen signals that a T cell uses to activate itself. TIGIT has a more indirect effect, and its influence on those activation signals appears smaller and more nuanced.
A point of overlap is DNAM-1, an activating receptor on immune cells. The review describes evidence that TIGIT and PD-1 can each interfere with DNAM-1 activity. Their different signaling routes may therefore converge on an activation pathway, providing a rationale for testing the two blockades together.
That provides a rationale for pairing TIGIT blockade with PD-1 blockade. In a test of T cells outside the body, blocking both checkpoints restored their activity better than blocking PD-1 alone; mouse studies also often found stronger tumor effects from combinations. The rationale does not guarantee that adding a second antibody will help every tumor or patient. It does suggest why a weak result from TIGIT treatment alone may not settle the question of what it can do in a combination.
The antibody’s tail can recruit help or create risk
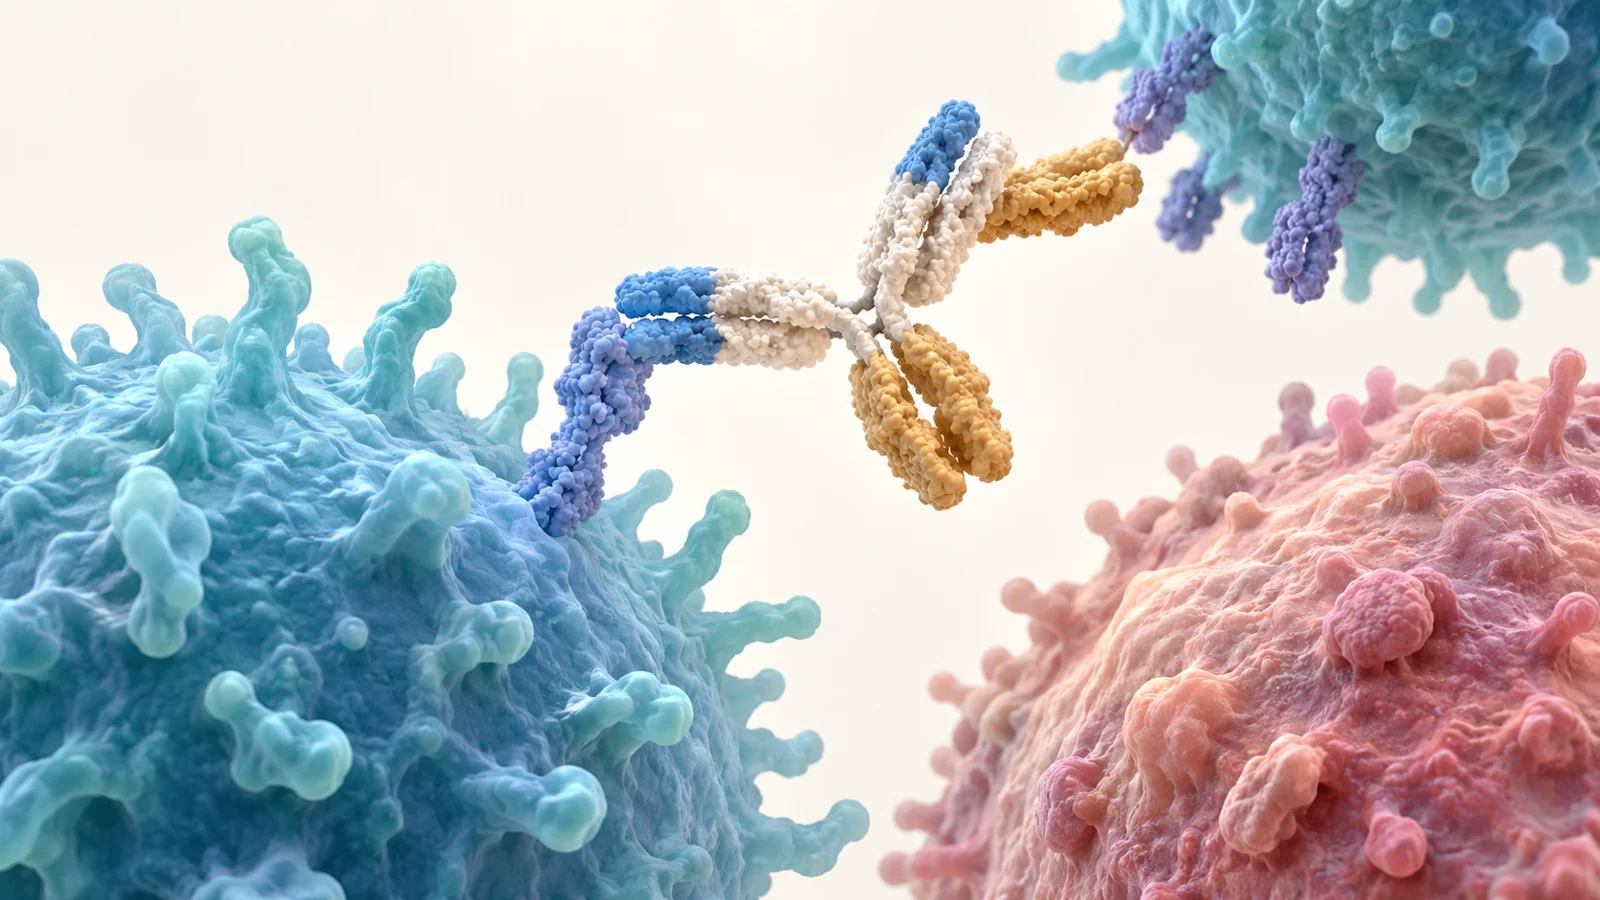
An antibody has a binding end that recognizes its target and an Fc region, or tail, that can interact with other immune cells. Depending on its design, that tail may recruit cells such as monocytes or natural killer cells. Those recruited cells can add effects beyond simply blocking TIGIT: some studies suggest they may help present tumor material to the immune system or remove regulatory T cells that suppress immune responses.
In mouse tumor models, anti-TIGIT antibodies with a functional Fc region often produced stronger tumor control than versions with reduced or disabled Fc activity. A matched comparison using the same TIGIT-binding antibody illustrates the point: both versions blocked TIGIT, but only the version with a functional mouse Fc showed efficacy in the MC38 colon cancer model. The review attributes that added effect to myeloid cells, which include monocytes and other immune cells.
The same extra activity creates a design concern. TIGIT is carried by immune cells that may already be exhausted from prolonged activity against a tumor. An Fc-active antibody could recruit other cells to attack TIGIT-bearing cells, potentially removing some of the cells that blockade is supposed to release. In short, a stronger immune-recruiting tail might help in one setting and undermine the goal in another.
This helps explain why the mouse-to-human comparison is difficult to interpret. Many mouse studies relied on Fc-active formats and treatment of smaller or earlier tumors. Human trials have often used IgG1 antibodies with functional Fc regions, while the review notes that human and mouse Fc behavior does not translate in a simple one-to-one way. The authors argue that future work should compare Fc-active and Fc-silent formats directly and make clear whether an antibody’s effect comes from blocking TIGIT, recruiting other immune cells, or both. These comparisons do not show that Fc activity caused any particular clinical failure, nor that Fc-silent antibodies will reliably succeed.
Early trial promise met a harder test
The clearest example of an encouraging combination result followed by a setback is tiragolumab. In the phase 2 CITYSCAPE trial in non-small cell lung cancer, 31% of patients receiving tiragolumab plus atezolizumab had an objective response, compared with 16% receiving atezolizumab plus placebo. An objective response means that a tumor shrank enough to meet the trial’s response criteria. The comparison favored the combination, but a response rate is not the same as showing that patients live longer.
The result helped support a larger phase 3 study, SKYSCRAPER-01. In 2024, Roche announced that it had not met its primary goal. That outcome shows why an early response-rate difference cannot by itself establish a lasting clinical advantage. It also leaves open questions about which patients, tumors and treatment settings might benefit from adding TIGIT blockade.
Vibostolimab offered another mixed picture. In a phase 1 study, the monotherapy group had a 0% objective response rate. The combination with pembrolizumab showed more activity, with the review describing stronger tumor-growth reduction among patients whose tumors were PD-L1 positive. Responses were more frequent in previously untreated non-small cell lung cancer than in a group whose disease had resisted prior PD-1 or PD-L1 treatment; the refractory group had a 3% response rate. Later, Merck announced that the KeyVibe-003 and KeyVibe-007 trials had failed, and development of vibostolimab was discontinued.
These results do not tell a single story of success or failure. The monotherapy finding was weak, some combination results were more encouraging, and later trials still failed to establish the hoped-for benefit. The review also describes Fc-silent domvanalimab, which was being studied with the PD-1 antibody zimberelimab. An ARC-10 update reported a 31% reduction in the risk of progression or death compared with zimberelimab alone. The review says enrollment was discontinued in 2024 as the developers prioritized other late-stage trials focused on gastrointestinal cancers, rather than citing lack of activity. This update is a trial comparison, not proof of a general survival benefit across solid tumors.
The right setting may matter as much as the target
The review finds reasons to look beyond a single overall result. In the vibostolimab study, the combination reduced tumor growth more among patients who were PD-L1 positive; responses were also more frequent in previously untreated lung cancer than in disease that had resisted prior PD-1 or PD-L1 treatment. These observations make treatment setting and patient selection important questions, but they do not validate PD-L1 as a universal test for deciding who should receive TIGIT blockade.
Another possible selection clue is PVR, a molecule that interacts with TIGIT. The review identifies tumor PVR as an unresolved question: it is not yet clear whether high PVR in a tumor reliably predicts greater benefit from anti-TIGIT treatment. Measuring it could help clarify why responses differ, but the evidence reviewed does not establish it as a clinical selection test.
The review searched published literature and trial registries, traced references, and included some recent abstracts, news reports and company announcements. It focused on solid tumors and excluded blood-cancer studies. Its comparisons therefore draw on evidence gathered in different ways, across different tumor types, antibody designs, trial phases and control groups. The findings are useful for understanding the field’s competing explanations, but they are not a single controlled test of which antibody design or patient group will benefit most.
What better TIGIT combinations could offer patients
A carefully designed TIGIT blocker could eventually add another option to existing checkpoint treatment for selected people with solid tumors. The route to that possibility runs through controlled trials that show the added treatment improves meaningful outcomes, while keeping immune-cell harms acceptable for the cancer and patient group being treated. Better evidence on antibody Fc design and on who benefits would help determine whether that added option is real.
Key Sources
- Primary source: Anti-TIGIT therapies: a review of preclinical and clinical efficacy and mechanisms.
DOI or Journal Page · Review or Meta-Analysis · 2025-07-15