
Evidence date · 2023-02-10 · Research note 1 of 2
1 2
See current Track status →
Sleep is often discussed in relation to the brain’s visible size or to dementia risk. This study asked a more fine-grained question: among older adults without dementia, were earlier sleep patterns related to subtle features of brain tissue even when conventional measures of brain volume and cortical thickness were not?
The answer was partly yes, but not in one simple pattern. Worse reported sleep quality was associated with several diffusion-based measures of white-matter and amygdala tissue, with some associations stronger among men. Sleep duration showed no significant association across the whole group after correction for multiple comparisons, yet shorter and longer sleep reported years earlier were associated with selected later imaging measures among women. The findings are informative about possible differences in how sleep and brain aging relate, but they do not establish different sleep prescriptions for men and women.
The study looked beneath brain size
Researchers used data from the Rancho Bernardo Study of Healthy Aging, a long-running community cohort. The final sample included 146 adults who were free of dementia when they underwent MRI in 2014–2016. Participants were an average of 76.7 years old at imaging, with a broad age range from 56 to 99.
The sleep-quality and sleep-duration analyses did not involve exactly the same people. Sleep quality was available for 117 participants, while 143 had usable sleep-duration data. That distinction matters when interpreting the results because the reported associations came from related but different groups and from sleep measurements taken at different stages of life.
The researchers examined brain volume, cortical thickness and a set of restriction spectrum imaging measures. The conventional size measures were not significantly associated with the earlier sleep patterns examined. The sleep-related differences appeared instead in measures designed to be sensitive to tissue organization and water movement within the brain.
Sleep was measured long before the scan
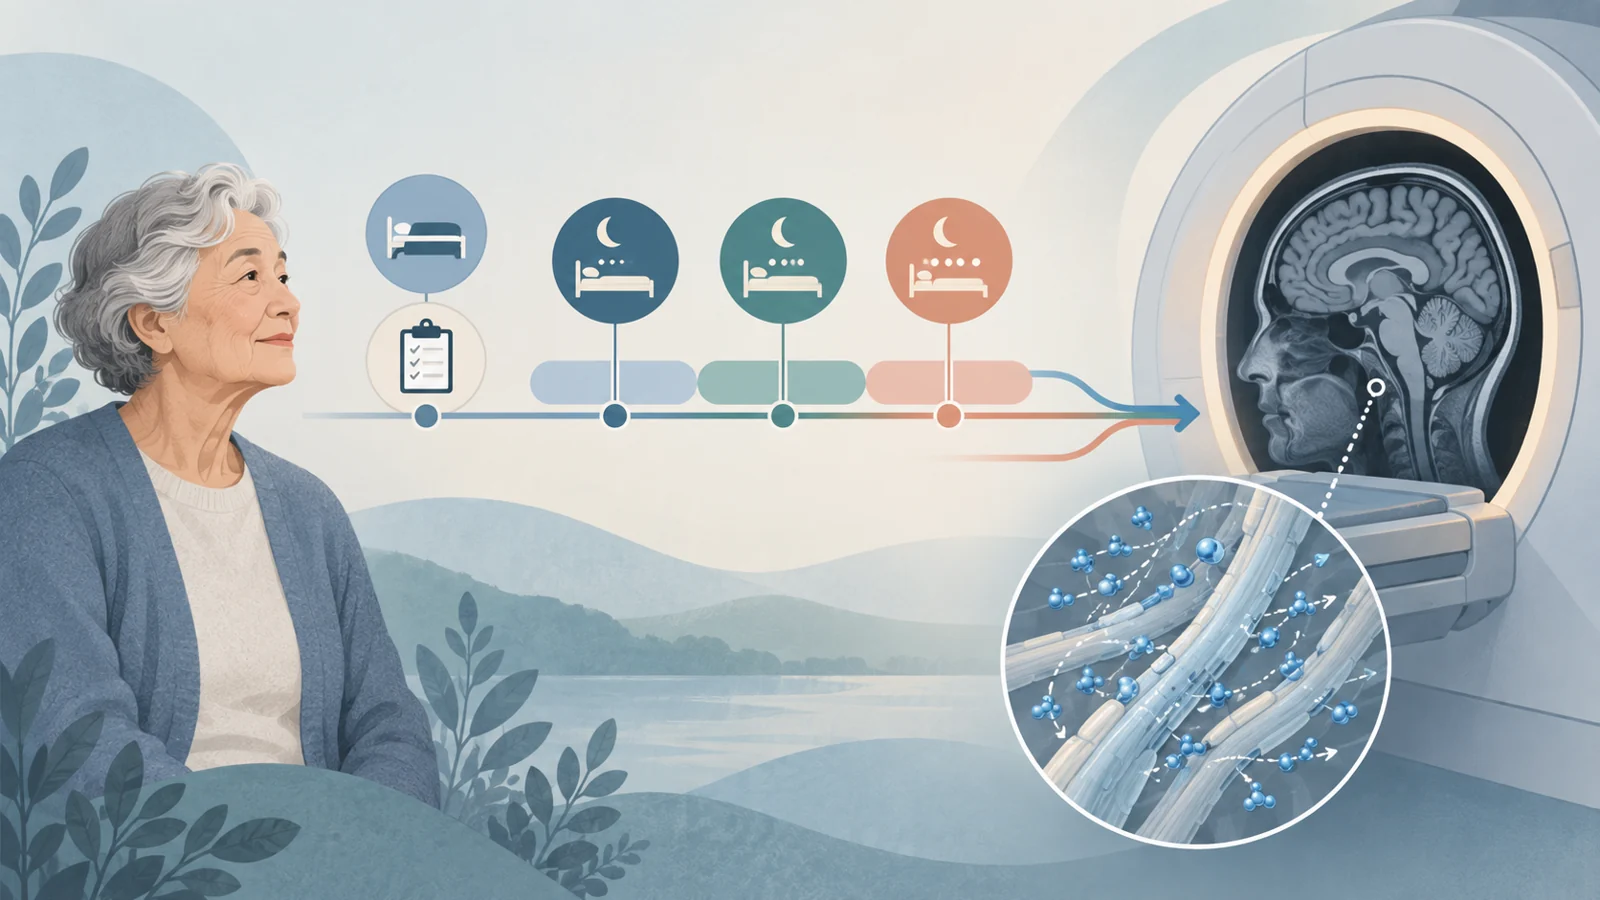
Sleep quality came from a 2008 questionnaire about participants’ general sleep habits during the preceding month. Its score combined several aspects of sleep, including perceived quality, time needed to fall asleep, sleep efficiency, disturbances, medication use and daytime dysfunction. Higher scores represented worse sleep quality. On average, this assessment occurred about 6.3 years before the MRI.
Sleep duration came from reports of nightly sleeping hours collected across visits between 1984 and 2009. To make the estimates more stable, the researchers grouped the reports into three approximate periods: 25 years, 15 years and 9 years before imaging. These were not continuous recordings of sleep. They were participants’ recollections or reports at research visits, summarized into longer-term time periods.
This timeline gave the study a useful feature. Sleep was assessed before the scan, sometimes decades before it, rather than at the same moment as the brain measurement. It also created an important interpretive complication: sleep duration was measured at substantially different ages from sleep quality. The earlier duration periods included more participants in midlife and later midlife, whereas the quality questionnaire was completed when participants were older.
The MRI therefore provided one later snapshot in relation to several earlier sleep reports. It did not show how an individual’s brain changed from one scan to the next.
MRI picked up water movement in tissue
Restriction spectrum imaging models how water moves through different compartments within a voxel, the small three-dimensional units used to represent an MRI scan. In this study, the measures included restricted isotropic diffusion, neurite density and isotropic free-water diffusion.
Restricted isotropic diffusion reflects non-oriented restricted movement and is used as an indirect measure of diffusion within cell bodies. Neurite density reflects restricted, oriented movement associated with neurites, including axons and dendrites. Free-water measures estimate more freely moving water in spaces such as interstitial or cerebrospinal fluid compartments.
Among participants with sleep-quality data, worse sleep quality was associated with lower restricted isotropic diffusion in global white matter and several white-matter tracts. It was also associated with lower neurite-density measures in selected regions and higher free-water diffusion in the amygdala. Some of these relationships remained after adjustment for education, alcohol intake, smoking, physical activity, hypertension, body mass index and depression.
These measures can be sensitive to changes in tissue organization, and the paper discusses possibilities such as cell shrinkage, demyelination or loss of axons and dendrites. But the diffusion patterns themselves do not directly demonstrate any one of those cellular events in these participants. They are indirect measurements that help identify differences in tissue properties, not a microscopic diagnosis.
Quality and duration pointed in different directions
The sleep-quality findings were not uniform across the sexes. After interaction tests and sex-stratified analyses, selected associations were evident among men, including relationships involving free water in the cingulum and a nonlinear pattern in hippocampal measures. The broader result was that poorer sleep quality showed stronger associations with abnormal microstructure for men in some analyses, rather than producing one consistent male-versus-female difference across every imaging measure.
Sleep duration followed another pattern. When the researchers analyzed the whole cohort, duration did not significantly predict the examined microstructure measures after the study’s multiple-comparison corrections. The more specific pattern emerged after testing whether sex changed the association. Among women, both shorter and longer sleep durations reported approximately 25 and 15 years before MRI were associated with lower restricted isotropic diffusion in white matter and higher free-water measures in selected areas, including the thalamus and white matter. There was no significant interaction between sex and sleep duration at the approximately 9-year assessment period.
In the women’s data, the imaging pattern was most favorable around 7–8 hours of nightly sleep. That range should not be read as a universal target from this study. It describes the shape of an association within one observational sample, measured at particular points in participants’ lives. It also does not mean that sleeping a specified number of hours would prevent tissue changes or dementia.
The timing makes the sex pattern harder to read
It may be tempting to turn the results into a simple message: women need the right number of hours, while men need better sleep quality. The study cannot support that conclusion because the two sleep exposures were not measured on the same schedule.
Sleep quality was assessed when participants were about 70 years old on average. The duration estimates associated with later imaging came from periods when participants were younger, including an average age of about 54 at the earliest period and about 63 at the middle period. The authors discuss hormonal changes around the menopausal transition as one possible factor that could have influenced sleep disruption during those earlier years, but the study did not test that explanation directly.
The unequal timing also affects what the sex interactions mean. A difference observed for sleep duration in earlier adulthood may reflect a different life stage, health context or exposure history from a difference observed for sleep quality in later life. The results encourage more precise questions about when sleep patterns matter and for whom; they do not yet separate the biological explanation from the timing of measurement.
What the design can and cannot tell us
The study’s observational structure leaves several possibilities open. Poor sleep could contribute to later tissue differences, but early changes in health or brain function could also influence sleep. Earlier sleep measurements reduce some of the ambiguity about which came first, yet they do not eliminate a bidirectional relationship.
A single MRI occasion cannot establish within-person tissue loss, its rate, or a sequence in which microstructural differences appear before visible shrinkage. The lack of an association with brain volume or cortical thickness also should not be treated as proof that one type of brain change occurs before another. The size measures and diffusion measures capture different properties, and neither provides a complete account of brain aging on its own.
The sleep data were self-reported, and the researchers did not account for obstructive sleep apnea, which can affect sleep quality and may have sex-dependent relationships with cognition. The sample was also relatively small and predominantly highly educated and non-Hispanic White, limiting how confidently the subgroup findings can be generalized. Multiple regions, measures and time periods were tested, making the correction procedures important for distinguishing stronger findings from chance patterns.
For these reasons, the paper supports a careful interpretation: sleep habits were associated with later differences in selected tissue-sensitive MRI measures, after accounting for measured health and lifestyle factors, but the study did not show that changing sleep would reverse those differences. It also did not establish a dementia-prevention effect, a personal risk calculator or a clinical need for this imaging method.
What this could mean for protecting brain health
The potential value of this line of research is the possibility of more tailored sleep care across adulthood. If future longitudinal studies show that the observed associations reflect modifiable processes, and that improving sleep changes later brain outcomes, sleep support could eventually be timed to the periods of life when particular patterns matter most. That could help people preserve healthy brain tissue as they age.
The February 2023 findings are an early reason to investigate that possibility, not a screening tool or a treatment result. Their contribution is to suggest that sleep quality, sleep duration, sex and life stage may need to be considered together when researchers study healthy brain aging.
Key Sources
- Primary source: Sleep quality and sleep duration predict brain microstructure among community-dwelling older adults.
DOI or Journal Page · Peer-Reviewed Paper · 2023-02-10