
Research Signal – Source date 2021-10-23
An early senolytic study can sound more decisive than it is. Fewer senescent cells may indicate that a drug reached one of its intended biological targets. Improved physical function may suggest a useful treatment. Those are meaningful observations, but they answer different questions.
A review published in October 2021, Strategies for late phase preclinical and early clinical trials of senolytics, brings both kinds of evidence into the same discussion. It describes early human observations involving dasatinib plus quercetin, while also examining why senolytic drugs can behave differently across cell types and how coordinated trials might test whether these biological changes matter to patients.
The question begins with a cell
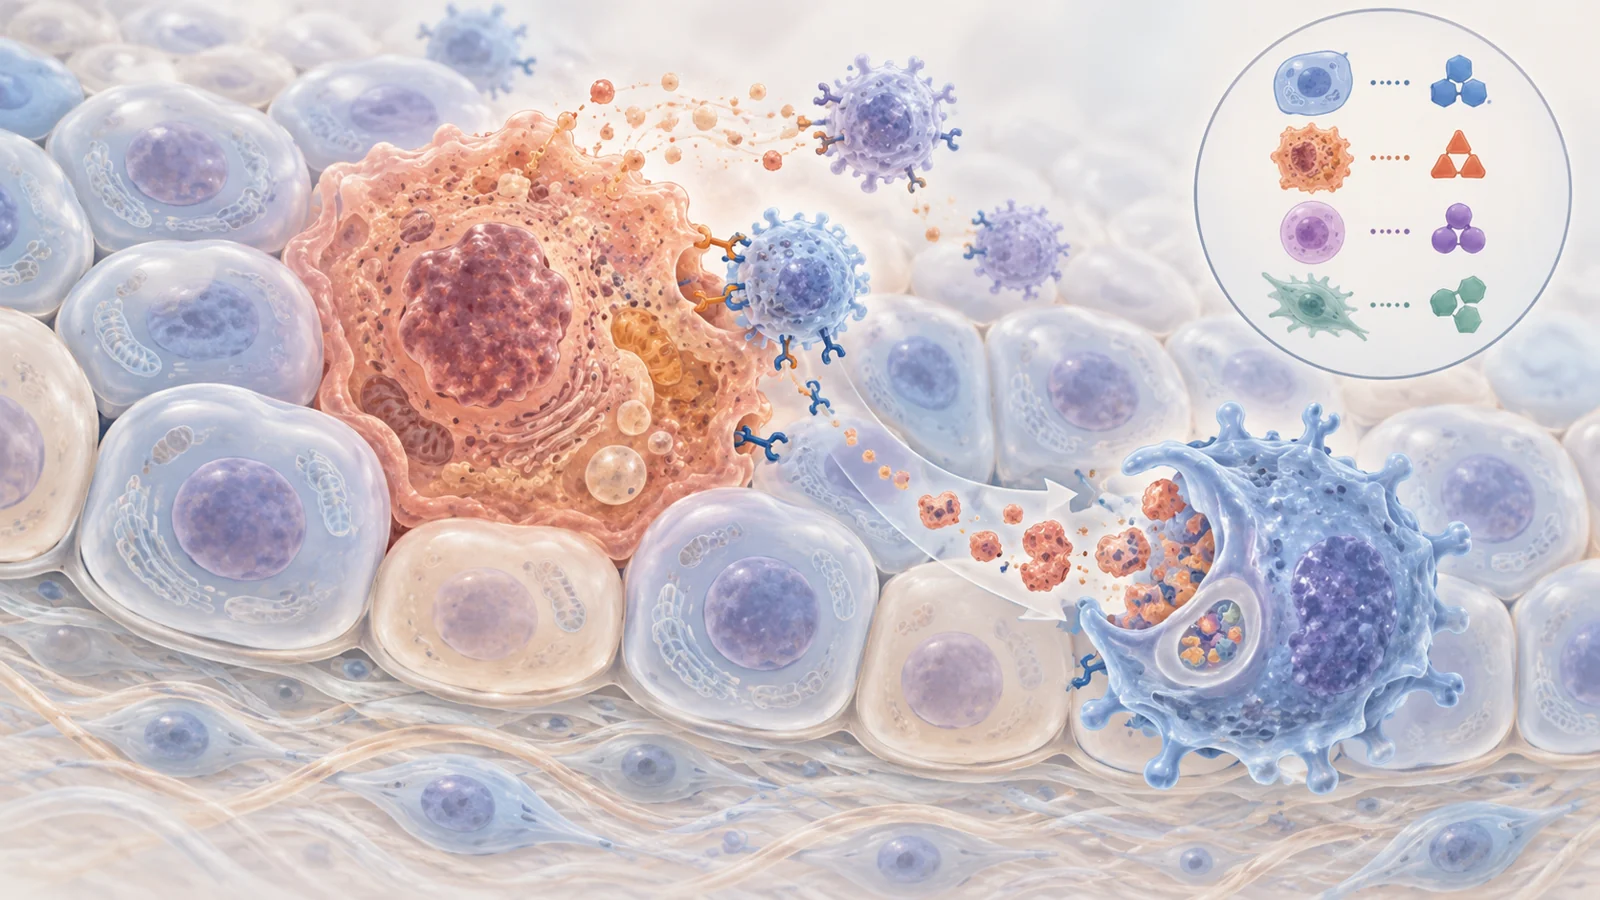
Cellular senescence is a state in which a cell stops dividing. Senescent cells can also resist programmed cell death, allowing them to remain in tissues rather than being removed. Some are eventually cleared by the immune system, but the review describes a threshold theory in which accumulation can outpace that clearance capacity.
The concern is not simply that a cell has stopped dividing. Some senescent cells release a collection of signals known as the senescence-associated secretory phenotype, or SASP. These secretions can include inflammatory molecules, growth factors, proteases, lipids and other biological materials. Depending on the cell and tissue, they may disturb nearby cells, affect stem or progenitor cells, alter immune function and contribute to tissue dysfunction.
This creates two related intervention strategies. Senolytics aim to remove senescent cells by exploiting the survival mechanisms that help them resist death. Senomorphics, such as the examples metformin or rapamycin discussed in the review, aim to suppress harmful secretions without necessarily removing the cells. The distinction matters because changing the signals around a cell is not the same intervention as clearing the cell itself.
The authors place senescence within a broader theory that the major processes of aging are interdependent. In that view, intervening in one process might influence several others. The theory helps explain why senescent cells are being considered in conditions as different as frailty, cardiovascular disease, metabolic disorders, osteoporosis and neurodegeneration. It remains a proposal about biological relationships, not a guarantee that one treatment will improve every linked condition.
A senolytic is not a universal cleaner
The first senolytic combinations were not designed around a simple one-target, one-disease model. The review describes a mechanism-based search for compounds that could interfere with senescent cell anti-apoptotic pathways, the survival networks that help these cells avoid programmed death. Different compounds can therefore act on different senescent populations.
Dasatinib, an anti-cancer drug, was identified as senolytic against human senescent adipocyte progenitors in the cited experimental work. Quercetin, a naturally occurring flavonoid, showed activity against senescent human umbilical vein endothelial cells. Their combination, commonly abbreviated D+Q, acted across a broader range of senescent cell types than either compound alone in that work.
That broader activity does not make the drugs interchangeable, or establish that a combination will be clinically superior. A candidate may work well against one senescent population and poorly against another because the cells rely on different survival pathways. The tissue in which the cells reside can also change the practical balance between removing a harmful cell and disturbing neighboring healthy cells.
Navitoclax illustrates the problem from another direction. The BCL-2-related investigational drug has several relevant targets and can induce apoptosis in human umbilical vein endothelial cells, but not in human preadipocytes, according to the review. It can also affect non-senescent cells, with severe neutropenia and platelet deficiency identified as important off-target concerns. A drug that attacks a survival pathway is not automatically selective simply because the pathway is important in senescent cells.
This is why the phrase senolytic drug describes an intended action more than a single uniform pharmacology. The useful question is always: which cells are being targeted, in which tissue, through which survival mechanism, and with what consequences for cells that should remain?
Mouse results depend on the model
Before human testing, D+Q produced different outcomes in different mouse models. In naturally aged mice, the review describes improved cardiac function. In radiation-exposed mice, it describes improved exercise capacity. In progeroid Ercc1 mice, treatment delayed age-related dysfunction. Each result belongs to a particular model and endpoint; none is a general demonstration that senolytics reverse aging.
The disease context changes the interpretation further. In mice with bleomycin-related lung injury, D+Q killed senescent fibroblasts and improved physical and pulmonary function. In obese mice, it alleviated metabolic and adipose-tissue dysfunction. In atherosclerosis models, it helped decrease senescent cell burden, while in osteoporosis models it increased bone mass and strength.
These findings are encouraging because they connect senescent-cell targeting to more than one kind of outcome. They also show why a single label such as improvement can hide important differences. Cardiac function, exercise capacity, adipose dysfunction, senescent-cell burden, bone strength and pulmonary function are separate measurements in separate models. A benefit in one does not supply the missing result for another.
The review describes the first human trials as especially cautious because senolytic agents were novel and their risk–benefit balance was uncertain. Serious conditions such as diabetes, idiopathic pulmonary fibrosis and osteoporosis were considered suitable settings for early investigation. Fisetin and quercetin had favorable safety profiles described in the review, while dasatinib had been used in clinical practice since 2006. Those facts helped support testing, but prior use of an individual drug does not settle the safety of a particular senolytic regimen.
Early human studies ask different questions
The first in-human trial discussed in the review involved patients with idiopathic pulmonary fibrosis. After treatment with D+Q, the patients showed improved physical function. In a separate early clinical trial involving patients with diabetic kidney disease, D+Q reduced the senescent cell burden measured in adipose tissue.
These observations are important precisely because they are not the same observation. Physical function is a patient-centered outcome. Adipose senescent-cell burden is a biological measurement in a particular tissue. The latter does not by itself establish improved kidney function or a meaningful clinical benefit, and the physical-function observation should not be expanded into demonstrated reversal of lung fibrosis or improved pulmonary function in those patients.
The review also describes an open-label pilot phase 1 Alzheimer’s disease trial whose results were then awaiting publication, with a phase 2 component about to begin. That position in the research process matters. A completed trial with results awaiting publication, an early biological measurement and a reported functional observation all represent different stages of evidence. They should not be blended into a claim that senolytics treat multiple diseases successfully in the same person, extend human lifespan or reverse aging generally.
What these studies do provide is a way to ask sharper questions. Did the intervention reach a relevant cell population? Did the tissue measurement change? Did patients function better, feel better or experience disease-related improvement? How durable were those changes, and what harms accompanied them? The early observations brought together by the review begin to separate those questions, even though they do not answer all of them.
Building trials that can answer them
The Translational Geroscience Network was created to make testing across aging mechanisms more coordinated. The network brought together eight institutions, including Mayo Clinic, Harvard, Johns Hopkins, Wake Forest, the Universities of Minnesota, Michigan and Connecticut, and the University of Texas Health Sciences Center at San Antonio. It also had partners such as St. Jude Children’s Cancer Hospital and the Steadman Clinic.
Its value is operational as much as scientific. Parallel work across institutions can help researchers study interventions in several diseases and aging contexts without every group having to build its own isolated infrastructure. Shared data management, statistical analysis, regulatory, biobanking and inclusion resources can make it easier to compare what different studies are actually measuring.
The network’s Facility for Geroscience Analysis develops assays for aging and disease markers. Those tests can help assess target engagement and efficacy in preclinical and early clinical trials. Target engagement asks whether an intervention appears to affect the intended biological process. Patient outcomes ask whether the person’s function, symptoms or disease course changed in a way that matters. A laboratory assay can support the first question without substituting for the second.
That separation is especially valuable for senolytics. A drug may reduce a measurable senescent-cell population in one tissue while having little effect on the condition that brought a patient into a trial. Conversely, a functional change may require attention to several biological processes rather than one cell count. Coordinated infrastructure can help connect these measurements without treating them as interchangeable.
What this could change
The practical promise is broader than clearing a cell under a microscope. Older people often manage several chronic conditions at once, and a treatment aimed at a shared aging mechanism could eventually help preserve everyday function across more than one of them, reducing some of the burden of treating each illness separately. That possibility depends on senescent-cell targeting producing meaningful patient improvements, not only biological changes, with an acceptable balance of benefit and harm in each relevant condition. The October 2021 review presents the infrastructure and early observations needed to investigate that possibility, while leaving the central clinical question open.
Key Sources
- Primary source: Strategies for late phase preclinical and early clinical trials of senolytics.
DOI or Journal Page · Review or Meta-Analysis · 2021-10-23
Keep exploring