
Research Signal – Source date 2021-09-28
Can removing senescent cells help an older person move more easily, or can it mainly make a laboratory measurement look different? That question sits at the center of the 2021 paper Targeting Cellular Senescence for Age-Related Diseases: Path to Clinical Translation. The paper is a synthesis of research rather than a newly conducted trial. It brings together cell and animal studies, drug-discovery work, and early human pilots to examine whether senescence might become a treatment target for age-related disease.
The idea is attractive because senescent cells may contribute to several conditions at once. The practical test, however, is not simply whether a drug changes p16, p21, inflammatory proteins, or the number of senescent cells in a tissue. A clinically useful treatment would need to help people function, preserve important biological roles, and avoid unacceptable effects on healthy cells. The early human evidence described in the paper had begun to address those questions, but in small and open-label studies with different measurements.
The biological problem is more specific than aging
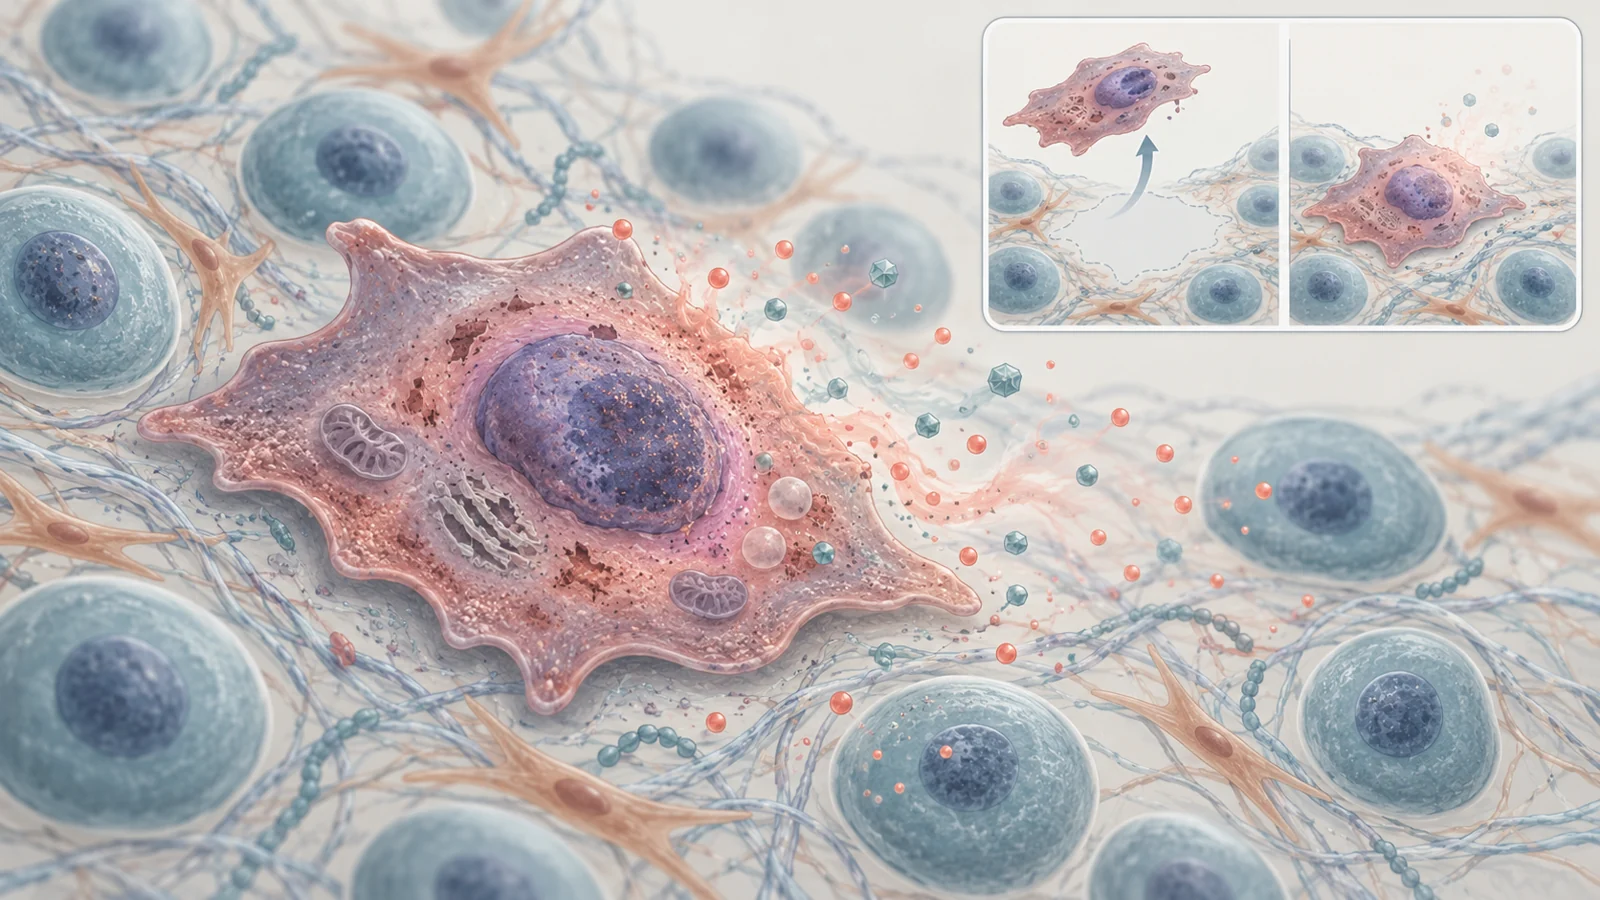
Cellular senescence is a state that cells can enter after damaging or stressful signals. Senescent cells stop dividing, become resistant to programmed cell death, and often change what they release into their surroundings. The state can be triggered by several kinds of cellular damage, including changes affecting DNA, mitochondria, proteins, or inflammatory signaling.
A senescent cell is therefore not simply an old cell that has become inactive. Its altered secretions can include cytokines, chemokines, proteases, microRNAs, and other factors. Collectively, these secretions are often called the senescence-associated secretory phenotype, or SASP. Depending on the cell type and context, the SASP can influence neighboring cells, stem and progenitor cells, and the surrounding tissue. Some senescent cells may produce a more inflammatory and tissue-disruptive pattern, while others may behave differently.
The paper describes a threshold-like possibility. The immune system can clear some senescent cells, but accumulation may eventually exceed that capacity. In animal experiments summarized by the authors, transplanting relatively small numbers of senescent cells into younger or older mice produced persistent physical dysfunction and could spread senescence-related changes into host tissues. These findings support the idea that senescent-cell burden can become biologically important, while still leaving open how well that mechanism translates to human disease.
Two strategies target different parts of senescence
Senotherapeutics are not one single kind of treatment. Senolytics are drugs intended to eliminate susceptible senescent cells. Senomorphics take a different approach by reducing or changing the cells’ harmful secretions while leaving the cells in place. The distinction matters because a treatment can alter tissue signaling without removing the underlying cells, and removal can have consequences that secretion control does not.
Dasatinib and quercetin provide the paper’s concrete example of why combinations were explored. Dasatinib, an anticancer drug, showed senolytic activity against human senescent adipocyte progenitors in the research summarized by the authors. Quercetin, a flavonoid, showed activity against a different senescent cell type, including umbilical vein endothelial cells. Used together, the two compounds were described as having broader activity across senescent cell types than either might have alone.
That description is about how the compounds were selected and studied, not a guarantee that they clear every senescent cell or improve every age-related condition. The target is a cell state with varied biology, rather than one universal molecule shared in the same way by all senescent cells.
Early human studies answered different questions
The first clinical example discussed in the paper was a small, open-label pilot involving 14 people with idiopathic pulmonary fibrosis. Participants received dasatinib plus quercetin, and the study reported improvements in physical-performance measures within one week. These included six-minute walk distance, gait speed, chair-stand time, and a broader short physical performance assessment. Changes in physical function were also correlated with changes in several SASP-related proteins, microRNAs, and inflammatory cytokines.
This pilot came closer to the reader’s main question because it measured how participants performed physically. Even so, the study design makes the observation preliminary. It was small, open-label, and did not by itself establish that the treatment produced durable improvements, that the effects would extend to other diseases, or that the changes resulted specifically from removing senescent cells.
A separate open-label pilot enrolled nine people with obesity and diabetic kidney disease. In that study, dasatinib plus quercetin was associated with reductions in adipose-tissue senescent-cell burden, SASP factors, and expression of p16INK4A and p21CIP1. Those measurements provide information about the treated tissue and possible target engagement. They are not the same as a demonstration that kidney function improved, that participants became more physically capable, or that another organ would respond in the same way.
The two pilots therefore point in different directions. One reported changes in physical performance alongside molecular measurements. The other reported changes in adipose tissue and senescence-associated markers. Both observations can matter, but they should not be merged into a single claim of clinical benefit. Senescence markers also vary in sensitivity and specificity, so the paper argues for multimodal assessment rather than relying on one marker to identify senescent cells or prove that a treatment reached its target.
Useful senescence makes treatment harder
Eliminating senescent cells sounds straightforward until their normal roles are considered. The paper describes early senescence as part of a protective response that can limit cancer-cell proliferation and contribute to acute wound healing. Chronic or late senescence, by contrast, may become damaging as senescent cells accumulate and alter tissue behavior. A treatment that removes cells indiscriminately could therefore interfere with useful biology, even if it reduces harmful signaling elsewhere.
Skin illustrates the problem. Senescent fibroblasts and keratinocytes can accumulate in aged skin, where fibroblasts may shift from producing extracellular-matrix components toward degrading them. That pattern is relevant to skin aging and tissue structure. Yet senescence also has a role during wound repair, so the goal would not simply be to erase every cell showing a senescence-associated feature at every moment.
Drug selectivity creates a second complication. The paper discusses navitoclax, a BCL-2-family inhibitor, as a candidate senolytic whose effects can extend beyond senescent cells. Off-target effects on non-senescent cells, including platelets and immune cells, limit the appeal of treating one molecular survival pathway as though it uniquely identified senescent cells. The concern is not only whether a compound can kill a senescent cell, but which other cells it may affect while doing so.
From cell measurements to a broader clinical goal
The larger promise of this field is not a cosmetic change in a biomarker panel. It is the possibility that one biological contributor could be involved in several age-related disorders, allowing treatment to address part of the shared burden behind multimorbidity. If senescent-cell accumulation contributes to declining tissue function in more than one organ, a carefully targeted intervention might eventually help older patients retain physical capacity while also reducing the need to manage each related problem in isolation.
That possibility depends on evidence that controlled studies can reproduce durable functional gains, with acceptable harms and preservation of useful senescence. It also depends on knowing which patients, tissues, cell types, and disease settings are most appropriate for a given senotherapeutic strategy. The paper describes parallel clinical testing across institutions as a way to evaluate safety, target engagement, and efficacy more efficiently than isolated studies conducted one after another.
What this could change
A successful senotherapeutic would give clinicians a way to treat a biological contributor shared across multiple age-related conditions, rather than responding only to the final symptoms of each disease. Older adults might retain more physical function, and the cumulative burden of multimorbidity could become more manageable. That future remains conditional: controlled clinical studies would need to show lasting improvements that matter to patients while demonstrating that treatment does not disrupt protective senescence or harm non-senescent cells.
Key Sources
- Primary source: Targeting Cellular Senescence for Age-Related Diseases: Path to Clinical Translation.
DOI or Journal Page · Peer-Reviewed Paper · 2021-09-28
Keep exploring