
Research Signal – Source date 2021-10-07
When a therapy removes senescent cells, what would show that it actually helps someone with disease? A lower laboratory marker might be a clue, but it is not the same as better mobility, organ function, or daily life.
A review published on October 7, 2021, titled Strategies for Targeting Senescent Cells in Human Disease, organized the field around that problem. It examined how senescence works, how researchers might alter or eliminate senescent cells, and what early human studies had observed. Its central challenge was not simply finding a way to remove cells. It was deciding which cells to target, what their removal would accomplish, and how to connect biological changes with patient outcomes.
A useful pause can become a chronic disturbance
Cellular senescence is a cell state marked by stable arrest of proliferation. A senescent cell has stopped dividing, but it has not necessarily become inactive. Stressors such as DNA damage, oxidative stress, mitochondrial dysfunction, radiation, or oncogene activation can push a cell into this state. The cell then engages survival mechanisms that help it resist apoptosis, the programmed process by which damaged cells are cleared.
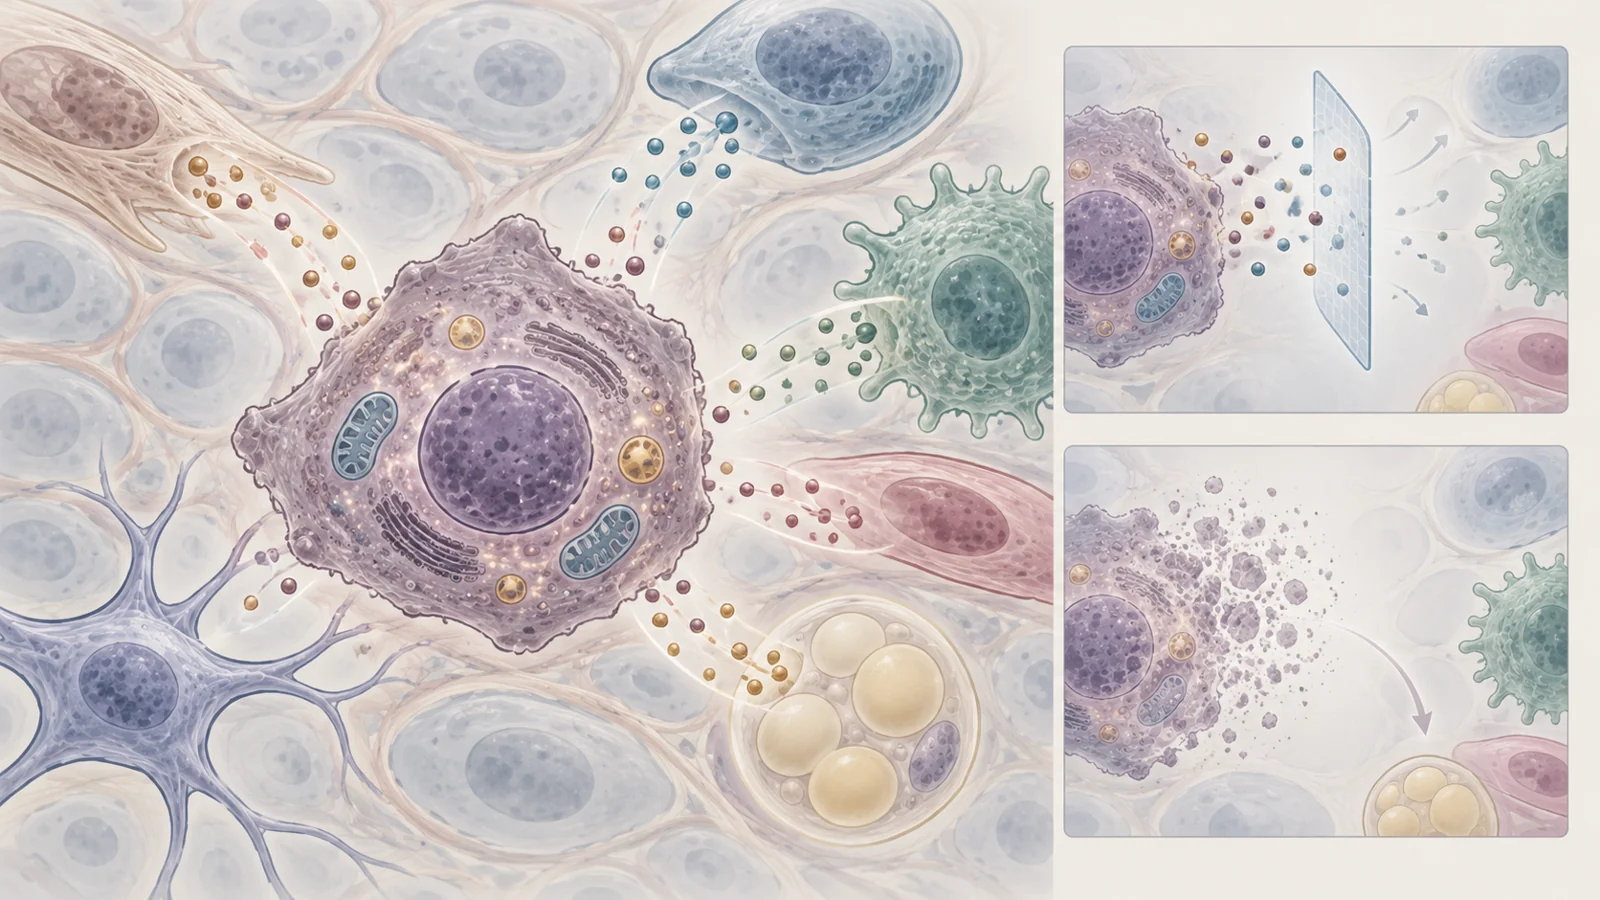
Many senescent cells also release a collection of molecules known as the senescence-associated secretory phenotype, or SASP. These signals can affect nearby cells and, when they circulate or persist, influence tissues farther away. The same general program can be useful in one setting and harmful in another.
During development, cells with senescent features help shape tissues and guide the removal of temporary structures. During wound healing and organ repair, carefully timed signals can recruit immune cells and coordinate tissue remodeling. Some SASP signals can even promote plasticity or regenerative behavior in neighboring cells. A brief pulse during repair is different from prolonged signaling by senescent cells that accumulate in a chronically stressed tissue. In models of regeneration, signals that support stem-like behavior temporarily can impair regenerative capacity when the exposure continues.
Senescence also helps limit tumor formation by stopping cells that have experienced dangerous stress. Persistent or poorly regulated senescence can instead contribute to inflammation, fibrosis, and tissue dysfunction. The therapeutic question therefore becomes highly specific: can a harmful senescent population be changed or removed while useful, temporary senescence remains available for repair and protection?
Two ways to intervene in a cell that will not divide
The review separates two broad strategies. Senomorphics aim to change the behavior of senescent cells by preventing, blocking, or neutralizing damaging SASP signals. In plain language, they try to quiet the cell without necessarily eliminating it. Senolytics are drugs intended to eliminate senescent cells by exploiting the survival systems that keep them alive.
The categories are useful, but they are not rigid labels. A compound that suppresses secretory behavior in one cell type or context may kill cells in another, and a drug described as senolytic may affect more than one aspect of senescence biology. The practical difference is the intervention’s immediate target: the harmful signals being released, or the cell producing them.
Dasatinib plus quercetin, commonly abbreviated D+Q, illustrates the senolytic approach. Rather than acting through one simple target, the combination interferes with several pro-survival networks, including ephrin dependence receptor signaling, PI3K/Akt signaling, and members of the BCL-2 family. These networks help senescent cells avoid the mitochondrial steps that lead to apoptosis. Disrupting them can make some senescent cells vulnerable to clearance.
Other BCL-2 family inhibitors showed senolytic activity against some senescent human cell populations in laboratory experiments. Their activity was not universal, however. Some pre-adipocyte populations were more resilient, and drugs in this family can also affect platelets, neutrophils, and possibly T cells. The biological appeal of intermittent cell removal therefore comes with a pharmacological problem: the same survival pathways may be important in healthy cells.
Senomorphics raise a different practical issue. Because they leave the senescent cells in place, their effects on secreted signals may require continued treatment. Senolytics may be given intermittently, but their usefulness depends on reaching the relevant cell populations and avoiding damage to tissues that still need senescent cells for a beneficial purpose.
Finding the right cells is part of the treatment
Before researchers can target a cell, they need a reliable way to recognize it. Senescence does not have one universal marker with both high sensitivity and high specificity. Different stressors can produce different senescent subpopulations, even in the same cell line. Cell type, tissue, prior stress, and surrounding environment all matter.
The proteins p16 and p21 are important examples. They can contribute to the cell-cycle arrest associated with senescence, but they are not interchangeable readouts of every senescent cell. A stressor may increase one more than the other, and some non-senescent cells can also express a marker under particular conditions. Senescence-associated beta-galactosidase, often shortened to SA-beta-Gal, is another widely used feature. It reflects changes in lysosomal activity, but it also has specificity limitations.
Researchers therefore combine several observations. They may assess cell shape and granularity, lysosome and mitochondrial changes, redox state, DNA-damage responses, and marker patterns alongside the absence of proliferation. No single result should carry the entire interpretation.
That matters when reading a biopsy result. A reduction in p16-positive or SA-beta-Gal-positive cells can indicate a change in the population detected by those assays. It does not automatically count every senescent cell in a tissue, and it does not by itself show that an organ is functioning better. The meaning of a marker change depends on which cells were measured, which features were included, and whether the biological change connects to a meaningful outcome.
Immune recognition adds a precision problem
Drug-based senolysis is not the only proposed route. The review also described an immune approach using chimeric antigen receptor, or CAR, T cells engineered to recognize the urokinase-type plasminogen activator receptor, uPAR. This surface protein was associated with several forms of senescence in the experimental work.
In mouse models, uPAR-directed CAR T cells cleared uPAR-expressing senescent cells. The treatment was associated with survival and tissue benefits in models of liver fibrosis caused by carbon tetrachloride or diet. These findings showed why cell-surface recognition is attractive: an immune cell can be programmed to seek a feature displayed by a target population rather than relying only on a drug’s distribution through the body.
Recognition and tolerability are separate engineering problems. Excessive CAR T dosing in the reviewed work was associated with inflammatory cytokine signals, weight loss, and hypothermia. In people, CAR T approaches also involve immune suppression and can produce serious burdens of their own. Senescent-cell specificity may improve targeting, but it does not remove the need to control dose, immune activation, expansion, and contraction of the engineered cells. The mouse findings therefore describe a promising experimental strategy, not established human efficacy or tolerability.
What early human observations actually measured
The review discussed a 14-person, open-label pilot in idiopathic pulmonary fibrosis. Participants received nine doses of oral D+Q over three weeks. Five days after the final dose, the study reported improvements in six-minute walk distance, walking speed, chair-rise ability, and a short physical-performance battery.
Those measures are closer to patient function than a molecular marker, which makes them important observations. The design also leaves several possible explanations in play. Participants and investigators knew the treatment was being given, and performance measures can be influenced by learning effects or other features of an open-label study. The findings were therefore an early signal that needed stronger testing, not proof that D+Q caused the improvements.
A separate interim report involved nine people with diabetic kidney disease. After a three-day oral course, biopsies taken 11 days after the last treatment showed decreases in adipose-tissue p16-positive and SA-beta-Gal-positive cells. A composite score of 10 circulating SASP factors also decreased. The study additionally observed less activated CD68-positive macrophage infiltration and fewer adipose-tissue crown-like structures, which are associated with fibrosis in that tissue.
These observations describe adipose tissue and circulating secretory factors. They do not establish improved kidney function. The continuing study had not, in the period covered by the review, produced a basis for broad conclusions about long-term safety. The absence of serious or severe side effects observed so far in that small, short-term setting also cannot establish safety in healthy people or for other senolytic and immune-targeting strategies.
The two clinical examples show why senotherapeutics need more than a single success signal. Functional measures can be meaningful but vulnerable to study design and attribution problems. Tissue and blood biomarkers can reveal that a biological process changed, yet still leave open whether the disease itself improved. A convincing treatment would need to connect a carefully identified target population with durable benefits that matter to patients.
What this could change
A successful senotherapeutic could eventually help people with chronic disease preserve mobility or organ function by reducing a tissue process that contributes to inflammation, fibrosis, or functional decline. The route to that benefit would be conditional: researchers would need to demonstrate sustained clinical improvement, identify the relevant senescent populations, and keep targeting tolerable while preserving senescence’s useful roles in development, repair, and tumor suppression.
That would make the field more than a search for lower p16 or fewer SA-beta-Gal-positive cells. It would turn the biology of cells that have stopped dividing into a practical treatment strategy whose value can be judged by how patients function and how their disease behaves.
Key Sources
- Primary source: Strategies for Targeting Senescent Cells in Human Disease.
DOI or Journal Page · Review or Meta-Analysis · 2021-10-07
Keep exploring