
Research Signal – Source date 2025-01-02
Fragmented nights, long periods of wakefulness and heavy daytime sleepiness are common problems for people living with Alzheimer’s disease. Sleep can become less restorative as the disease affects the brain systems that help organize daily rhythms. At the same time, poor sleep may influence biological processes associated with Alzheimer’s pathology.
A review published on January 2, 2025, examines one possible link between these problems: orexin, a brain signaling molecule that helps keep us awake. The central question is unexpectedly difficult. If orexin helps sustain wakefulness, could blocking its action improve sleep for people with Alzheimer’s disease? And if sleep improves, would that change only the night, or could it also affect the disease processes connected with memory loss?
The review brings together human observations, experimental findings and treatment studies. Its account suggests a relationship running in both directions, but it does not reduce that relationship to a single cause. Alzheimer’s disease may disrupt sleep and the systems that regulate arousal. Sleep loss may, in turn, alter processes involving amyloid-beta, tau and brain immune activity. Orexin sits near the intersection, without yet providing a settled explanation.
Why wakefulness matters in a disease marked by broken sleep
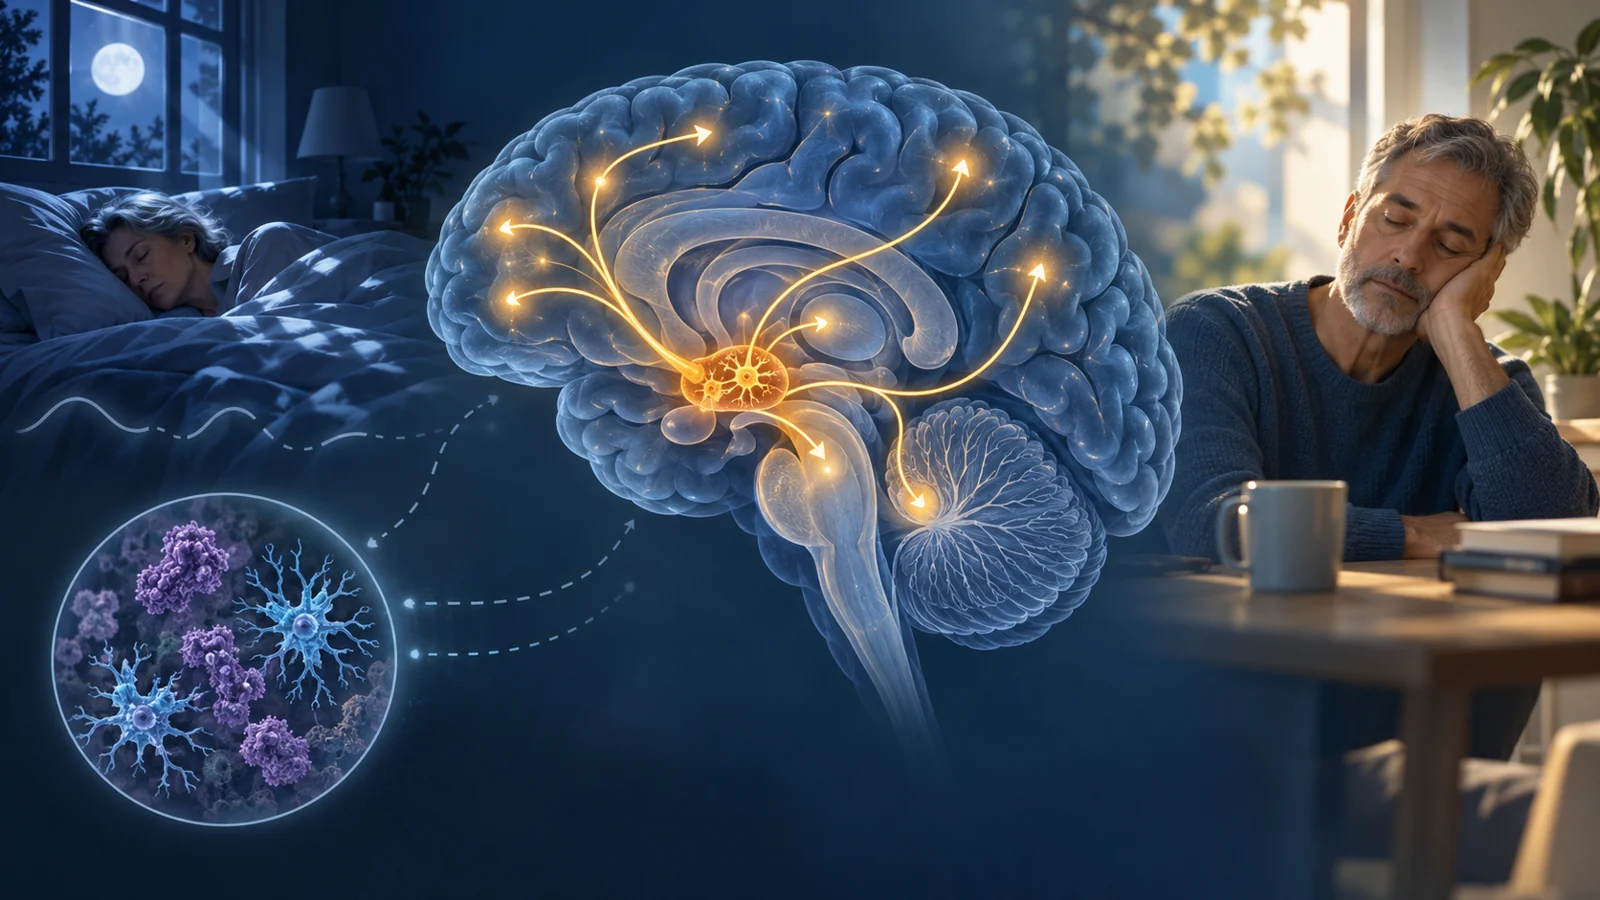
Orexin is produced by a relatively small group of neurons in the hypothalamus, a region involved in basic body and brain regulation. Those neurons send projections widely through the brain, influencing arousal networks that help a person remain awake and responsive. Orexin does not simply act as an on-off switch for consciousness. It helps stabilize wakefulness over time and works with other signaling systems that activate the cortex and suppress sleep-promoting circuits.
Its importance becomes clear in narcolepsy. When orexin signaling is lost, people have difficulty staying awake for long periods, and features of rapid eye movement sleep can intrude at inappropriate times. The result can include sudden transitions into sleep and cataplexy, in which muscle control briefly fails during wakefulness. This contrasting condition shows why orexin has a necessary role: reducing its activity is not biologically neutral, even when the goal is to make sleep easier.
Alzheimer’s disease can disturb the same broad balance from another direction. People may wake repeatedly at night, sleep at unusual times, or remain sleepy during the day. The review describes changes in circadian timing and sleep architecture, including reductions in slow-wave and rapid eye movement sleep. These disruptions can make daily life harder and may interfere with the sleep-dependent processes that support memory and cognitive function.
The question is therefore not whether wakefulness is good or bad. The question is whether an arousal system that is useful in a healthy sleep-wake cycle becomes poorly timed, overactive or otherwise dysregulated as Alzheimer’s disease progresses.
Sleep changes the amyloid balance
The review describes several ways that sleep loss might influence amyloid-beta, a protein involved in Alzheimer’s disease pathology. Amyloid-beta levels fluctuate with the sleep-wake cycle. In the findings summarized by the review, levels rise during wakefulness and fall during sleep, while sleep deprivation can increase amyloid-beta in the cerebrospinal fluid of healthy adults. Experimental work also points to changes in production by neurons and astrocytes, a type of supporting brain cell.
Production is only half of the proposed story. The brain must also remove proteins from the spaces around its cells. Cerebrospinal fluid and interstitial fluid participate in that clearance, and microglia, the brain’s resident immune cells, can take up extracellular amyloid-beta. The review discusses evidence that sleep loss may weaken these removal processes, including by reducing microglial handling of amyloid-beta. A higher level could therefore reflect both more being made and less being cleared.
That distinction matters because a short-term rise in a biomarker is not the same thing as a demonstrated disease outcome. The review describes experimental findings in which prolonged orexin exposure, used to model continued sleep loss, inhibited microglial degradation of amyloid-beta. Such work helps explain a possible biological pathway, but it does not show that one night of poor sleep causes Alzheimer’s disease or that changing orexin alone would prevent it.
Tau offers a second proposed connection. The review reports associations between orexin levels and total tau or phosphorylated tau in different human and experimental contexts. It also describes animal and cell findings in which altering orexin signaling changed tau-related measures. These observations broaden the question beyond amyloid-beta, while leaving the relationship between orexin activity, sleep, neuronal injury and disease progression unresolved.
Orexin findings do not point one way
Human measurements are one reason the story remains unsettled. The review includes studies reporting lower cerebrospinal fluid orexin-A in some people with advanced Alzheimer’s disease and higher levels in other groups with moderate to severe disease. It also discusses increased orexin after partial sleep deprivation. These results do not establish that high orexin is a uniform feature of Alzheimer’s disease, nor do they make orexin a validated diagnostic marker.
Different results could reflect differences in disease stage, sleep-wake state or the way the underlying systems are changing. They may also indicate that orexin is responding to the disorder rather than initiating it. The review explicitly leaves open whether altered orexin signaling is part of the neurodegenerative process, a consequence of disrupted sleep, or both.
One possibility is compensation. Alzheimer’s disease can damage cholinergic neurons in the basal forebrain, an important arousal system. If that system becomes less effective, orexin neurons or other wakefulness pathways might increase their activity to help sustain alertness and cognitive function. Compensation could be useful for a time, but persistent hyperarousal might also make sleep more difficult and place additional stress on processes linked with amyloid-beta and tau.
Higher orexin could reflect sleep deprivation or compensation for disruption elsewhere in the arousal system. The contrasting measurements do not establish which mechanism explains a given group’s results, or whether orexin changes are driving disease processes or responding to them.
Blocking the wakefulness signal tests a bigger idea
Dual orexin receptor antagonists are designed to block both of the main orexin receptors. By reducing orexin’s wake-promoting action, these medicines aim to make sleep easier to initiate or maintain. The review discusses suvorexant and lemborexant as emerging treatments for sleep disturbances in Alzheimer’s disease and summarizes studies in which participants experienced better sleep parameters, fewer nighttime awakenings and improved daytime functioning.
Those reported sleep outcomes are important in their own right. A night with fewer interruptions can change how much time a person spends awake in bed and how demanding the following day feels. For caregivers, more predictable sleep may also reduce the disruption caused by repeated nighttime waking. Yet these are sleep and functioning outcomes, not proof that the underlying neurodegenerative process has been altered.
The larger therapeutic hope comes from the proposed biology. If sleep helps clear amyloid-beta, and if orexin activity influences amyloid-beta, tau or inflammatory processes, then receptor blockade might eventually offer benefits beyond sedation or better sleep. The review presents this as a possibility supported by experimental findings and early treatment interest. It does not establish that these medicines prevent Alzheimer’s disease, reverse it or durably slow cognitive decline.
The distinction is especially important because a treatment can improve a symptom without changing the disease that contributes to it. Better sleep might support daytime function while leaving amyloid and tau pathology unchanged. Conversely, a biological effect on amyloid-beta in an experimental setting would still need to be connected to meaningful, durable outcomes for people. Sleep improvement, biomarker change and slower cognitive decline are separate claims that require separate clinical evidence.
Safety also remains part of the question. The review describes dual orexin receptor antagonists as generally well tolerated in the studies it summarizes, while noting reported effects such as daytime drowsiness and headache. For people already vulnerable to falls, confusion or impaired alertness, preserving safe daytime function matters as much as reducing nighttime wakefulness. Longer-term assessment is needed to understand how sustained receptor blockade affects people with Alzheimer’s disease.
What better nights could mean for people with Alzheimer’s
For patients and families, the first possible benefit is practical rather than molecular. More consolidated nighttime sleep could mean fewer disruptive awakenings, less daytime sleepiness and a daily routine that feels less fragmented. Better daytime functioning could make ordinary activities easier if those improvements persist and treatment does not compromise alertness or safety.
A further possibility is that improving sleep could support processes related to amyloid-beta clearance, tau biology or cognitive resilience. That prospect is scientifically important, but it remains a separate claim from the sleep benefit itself. Protection of memory or slower disease progression would need to be demonstrated directly in appropriately designed clinical studies.
From the January 2025 perspective of this review, orexin is best understood as a promising point of contact between two problems that often appear together: unstable sleep and Alzheimer’s disease. Blocking the system may help some people sleep more consistently, while the consequences for the disease itself remain an open question. The answer will depend on whether better nights translate into durable improvements that extend beyond the bedroom without sacrificing safe, useful wakefulness during the day.
Key Sources
- Primary source: The interaction between orexin, sleep deprivation and Alzheimer's disease: Unveiling an Emerging Connection.
DOI or Journal Page · Review or Meta-Analysis · 2025-01-02
Keep exploring