
Evidence date · 2026-07-23 · Research note 3 of 3
1 2 3
See current Track status →
Since the previous research note · Earlier expectation not tested
Track continuity
Since the previous research note: How a virus used in smallpox vaccines could trigger an immune response beyond a lung tumor
Previous expectation: Vaccinia-based treatment might eventually combine local tumor destruction with immune control beyond the infected cancer cells if delivery, antiviral immunity and clinical efficacy barriers are overcome.
What this study adds: The July 23, 2026 study investigates a different viral platform, adding cGAS to an adenovirus and reporting model-dependent distant-tumor findings plus regression in three of five mice receiving PD-L1 blockade with the virus. It adds a specific preclinical combination strategy to the lung-cancer virus-therapy timeline without testing the vaccinia forecast.
What changed in this study
Three of five mice showed tumor regression after receiving an engineered adenovirus together with a PD-L1-blocking antibody. That result, reported in a July 23, 2026 study, came from mice bearing implanted lung-cancer tumors—not from people with lung cancer. It raises a focused question: can a virus keep attacking cancer cells while also making the tumor environment more visible to the immune system?
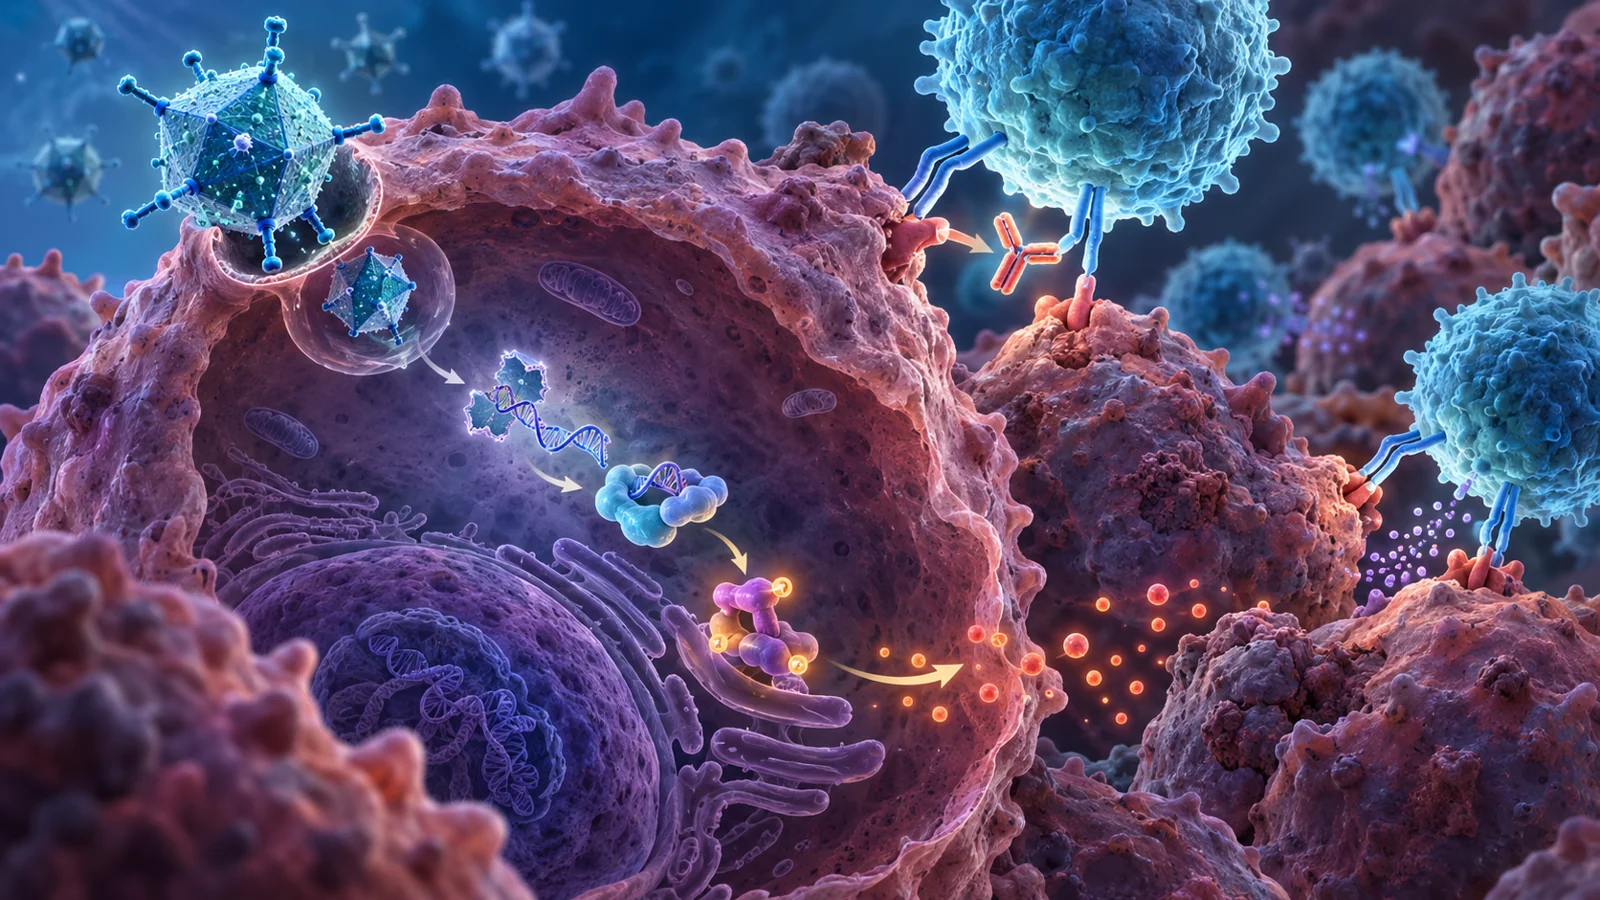
The researchers built two related viruses to investigate that possibility. They added cGAS, an enzyme that senses DNA inside cells and starts an immune-signaling pathway, to an oncolytic adenovirus platform. The human version was tested mainly in human lung-cancer cells; the mouse version was used in a mouse lung-cancer model. Both were designed to replicate preferentially in tumor cells and already carried GM-CSF, another immune-related cargo.
The results suggest that adding cGAS can engage the STING pathway without eliminating the virus’s measured ability to replicate. The combination with PD-L1 blockade then produced a stronger treatment result in the tested mouse experiment. But the study leaves important questions about which cargo mattered, how much of the effect depended on the immune setting, and whether the strategy can distinguish tumors from healthy human tissue.
A virus that carries an immune alarm
Oncolytic viruses are intended to use the vulnerabilities of cancer cells to replicate and break them open. That can release material from the tumor, but the virus must also interact with the immune defenses that normally recognize viral activity. The study’s design uses that tension deliberately.
cGAS detects double-stranded DNA in the cell’s cytoplasm. After sensing that DNA, it produces cGAMP, a messenger that activates STING. STING then recruits TBK1, which activates IRF3 and helps drive type I interferon and other inflammatory signals. In a tumor, those signals can provide instructions for immune activity rather than leaving cancer-cell destruction as an isolated local event.
The researchers placed human cGAS into OAd-HcGAS and murine cGAS into OAd-McGAS. The viruses were built on an Ad5/3 chimeric adenovirus platform regulated by the hTERT promoter. Their existing design also expressed GM-CSF. The two versions were not interchangeable in the experiments: OAd-HcGAS was evaluated with human NCI-H226 lung-cancer cells, while OAd-McGAS was used with murine Lewis lung carcinoma, or LLC, cells.
In the human-cell experiments, OAd-HcGAS raised levels of phosphorylated TBK1 and IRF3, along with interferon-beta and inflammatory factors including CXCL10, CXCL9 and TNF-alpha. A STING inhibitor reduced the pathway activation under the tested conditions, supporting the involvement of STING in those cell assays. The engineered virus also showed replication kinetics comparable to the parent OAd-Z2 virus in the reported comparison.
The immune alarm did not stop the virus from attacking cells
The apparent paradox is important. STING signaling is part of an antiviral defense, so it might be expected to interfere with viral replication. In these experiments, however, activating the pathway did not produce a statistically significant reduction in OAd-HcGAS replication compared with OAd-Z2 in NCI-H226 cells. The virus could therefore retain its measured replication and cell-killing behavior while adding an immune-stimulating output.
The researchers tested whether that output changed the behavior of immune cells, not just the levels of signaling proteins. They co-cultured infected lung-cancer cells with peripheral blood mononuclear cells. OAd-HcGAS increased CD69 expression on CD8-positive T cells and natural killer cells, a marker of early activation, and increased interferon-gamma secretion. The co-cultures also showed more tumor-cell death than the comparison conditions.
Those findings connect the molecular measurements to a functional response in the laboratory. They do not show that every immune cell in a tumor will behave the same way, or that pathway activation alone caused the later tumor effects. They do show why the researchers viewed cGAS as more than an added label on the virus: it was intended to produce an immune signal while the virus continued to replicate in the cancer-cell system being tested.
The mouse models separated local treatment from distant effects
The first in vivo setting used human NCI-H226 tumors implanted in BALB/c-nu mice, which are immunodeficient. One tumor was injected directly with OAd-HcGAS, while the tumor on the opposite side was left untreated. By day 12, the treated tumors in the OAd-HcGAS group were smaller than those in the OAd-Z2 and PBS groups, with a reported tumor volume of 68.07 cubic millimeters and a 65.81 percent inhibition rate. The untreated tumors did not show a significant difference among groups.
That result is mainly a localized tumor-suppression observation in a model with limited immune function. It does not provide a clean test of how a fully functioning immune system might carry or amplify the response beyond the injected site.
The second model used immunocompetent C57BL/6 mice bearing bilateral LLC tumors. Here, OAd-McGAS was injected into only one tumor. By day 10, the reported inhibition rates were 79.55 percent on the treated side and 58.24 percent on the untreated side. Tumor-weight measurements also showed suppression on both sides compared with PBS, with an additional treated-side difference compared with OAd-Z2. In repeated experiments, complete regression at the treated site was observed in the OAd-McGAS group.
The untreated-side findings provide evidence of activity beyond the injected tumor in that particular model, but they should not be reduced to a simple story of immune cells traveling from one site to another. Viral DNA and Hexon protein were detected in both treated and untreated tumors from OAd-treated mice. The models also differed in tumor species, viral cargo and immune status. Those factors make it difficult to isolate immune status as the sole explanation for the distant findings.
Tumor analyses added biological context. OAd-McGAS increased CD8-positive T cells and tumor-associated macrophages in both tumor sites. Immunofluorescence also showed greater CD8-positive T-cell density. Tumor-infiltrating lymphocytes taken from OAd-McGAS-treated tumors were able to kill LLC target cells in a separate cytotoxicity assay. In contrast, the increase in conventional dendritic cells did not reach statistical significance, and the number of natural killer cells did not change.
Why the researchers paired the virus with PD-L1 blockade
The combination experiment followed an observation from the human-cell work. NCI-H226 cells infected with OAd-HcGAS increased PD-L1 protein expression. PD-L1 is part of a checkpoint system that can reduce T-cell activity, so its increase gave the researchers a reason to test whether blocking PD-L1 could complement the virus’s immune stimulation.
For the combination study, mice bearing bilateral LLC tumors received intratumoral OAd-McGAS and an anti-PD-L1 antibody. The virus was given at 100 million plaque-forming units per tumor every two days for two doses, while the antibody was administered at 5 milligrams per kilogram every two days for four doses. Five mice received the combination. Three showed tumor regression, and the reported tumor-inhibition rate was 95.22 percent.
The result is a treatment comparison in a small mouse group. It supports further investigation of the partnership, but it does not by itself establish formal pharmacological synergy, durable remission, immune memory or a clinical response rate. The study also measured immune changes in the spleen: the combination increased the proportions of CD4-positive and CD8-positive T cells in mice treated with PD-L1 antibody, while the proportion of natural killer cells did not change. Those spleen findings are separate from the tumor-infiltration measurements and should not be treated as interchangeable evidence.
What the experiments still leave open
One unresolved issue is attribution. The viruses carried both cGAS and GM-CSF, yet the study did not systematically compare the individual and combined contributions of those transgenes. The results therefore show what the complete constructs did in the tested systems, rather than assigning the antitumor effect to cGAS alone.
A second issue is causality. The H-151 experiments support STING involvement in the human-cell assays, but the authors did not establish a definitive in vivo causal link between STING activation and tumor control. Stronger tests would be needed to separate the pathway’s contribution from the effects of viral replication, tumor-cell lysis, GM-CSF and other immune responses.
Tumor selectivity also remains a design goal that needs direct support. The authors did not perform cytotoxicity and replication assays in normal human cells. Because STING is expressed in both tumor and normal cells, a strategy that delivers an immune agonist through a replicating virus must show more than activity inside implanted tumors. It must also demonstrate an acceptable margin between tumor targeting and effects on healthy tissue.
The mouse context adds another translation problem. The vector included human GM-CSF, whose activity in mice is limited because the mouse receptor has low affinity for the human cytokine. The observed activity in immunocompetent mice is therefore informative but not a direct preview of how the same cargo would function in people. Flank tumors, intratumoral dosing and the particular mouse immune systems used here also simplify conditions that would be more complex in human disease.
The reported safety observations were encouraging within the study’s boundaries. Body weight remained stable or increased, and the histological assessment found no significant tissue alterations or liver damage after OAd-Z2 or OAd-McGAS treatment. Those observations do not amount to comprehensive safety validation, especially when normal human-cell testing and clinical exposure are still unresolved.
What this could mean for lung cancer immunotherapy
The prospective capability is a tumor-directed viral treatment that combines cancer-cell destruction with local immune stimulation, potentially helping lung tumors respond more effectively to checkpoint therapy. People with lung cancer would benefit only if the effect is reproducible and the approach proves sufficiently selective and safe in human-relevant testing.
From the July 2026 publication perspective, the study adds a specific preclinical route for pairing an engineered adenovirus with PD-L1 blockade. Its most concrete contribution is not a treatment timetable or a promise of durable control. Across the tested cell and mouse systems, the cGAS-carrying viruses activated STING-associated signaling, retained replication in the human-cell assays and altered immune responses; adding OAd-McGAS enhanced the reported antitumor effect of the PD-L1 antibody in mice.
Key Sources
- Primary source: Oncolytic adenovirus armed with cGAS activates STING pathway and enhances antitumor immunity in lung cancer with superior combined efficacy of PD-L1 therapy.
DOI or Journal Page · Peer-Reviewed Paper · 2026-07-23