
Research Signal – Source date 2026-06-18
Cancer treatment often aims to keep engineered immune cells active so they can find and attack cancer cells that return. A proposed use against aging cells raises a different design question: could a brief, controlled attack be enough—and safer than keeping those cells on patrol?
A review published June 18, 2026, surveys research into chimeric antigen receptor T cells, or CAR-T cells, for age-related diseases. These are T cells engineered with a receptor that recognizes a chosen target on a cell’s surface. The review brings together animal and other preclinical findings, clinical experience treating blood cancers, and proposals for future designs. It reports no new treatment test in people for clearing senescent cells.
Aging cells can help and harm tissue
Cellular senescence is a state in which a cell stops dividing after stress such as DNA damage, shortened telomeres or oxidative stress. Senescent cells can also change shape and function, and release a mixture of signaling molecules called the senescence-associated secretory phenotype, or SASP.
Some of these signals, including inflammatory cytokines and chemokines, affect nearby cells. In the short term, SASP can help recruit immune cells to clear damaged or senescent cells. When senescent cells persist, however, their signals can contribute to chronic inflammation and disturb the surrounding tissue. The review links this process to conditions including atherosclerosis, diabetes and neurodegenerative disease.
Senescence is not simply a harmful state to eliminate wherever it appears. When a cell receives cancer-promoting signals, growth arrest can help keep it from multiplying uncontrollably. Some SASP signals can also help attract immune cells that remove precancerous cells. Over time, though, senescent cells in a tumor environment may release signals that support tumor growth and spread. What the cell is doing, where it is, and how long it remains senescent all matter.
The receptor sets the target and the risk
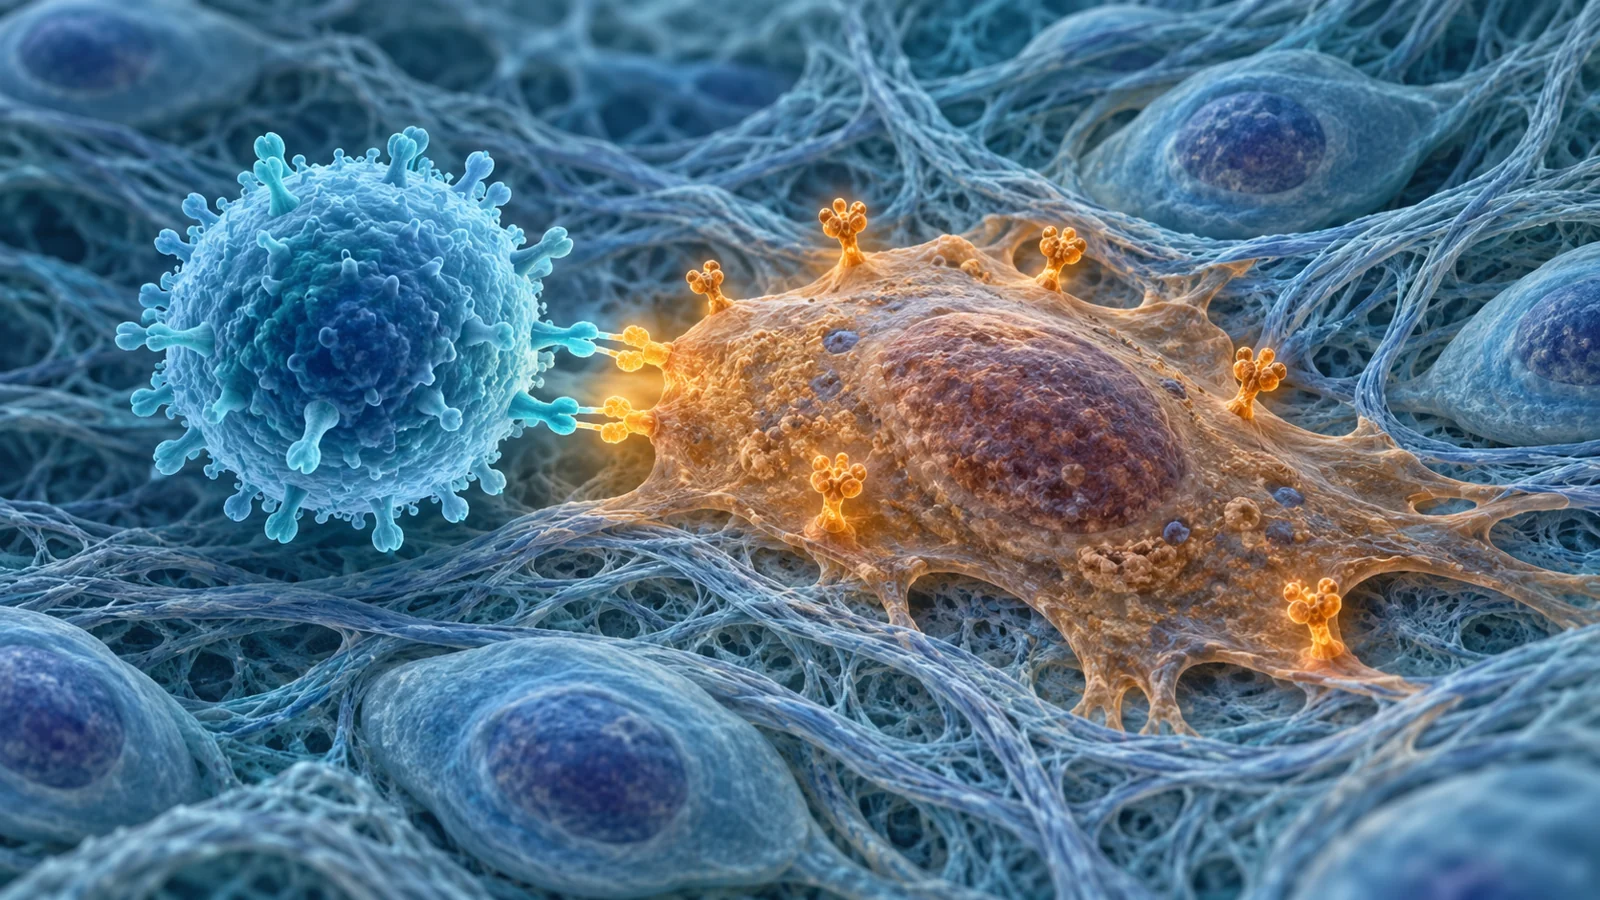
A CAR adds a designed recognition system to a T cell. Its outer part binds a chosen surface marker; its inner signaling parts activate the T cell after recognition. The marker is the address the engineered cell follows. If it is present on healthy tissue as well as the intended target, the same recognition system can put those tissues at risk.
CAR designs have changed over time. First-generation receptors had limited activation. Second-generation designs add a costimulatory signal, such as CD28 or 4-1BB, alongside CD3ζ to strengthen T-cell activity. The review describes second-generation CAR-T cells as the current standard in senescence research. For several age-related models, it identifies CD28ζ as a promising design because it can expand quickly and produce acute cell killing without aiming for prolonged activity.
That design goal differs from cancer treatment, where persistent immune surveillance can help prevent relapse. Against senescent cells, the review argues for potent but controlled activity: clearing a harmful cell population may not require the engineered cells to remain active indefinitely. More persistence or stronger signaling is not automatically better when the intended intervention is a bounded clearance.
Results vary across organs
The clearest example in the review is work with CAR-T cells directed at uPAR, a cell-surface marker used to identify senescent cells. In experimental models of liver fibrosis and lung adenocarcinoma-induced senescence, a single injection cleared senescent cells over the long term and restored tissue function. The review also describes improvements in age-related metabolic problems and physical function in models. These findings made uPAR-directed CAR-T cells a proof of concept for senescent-cell clearance, not a demonstrated treatment for people.
Cardiac fibrosis work raises a different question: how long must the engineered cells persist to affect disease? Both DNA-based FAP-CAR-T cells and a transient mRNA-based approach improved cardiac function in models despite limited CAR-T persistence. The review suggests that removing activated myofibroblasts—cells involved in scar formation—may interrupt a self-sustaining fibrotic process and give the tissue’s own repair mechanisms room to act. Advanced chronic disease or repeated injury could call for repeat treatment, but the model results do not settle that question for patients.
The brain-disease evidence is earlier. The review describes preclinical work in which NKG2D-directed CAR-T cells eliminated senescent neurons and glial cells in neurodegenerative disease models. That is a different target and tissue context from liver or heart fibrosis, and the review places this work at a very early stage of translation. A result in one organ cannot show that the same target, cell design or risk profile will work in another.
Older patients bring a different immune starting point
CAR-T has been used clinically in older people with blood cancers. The review reports that outcomes in older participants in trials of treatments for lymphoma and multiple myeloma were broadly comparable to those in younger groups, while toxicity risk was somewhat higher. This is relevant experience with CAR-T in older patients, but it concerns attacks on cancer cells. It does not establish that clearing senescent cells would help age-related disease.
Age can also affect the treatment cells and the environment they enter. The review describes preclinical evidence that aged T cells may be harder to use in manufacturing and that aged tissues may hinder CAR-T expansion and persistence. In aged animal models, infused cells tended to become short-lived effectors rather than central memory cells. Signals from senescent stromal cells and M2 macrophages, including TGF-β and IL-10, may contribute to CAR-T cell dysfunction. These are potential obstacles to how well a therapy can be made, how long it acts and how safely it behaves.
A precise address still has to be safe
Markers such as uPAR and NKG2D ligands are not confined to senescent cells; the review notes that they can also appear at low levels in normal tissues. A CAR that recognizes the marker may therefore affect cells beyond the intended population. Researchers are exploring ways to improve selectivity, including receptors that recognize more than one target and designs that activate only in particular tissue conditions, such as hypoxia. These are proposals under investigation, not clinically validated safeguards for age-related disease.
The known risks of CAR-T make the targeting problem consequential. Cytokine release syndrome can range from mild symptoms to life-threatening illness, and immune effector cell-associated neurotoxicity syndrome can also occur. Older patients may have less organ reserve to tolerate these complications. Approaches to manage or limit toxicity are part of the broader CAR-T field, but proposed short-lived or conditionally activated designs do not yet establish safety for senescent-cell treatment.
Making the cells is part of the access problem
Many current CAR-T treatments use a patient’s own T cells. The review describes a typical preparation period of two to four weeks and costs exceeding $500,000 per treatment. Older patients may have fewer T cells or cells of lower quality, which can make production harder as well as the biology more challenging.
Possible ways to reduce those burdens include donor-derived cells engineered to lower the risks of immune rejection, non-viral methods, automated manufacturing and approaches that generate CAR-T cells inside the body. The review cites projected cost reductions of more than 50% for some off-the-shelf approaches; these are projections, not established savings for an available senescent-cell therapy. Simpler production could eventually widen access, but it cannot compensate for an unsafe target or an ineffective treatment.
What targeted cell clearance could mean for scarred organs
If researchers can identify markers that distinguish harmful senescent cells from healthy tissue, and control how long engineered cells act, CAR-T could offer a way to remove cell populations that help sustain fibrosis or chronic inflammation. In principle, that could give damaged organs a better chance to recover without requiring the lasting immune surveillance used against recurring cancer. The liver and heart models offer reasons to investigate that possibility; they do not show that the approach prevents, treats or reverses age-related disease in people. Human benefit depends on solving the questions of target selectivity, immune function, safety and practical production first.
Key Sources
- Primary source: Research advances and application prospects of CAR-T therapy in the treatment of age-related diseases.
DOI or Journal Page · Review or Meta-Analysis · 2026-06-18
Keep exploring