
Research Signal – Source date 2022-08-15
Sleep changes are common in Alzheimer’s disease, but disturbed sleep is not the same thing as a damaged body clock. Sleep describes a visible pattern of rest and wakefulness. Circadian rhythms are the body’s internal daily timing system, coordinating activity across the brain and other organs even when a person’s sleep appears fairly regular.
A review published on August 15, 2022, brings together evidence on how these two ideas may intersect in Alzheimer’s. It discusses observations from people and postmortem tissue, alongside experiments in animals and cells. The evidence points to several connected biological processes, but it does not settle whether circadian disruption is mainly a consequence of Alzheimer’s, a contributor to its progression, or both.
Light reaches the brain’s central timing hub
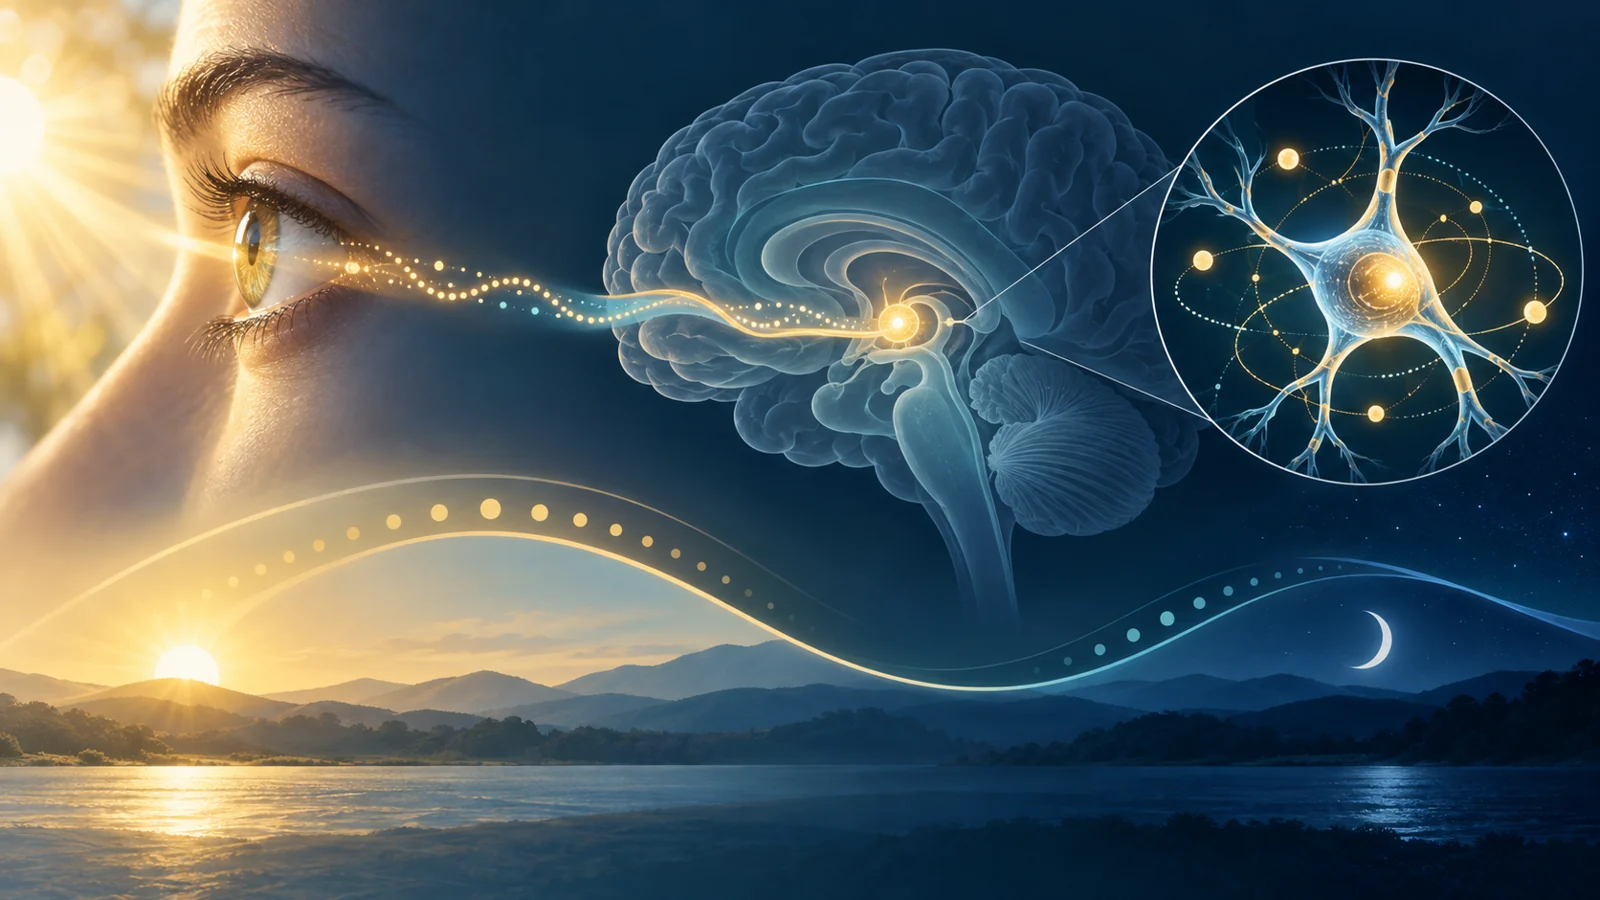
The daily timing system begins with information about light. A small population of retinal ganglion cells contains the light-sensitive protein melanopsin. These cells send information about the day–night environment through a pathway to the suprachiasmatic nucleus, or SCN, in the hypothalamus. The SCN acts as a central timing hub, helping synchronize rhythms in the brain and across the body through neural and hormonal signals.
This arrangement creates more than one possible point of disruption in Alzheimer’s. The review describes findings involving melanopsin-expressing retinal cells, including retinal amyloid-beta deposition and loss of these light-responsive cells. If light input is weakened or becomes less reliable, the signal reaching the SCN may also become less stable.
The SCN itself may be affected. Postmortem observations in people with Alzheimer’s have found neuronal loss in this region, associated with a lower-amplitude rest–activity rhythm. Changes in melatonin receptor expression were also described. Retinal damage and neuronal loss in the central timing hub are different findings, but each offers a possible explanation for why daily rhythms may become less distinct.
The clock is also distributed through cells. Molecular feedback loops involving clock genes help regulate the timing of processes in neurons and other tissues. In mice, cellular clock disruption can coexist with apparently normal sleep and activity rhythms.
A mouse can keep time while its brain cells are injured
The review uses BMAL1 experiments to show why observable rhythms and cellular clock function should not be treated as interchangeable. BMAL1 is one of the core genes involved in the molecular clock. In a mouse model with BMAL1 deleted in parts of the hippocampus and cortex, researchers observed severe astrogliosis, synaptic degeneration and oxidative damage in affected brain regions.
At the same time, the animals could retain apparently normal behavioral rhythms and sleep–wake cycles when assessed through activity and electroencephalographic measures. In other words, the animals’ visible timing patterns did not reveal the extent of injury occurring within brain cells.
This result does not show that people with Alzheimer’s can have equivalent cellular damage while sleeping normally. It does show why a regular-looking schedule cannot, by itself, be used as a complete readout of the molecular clock or of brain health. A clinical symptom and a cellular process may move together, but they are not the same measurement.
The review also connects circadian regulation with oxidative defenses, mitochondrial stress and neurodegeneration in experimental models. Those findings make the clock biologically relevant to disease mechanisms, while leaving open how much of the relationship applies to human Alzheimer’s and which parts might be altered therapeutically.
Sleep-linked clearance is different from protein breakdown inside cells
One proposed connection between sleep and Alzheimer’s involves the glymphatic system. The review describes this as a fluid-based transport pathway around blood vessels that can help move substances associated with amyloid clearance. Its activity is described as higher during sleep and lower during wakefulness in the evidence discussed.
That idea is important, but it is not a complete explanation of Alzheimer’s biology. Transport around blood vessels is different from the intracellular systems that break down proteins inside cells. The review separately discusses rhythmic protein degradation by the proteasome and notes that the way the circadian clock controls protein breakdown in the brain remains unresolved.
The distinction matters because a change in sleep could plausibly affect one process without proving an effect on every other process linked to amyloid or tau. The review’s glymphatic discussion also leaves the human relevance of these mechanisms open. Findings from experimental systems cannot establish that a particular sleeping position reduces Alzheimer’s risk, nor do they provide a validated clinical measure of glymphatic function in patients.
Amyloid-beta and tau remain central to the review’s account of Alzheimer’s pathology, but the proposed links among sleep, clearance, protein degradation and neurodegeneration involve different mechanisms and different levels of evidence. Keeping those levels separate prevents a plausible biological pathway from being mistaken for a demonstrated treatment effect.
Melatonin’s promise depends on what is being measured
Melatonin is discussed as a possible way to influence disrupted biological timing. In animal and cell models, the review describes effects that include antioxidant activity, protection against mitochondrial dysfunction, reduced amyloid-beta toxicity and changes in pathways associated with tau phosphorylation. These experiments suggest several reasons melatonin might affect disease-related biology under particular conditions.
Those findings answer a mechanistic question: can melatonin influence processes that are relevant to Alzheimer’s in experimental systems? They do not answer the clinical questions that matter to patients and families. A change in amyloid or tau-related biology is not the same endpoint as better sleep. Better sleep is not the same endpoint as less evening agitation or “sundowning.” None of those outcomes, on its own, demonstrates slowed cognitive decline or prevention of Alzheimer’s.
The review’s discussion of clinical interventions is more cautious. It covers melatonin, trazodone and ramelteon in studies involving sleep disturbance, while noting that the available evidence did not establish improved sleep quality for melatonin or trazodone. It calls for more comprehensive trials that assess sleep together with cognitive and pathological outcomes. That combination is important because a treatment could make nights more predictable without changing the underlying course of neurodegeneration, or it could affect a biological pathway without producing a noticeable improvement in daily life.
The same logic applies to non-drug approaches. The review places regular bed and wake times, daytime light exposure and other behavioral measures in the context of managing disrupted rhythms and evening symptoms. Bright light combined with chronobiotic approaches is discussed as potentially useful for sundowning characteristics and related cognitive symptoms in advanced Alzheimer’s. These care-oriented outcomes are meaningful, but they should not be presented as proof that the disease process has been slowed.
The body clock may be both a clue and a target
Changes in sleep timing, rest–activity rhythms and evening behavior could eventually help clinicians recognize when a person’s daily biological organization is becoming less stable. The review presents such patterns as possible early signals, not as a validated standalone diagnostic test.
Circadian dysfunction may also be part of a feedback loop. Alzheimer’s-related pathology could damage the structures that receive light or coordinate daily timing. Disrupted timing and sleep could then influence processes involving inflammation, oxidative stress, protein handling and clearance. The review brings these relationships together, but the human evidence does not identify a single starting point or prove that correcting one part of the loop will halt the others.
The practical challenge is therefore to measure the right outcome. A future intervention might be judged by more consolidated sleep, fewer evening symptoms, a more stable daily rhythm, changes in disease-related biology, preservation of cognition, or some combination of these. Those endpoints should not be collapsed into one claim about “improving the clock.”
What better daily rhythms could mean for Alzheimer’s care
More predictable sleep and daily routines could make life easier for people with Alzheimer’s and for those caring for them, particularly if evening distress and day-to-day disruption become less severe. Light-based approaches, schedule-based care and chronobiological treatments might eventually support that practical benefit if controlled clinical evidence shows that the effects are sustained and meaningful for patients.
That possibility is separate from the much larger ambition of slowing neurodegeneration. The 2022 review makes biological timing an important area for investigation because it touches light input, sleep, cellular clocks and several processes associated with Alzheimer’s. Whether targeting that timing system can change the course of disease remains a question for clinical research rather than a promise established by the evidence reviewed here.
Key Sources
- Primary source: Circadian dysfunction and Alzheimer's disease – An updated review.
DOI or Journal Page · Peer-Reviewed Paper · 2022-08-15
Keep exploring