
Evidence date · 2021-06-22 · Research note 1 of 3
1 2 3
See current Track status →
Cancer immunotherapy helps the immune system recognize and attack cancer. The best-known checkpoint treatments work by blocking inhibitory signals involving CTLA-4 or PD-1 and PD-L1, giving T cells more opportunity to act against a tumor. Because aging changes both immune cells and the tissues around them, it is reasonable to ask whether these treatments become less effective over time.
The answer presented by a review published on June 22, 2021, is more complicated than an age rule. Clinical comparisons discussed in the review produced mixed results. Some analyses found no broad loss of checkpoint-treatment efficacy with age, apart from a possible decline among patients older than 75. Another analysis of metastatic melanoma found better survival among older patients than younger ones. Those comparisons used age groups that treated people younger than 60 or 65 as “young,” even though immune function may already have changed by those ages.
The review instead connects treatment response to several biological processes that can accompany aging. Immune cells may become less diverse or less able to expand. Senescent cells may accumulate in the tumor environment and release inflammatory signals. Yet the clinical findings, animal experiments and cellular measurements do not line up cleanly enough to turn chronological age into a prediction for an individual patient.
Age alone gives an incomplete answer
Checkpoint inhibitors can only help if immune cells can reach a tumor, recognize what they should attack and remain capable of mounting a response. Aging may affect each part of that process, but not in a single direction or at the same intensity in every person or tumor.
The review describes a decline in circulating T cells with age, alongside changes in the T-cell receptor repertoire of naïve cells. The thymus, which helps produce naïve T cells, also undergoes age-related structural and functional changes. At the same time, blood-forming tissues can become skewed toward producing more myeloid cells. These shifts alter the supply and balance of immune cells available to respond to a tumor.
Inside tumors, another problem can develop. Activated T cells may become exhausted, a state associated with sustained expression of inhibitory receptors such as PD-1 and CTLA-4 and with resistance to tumor control. The review describes mouse work in which highly exhausted T cells increased with age and responded less effectively to activation. In one experiment, combined PD-L1 and CTLA-4 blockade was less effective in older mice than in younger mice.
Those observations help explain why aging could matter biologically. They do not establish that an older person will respond poorly to immunotherapy. The clinical analyses summarized in the review involved different cancers, age boundaries and patient populations, while the animal experiments used particular tumor models. The result is a plausible set of influences rather than a reliable age-based forecast.
Two routes from aging to a weaker immune response
One route runs through immune-cell fitness. Fewer circulating naïve T cells, a narrower receptor repertoire and more cells with exhausted or senescence-like features could reduce the number of lymphocytes able to respond when a checkpoint is released. The review also discusses the possibility that some T cells acquire characteristics associated with cellular aging while retaining some functions, making their classification less straightforward than a simple active-versus-inactive division.
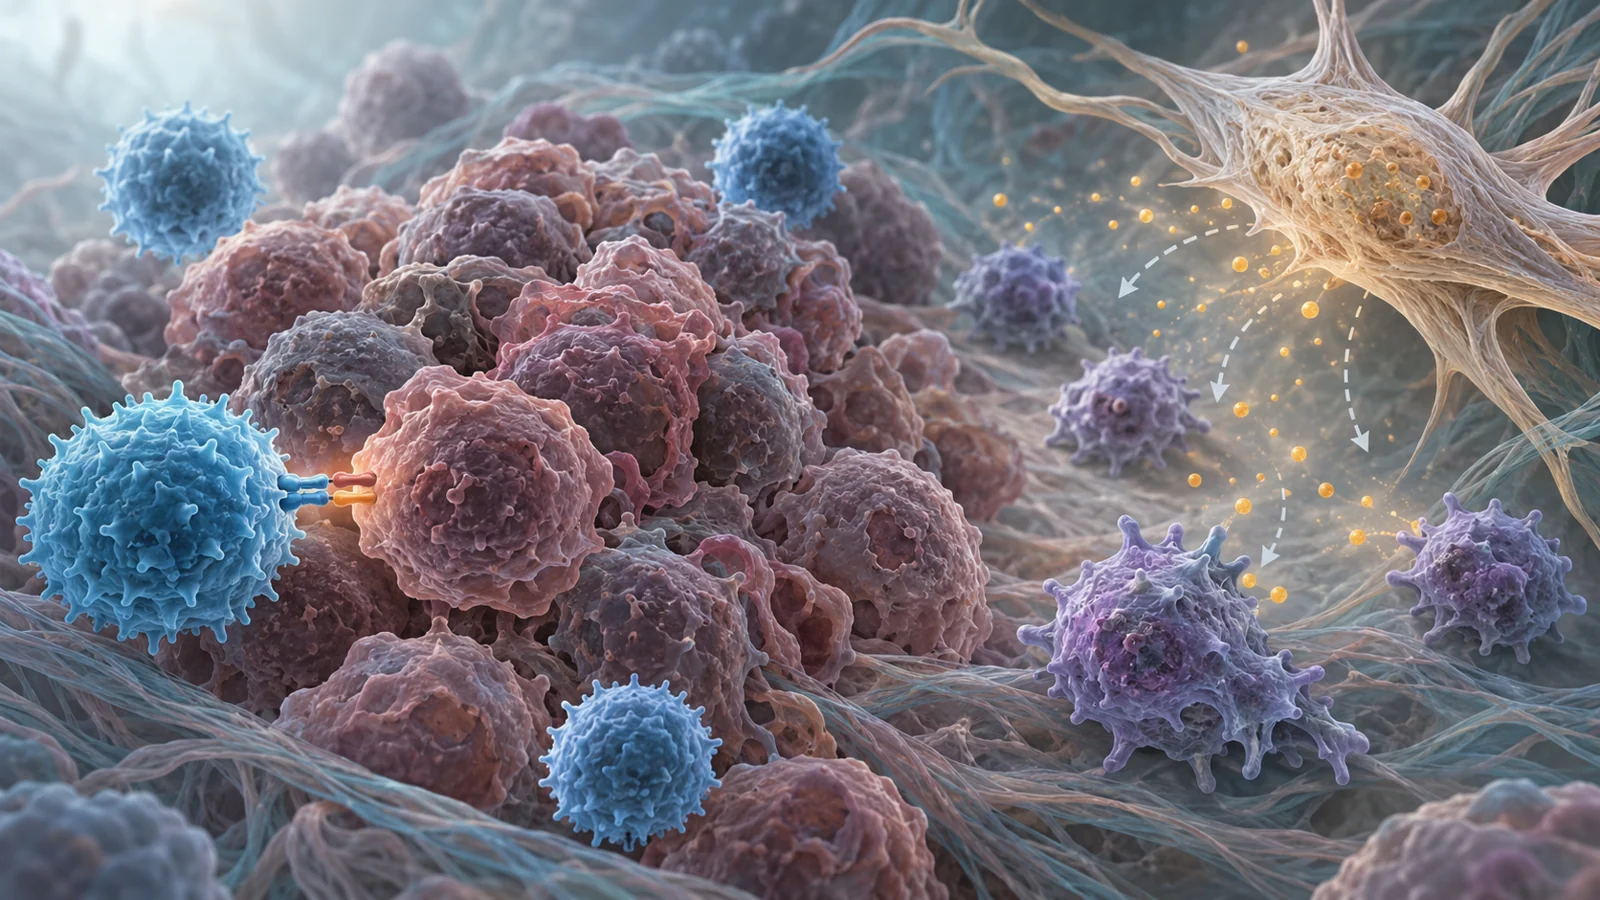
The second route runs through the tumor microenvironment, the network of cells and signals surrounding cancer cells. Senescent cells stop dividing persistently, but they remain metabolically active. A key feature described in the review is the senescence-associated secretory phenotype, or SASP, which can include inflammatory cytokines, growth factors and matrix-remodeling enzymes.
Senescent stromal cells provide one concrete example. Stromal cells help organize the tissue around a tumor, and senescent versions can release signals such as IL-6 and IL-8. In mouse studies discussed by the review, senescent stromal cells increased the recruitment of suppressive myeloid cells and promoted tumor growth. Related findings suggest that signals from senescent fibroblasts can encourage monocytes to develop toward an M2 macrophage state and can increase PD-L1 expression in tumor cells.
These findings offer a possible route by which aging tissue could make checkpoint treatment harder: the surrounding environment may become more capable of suppressing immune attack or helping tumor cells evade it. The experiments support the tissue pathway, while the effect on checkpoint-treatment success remains an inference that needs to be tested directly. Cancer-associated fibroblasts are also highly varied and difficult to identify, and they should not be treated as interchangeable with senescent fibroblasts.
A senescent cell is harder to identify than its label suggests
A proposed treatment to remove senescent cells needs a defensible way to identify its target. The review emphasizes that cellular senescence has several features rather than one universal marker. Researchers may look for SA-β-gal, inhibitors such as p16 or p21, persistent DNA damage, changes in chromatin, SASP components or lipofuscin deposits. A combination of characteristics is generally more informative than any single measurement.
This problem becomes especially visible in T cells. One mouse reporter study found that fewer than 1% of circulating T cells expressed p16 in aged animals. A human study using SA-β-gal measurements estimated that senescence-marker-positive T cells could account for as much as 60% of T cells in people older than 60. Those figures are not directly comparable. They came from different species, markers and measurement systems, and the mouse reporter may have missed some p16-expressing cells.
The functional evidence is also mixed. In the human work discussed by the review, cells identified as senescent showed impaired proliferation. Other researchers have used a CD45RA-positive, CD57-positive and CD28/CD27-deficient phenotype to describe senescence-like effector-memory T cells, which become more common with age and proliferate less than some comparison cells. Yet another study found similar proliferation between CD57-positive and CD57-negative T cells.
Cellular senescence, broader immune aging and T-cell exhaustion therefore overlap without being identical diagnoses. A marker can indicate a changed state without proving that the cell is a safe or useful target for removal. It also does not show that every cell carrying that marker is harming the immune response. A senescence-targeted therapy would need to distinguish damaging populations from cells whose removal could create new problems.
Older mice and older patients do not form a simple comparison
Age is difficult to model in cancer research. The review notes that most people receiving cancer treatment are over 60, while many mouse experiments use animals only three or six months old. The authors frame a patient over 60 as more comparable to a mouse around 15 to 18 months old, yet older animals are less common in preclinical studies.
When aged mice have been used, checkpoint responses have sometimes been weaker. Anti-CTLA-4 and anti-PD-L1 treatment reduced B16 melanoma growth less effectively in mice 19 to 26 months old, alongside fewer infiltrating and activated lymphocytes in the tumors. That is an important experimental observation, but it does not make every tumor in every older host behave the same way.
Tumor growth itself varies with age and model. Some melanoma, mammary and other tumors grew faster in young mice; some grew more slowly in older mice; others showed no clear age effect. In certain models, slower growth in older animals was associated with more CD8 T-cell infiltration. In others, faster growth was linked to more tumor-associated macrophages or greater remodeling of the surrounding tissue. The review reports an association between larger baseline tumors and checkpoint resistance. It proposes slower tumor growth as one possible explanation for better outcomes in some older patients.
The clinical comparisons have their own limitations. Grouping everyone under 60 or 65 together as “young” can conceal meaningful changes in immune fitness, while patients above a particular age may still differ substantially in health, tumor biology and treatment history. The review’s central lesson is not that animal findings are irrelevant, but that the age of the model, the tumor being studied and the comparison group all shape what a result can mean.
Removing senescent cells brings a safety problem
Senolytics are drugs intended to eliminate senescent cells. If senescent cells help maintain an immunosuppressive tumor environment, removing them could theoretically improve immune access or reduce signals that support tumor growth. The review discusses ABT263, also called navitoclax, in the broader context of senescent-cell clearance.
The possible benefit is separate from whether a particular drug removes the relevant cells safely. Navitoclax had already been tested in cancer trials, where it showed limited effectiveness and severe treatment-induced thrombocytopenia, meaning a dangerous reduction in platelets. This platelet toxicity is a concrete safety concern for the proposed use of navitoclax alongside checkpoint treatment.
The review’s authors state that, to their knowledge, preclinical evaluation of a senolytic combined with a checkpoint inhibitor was still lacking. That places the combination at a proposed-intervention stage in this account. It was not an established treatment, and the review did not identify a validated test for selecting patients whose tumors would benefit from it.
A useful senolytic strategy would therefore require more than evidence that a compound can kill cells carrying a senescence-associated feature. Researchers would need to establish which cells matter in the tumor environment, whether the drug reaches them, whether their removal improves immune control and whether the harms remain tolerable. The safety question is part of the biological question, not an afterthought.
The surrounding signals may matter as much as the cells
Eliminating senescent cells is only one possible approach. Another is to change the inflammatory signals they or nearby cells release. This route also demands precision because inflammation can suppress immunity in one setting and help immune cells attack a tumor in another.
The review describes an attempt to block IL-6, a cytokine that can contribute to the recruitment and suppressive activity of myeloid-derived suppressor cells. In melanoma, IL-6 blockade did not improve the effect of PD-1-blocking antibodies in the experiment discussed. The authors suggest that IL-6 may also be needed for some immune-cell activation, and that the strategy could behave differently in older patients, who may have higher circulating IL-6 levels. That possibility remained a hypothesis rather than a demonstrated age-specific benefit.
Interferon-related findings show why exposure pattern matters. Sustained type I interferon signaling was associated with resistance to checkpoint treatment in a B16 melanoma setting, involving increased expression of several inhibitory pathways. Type II interferon could also make tumor cells more resistant to cytotoxic CD8 T cells in the described experiments. Yet type I interferon released by tumor-infiltrating T cells was associated with the elimination of suppressive myeloid cells and successful anti-PD-1 therapy in another setting.
In aged mice, an intervention that stimulated type I interferon signaling increased the efficacy of anti-PD-L1 and anti-CTLA-4 treatment. The review’s authors interpret the contrasting findings as suggesting that short-term rather than chronic activation might help older patients. Responses to type I interferon signaling were also reduced in T cells from older humans in the comparison described by the review, adding another layer to the question of how an intervention would behave in patients.
What this could change
Patients whose tumors resist immune attack because senescence-related changes in the surrounding tissue create a suppressive environment could eventually gain better tumor control from checkpoint treatment paired with a targeted intervention in that environment. Reaching that possibility would require the relevant mechanism to be demonstrated in patients, and changing it would have to improve outcomes without causing unacceptable harm.
The practical payoff would be a more precise way to improve immunotherapy: not excluding people because they are older, and not removing every cell that carries a senescence-associated marker, but identifying a harmful tissue interaction and interrupting it selectively. The review places that prospect alongside substantial unanswered questions about markers, tumor models, treatment timing and toxicity. Those questions determine whether the idea becomes a useful clinical strategy or remains a plausible explanation for why some checkpoint treatments fail.
Key Sources
- Primary source: Senescence and Aging: Does It Impact Cancer Immunotherapies?
DOI or Journal Page · Review or Meta-Analysis · 2021-06-22