
Research Signal – Source date 2025-05-30
REM sleep behavior disorder raises a difficult prevention question: could treatment begin early enough to delay later movement, cognitive or daily-function problems associated with synuclein-related neurodegeneration?
A ClinicalTrials.gov record describes a phase 2 study testing adalimumab against placebo in people with idiopathic REM sleep behavior disorder. The record was dated May 30, 2025, but that date identifies the registry entry rather than the beginning of participant treatment. The current record lists an actual study start date of August 17, 2026 and recruiting status, with primary completion estimated for August 2029 and overall completion estimated for January 2030. No results are posted.
The current record describes the protocol details discussed here. Its central question is whether adalimumab can slow or prevent synuclein-related neurodegeneration in this population, and whether any difference in brain imaging is accompanied by a meaningful clinical benefit.
The study starts with a prevention question
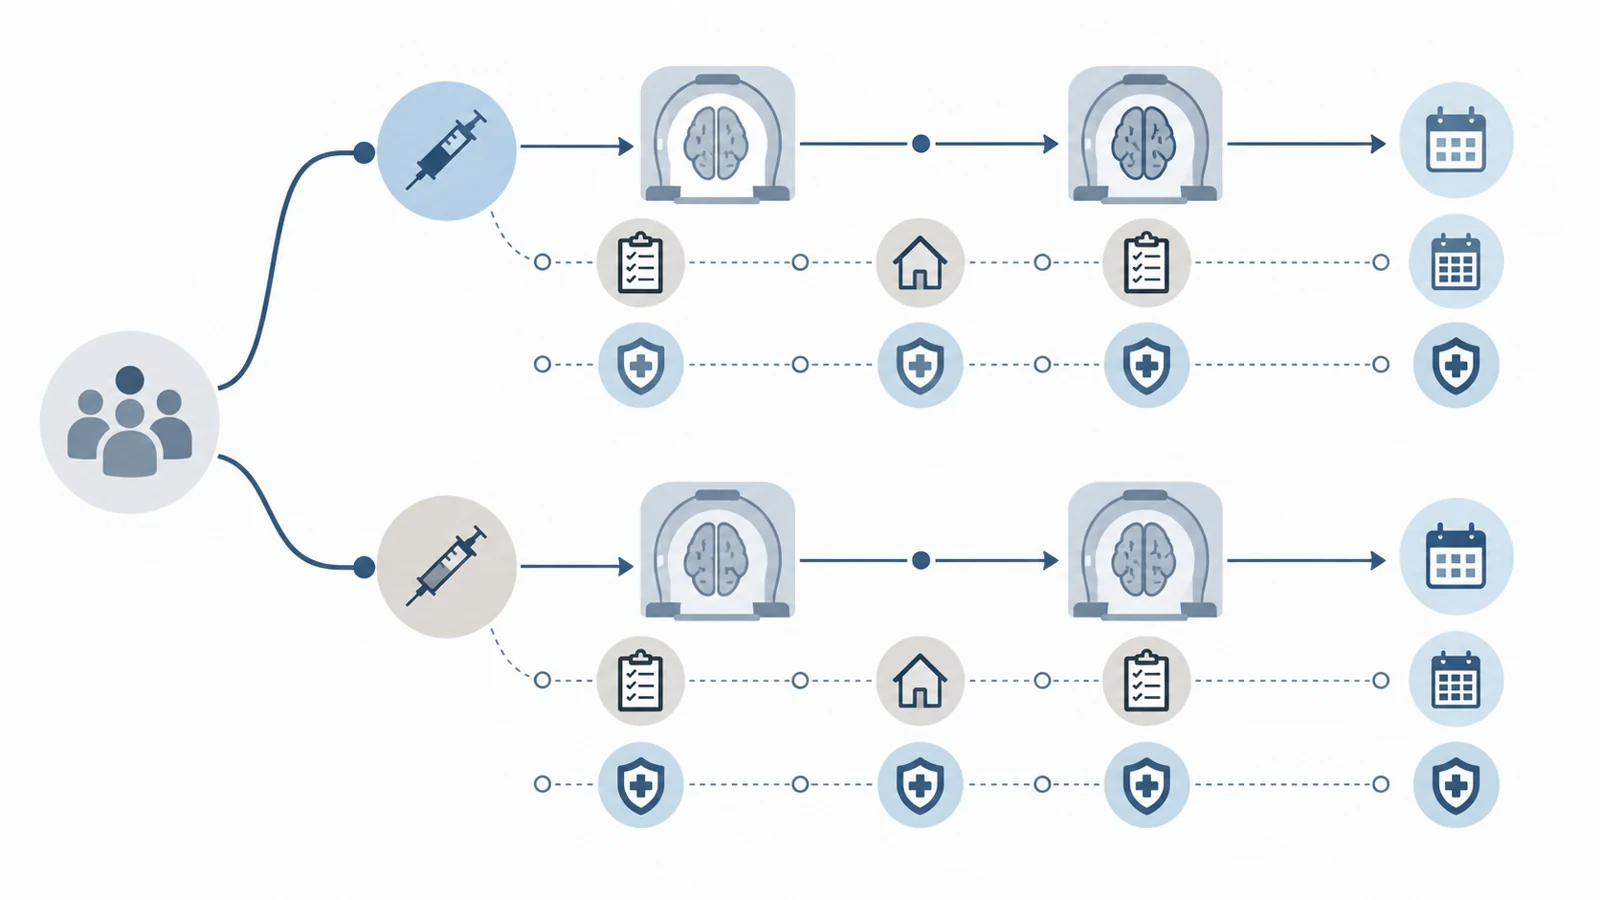
The planned study is randomized, parallel and placebo-controlled, with estimated enrollment of 108 adults ages 50 to 80. Participants are assigned in equal proportions to adalimumab or matching placebo. The intervention is a 40 mg injection under the skin every two weeks for up to two years, following a 12-week screening period.
This design gives investigators two groups moving through the same broad timetable. Participants have clinic visits after the first dose at weeks 4, 12 and 24, followed by visits at about six-month intervals through Week 96. Motor and cognitive assessments are also completed at home between some in-person visits. At six-month intervals, body-worn sensors are used for seven days to record activity during sleep and wakefulness.
Those details matter because prevention is a question about change over time. People in both groups may experience changes while they remain under observation, and measurements can vary from visit to visit. Comparing the active-treatment group with a placebo group that follows the same study schedule gives the investigators a way to ask whether the pattern differs between assignments, rather than simply whether participants changed from their own starting point.
The scan is only one part of the answer
The primary outcome is a change from baseline to Week 96 in expression of the Parkinson Disease Related Pattern, or PDRP, measured with FDG PET brain imaging. In plain terms, the scan supplies a defined biological measurement that can be compared between the two groups at the start and near the end of treatment.
A scan result and a patient-level outcome are related questions, but they are not interchangeable. A change in PDRP expression would describe what happened to the imaging measure. It would not by itself show that a person avoided a diagnosis, retained daily functioning or experienced better quality of life. To support the hope of delaying disabling disease, the imaging result would need to sit alongside a meaningful clinical difference.
The study therefore includes a secondary composite endpoint. A participant is considered to have met it only when at least one milestone is reached at two consecutive study visits at least three months apart. The milestones include a worsening of more than two points on the combined MDS-UPDRS Parts 1b and 2, a motor-score increase of more than four points on Part III, or a decline of more than three points on the MoCA cognitive assessment. The endpoint can also be reached if a movement-disorders or cognitive-disorders specialist diagnoses Parkinson disease, dementia with Lewy bodies or multiple system atrophy, or if medication is started for related symptoms.
This composite brings the trial closer to the experiences that prevention is meant to affect: everyday function, movement, cognition, diagnosis and the need for symptom treatment. Participants who meet one of these clinical milestones remain in the study until its termination, allowing follow-up to continue rather than ending at the first sign of change.
What the exploratory tests could clarify
The study also asks biological questions that are separate from its primary imaging outcome. Exploratory assessments examine biomarkers of immune-system dysfunction, selected biomarkers associated with neurodegeneration and measures of quality of life. The immune measurements are intended to help evaluate whether biological features might predict response to treatment. That is an objective of the study, not a capability already demonstrated by the registry record.
A planned cerebrospinal-fluid substudy makes the question more concrete. Approximately 25 participants in each treatment group are expected to undergo lumbar punctures at baseline and then yearly. The samples are intended to support measurements of immune processes and neurodegeneration in cerebrospinal fluid.
These tests could help connect treatment assignment with changes in the body and nervous system, or show whether a clinical pattern is accompanied by a measurable biological pattern. They remain exploratory: their role is to help interpret the trial and generate evidence about response, not to substitute for the clinical endpoint.
Prevention also has a safety price
A preventive strategy has to justify treatment before a person has received a demonstrated benefit from it. The planned exposure is substantial enough that the study includes dedicated safety surveillance throughout the 96-week treatment period and afterward.
The record lists monitoring for adverse events and laboratory abnormalities, as well as serious infections. It also tracks signs and symptoms suggestive of new-onset demyelinating disease and new demyelinating lesions on brain MRI. Demyelination refers broadly to damage involving the protective covering around nerve fibers. Investigators will also look for antibodies that the body develops against adalimumab.
A safety follow-up visit is planned 70 days after the last dose. These checks show what risks the protocol is designed to watch for; they do not provide observed rates of harm or establish that the balance between benefit and risk is acceptable. That balance is especially important when the hoped-for payoff is a future delay in disease-related problems rather than relief that can be measured immediately.
What earlier intervention could mean for patients
The practical promise of this strategy is time. If the trial eventually shows a durable clinical benefit, people with idiopathic REM sleep behavior disorder could have more time before movement, cognitive or daily-function difficulties emerge or worsen. The brain-imaging result could strengthen that interpretation only if it aligns with patient-level outcomes and remains compatible with an acceptable safety balance.
The current registry presents a carefully defined prevention test, not evidence that adalimumab has already delayed neurodegeneration. Its importance lies in asking whether an intervention delivered during this earlier stage can preserve everyday capability for longer, while measuring both the biological signal and the burdens of treatment needed to pursue that possibility.
Key Sources
- Primary source: An Exploratory Study of the Potential for Rational Immune System Manipulation to Prevent Emergence of Synucleinopathy Manifestations in Persons With REM Sleep Behavior Disorder (RBD)
Government or Regulator · Clinical Trial · 2025-05-30
Keep exploring