
Research Signal – Source date 2025-12-10
For thousands of years, hopes of preserving youth were expressed through ambrosia, Taoist elixirs, and medieval aqua vitae. Modern geroscience asks a more specific question: if aging biology can be changed, could people spend more years healthy, capable, and independent?
A review published on December 10, 2025, titled From Elixirs to Geroscience, traces how that question moved from myth and speculation toward experiments on cells, animals, and early human interventions. Its account does not show that any treatment reliably extends human lifespan. It does show why researchers are testing whether common mechanisms of aging can be targeted before they produce several chronic diseases at once.
When aging became a biological problem
A major shift came in the late nineteenth and early twentieth centuries, when aging began to be treated as a biological process rather than only an inevitable stage of life. Some early attempts were highly speculative. The review describes experiments such as Voronoff’s grafting work as part of a period when scientists were trying to rationalize rejuvenation claims with the tools available at the time.
By the mid-twentieth century, cellular biology offered a more testable vocabulary. Leonard Hayflick’s discovery in 1961 that human fibroblasts have a finite replicative capacity, later known as the Hayflick limit, helped establish that cells do not divide indefinitely. Work on telomeres and telomerase added another way to study cellular aging. Denham Harman’s oxidative stress theory also prompted decades of research into antioxidants, although clinical benefits from antioxidant and vitamin use have been inconsistent.
Geroscience grew from this shift. Rather than treating each age-related illness as entirely separate, it connects aging mechanisms with the onset of multiple diseases. The goal is not to deny aging or promise a return to youth. It is to ask whether slowing or modifying shared biological processes could delay the loss of function that makes later life more vulnerable to disease.
The cell systems researchers are trying to influence
Several nutrient-sensing pathways sit near the center of this research. mTOR, AMPK, and the sirtuins respond to information about nutrients, energy, and cellular stress. Their activity helps regulate growth, metabolism, autophagy, and other maintenance processes. When these systems are altered, cells may change how they allocate resources between growth, repair, and stress resistance.
That makes them attractive research targets, but also makes simple interpretations difficult. A pathway involved in aging is usually involved in many ordinary functions as well. Drugs or diets that alter it may affect immune activity, metabolism, tissue maintenance, or other processes at the same time.
Aging also involves communication between cells and tissues. The review describes inflammaging as persistent, low-grade inflammatory signaling without an overt infection. Cytokines such as interleukin-6, tumor necrosis factor-alpha, interleukin-1 beta, and macrophage migration inhibitory factor can contribute to an environment associated with tissue dysfunction, frailty, atherosclerosis, diabetes, and neurodegeneration. Senescent cells, mitochondrial dysfunction, damage signals, and impaired autophagy can all help sustain that environment.
This is why geroscience investigates a range of approaches, including caloric restriction, fasting-mimicking diets, rapalogues, metformin, NAD+ boosters, sirtuin activators, and compounds intended to remove senescent cells. The common idea is to influence biological processes that may connect several forms of age-related decline. The interventions are not interchangeable, and changing one marker or pathway does not automatically translate into more independent years of life.
Longer-lived animals do not answer the human question alone
Rodents have provided some of the strongest experimental evidence for modifiable aging biology. In the models reviewed, caloric restriction can extend lifespan and healthspan. Rapamycin and changes to growth hormone or IGF-1 signaling have also revealed mechanisms that appear to be conserved across species. In some genetically modified mice, clearing senescent cells improved frailty, preserved organ function, and delayed multiple age-related problems.
Yet a laboratory mouse is not a small human. Researchers are increasingly using older animals, both sexes, genetically diverse strains, and models that include multimorbidity or social stress. These designs may better represent the uneven health, medication use, and disease burden found in later life.
Rhesus macaques provide a closer comparison in some respects. Decades-long caloric-restriction studies described by the review found improvements in metabolic health and immune function, along with delayed onset of some diseases. The findings on lifespan were mixed. That difference matters because better metabolic measures, delayed disease, and a longer total lifespan are separate outcomes.
An intervention might improve a physiological system without adding years to life. It might extend life without preserving independence. Or it might delay several diseases while producing harms that offset some of the benefit. Animal studies can reveal mechanisms and test causality, but the meaning of a result depends on the species, the model, the timing of treatment, and the outcome being measured.
Senescent cells can be harmful and useful
Senolytics are drugs intended to selectively eliminate senescent cells. In some settings, senescent cells accumulate and release inflammatory molecules as part of their senescence-associated secretory phenotype, or SASP, helping sustain inflammatory signaling. Animal studies have therefore tested whether removing them can reduce frailty, preserve organ function, or delay disease.
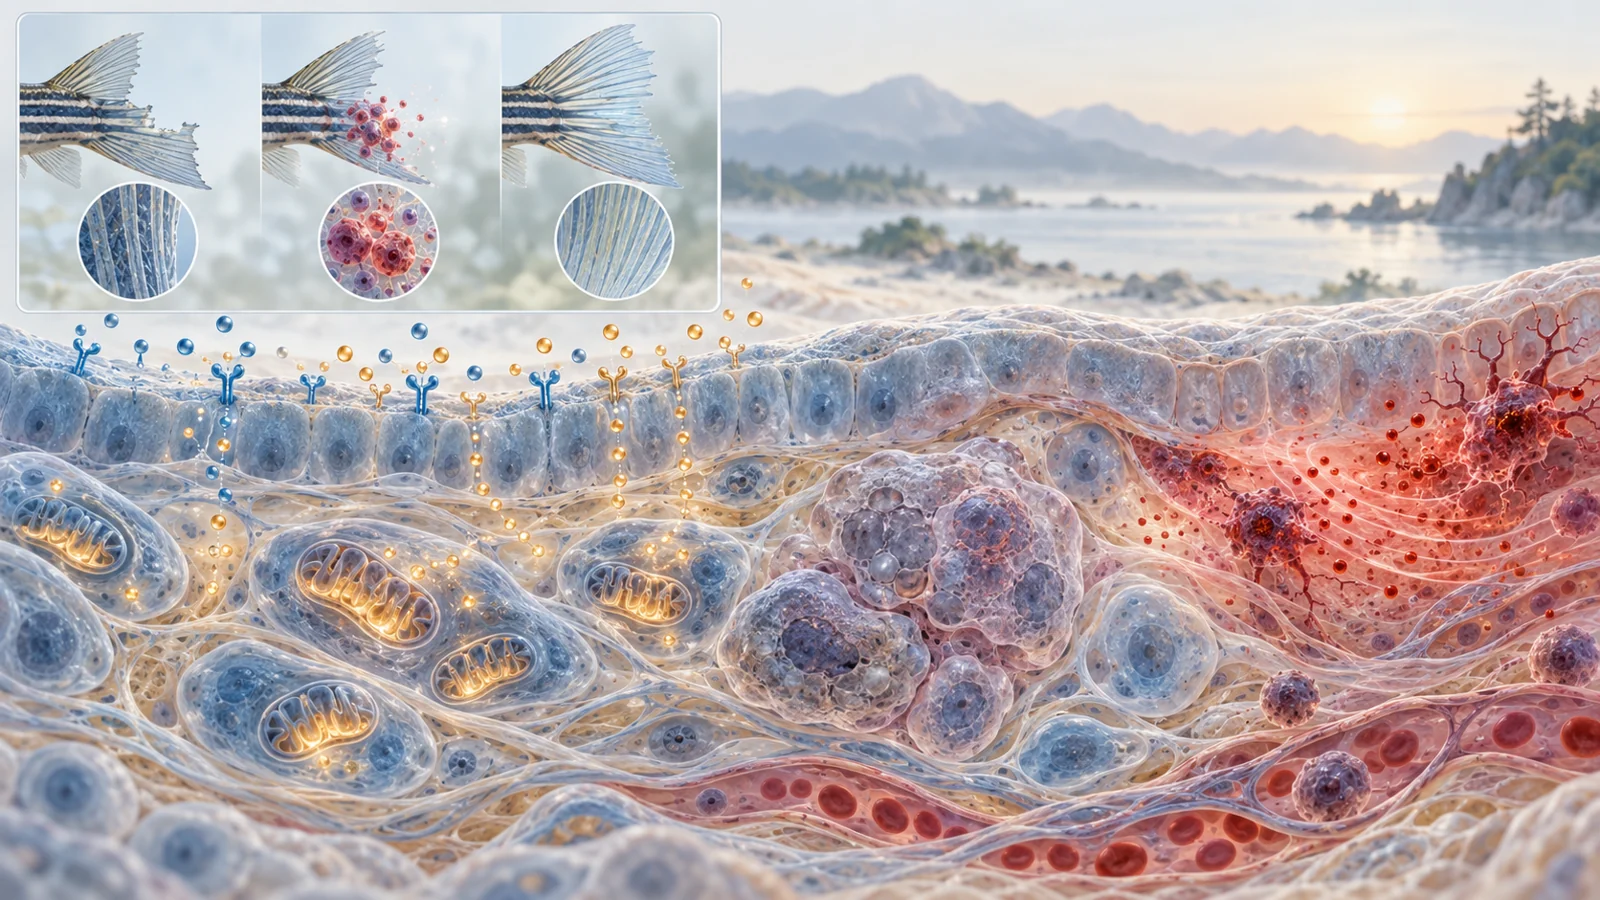
The biology is not as simple as treating every senescent cell as disposable. The review describes transient senescence during tissue repair in zebrafish, including regeneration of fins and hearts. In axolotls, senescence can support the formation of the blastema, the specialized structure involved in replacing lost tissue. In these settings, senescence appears to participate in repair rather than simply mark deterioration.
The lesson is about tissue and timing. Persistent senescent-cell signaling may contribute to chronic inflammation, while a temporary senescent state can help coordinate regeneration. Findings in fish and amphibians do not establish what senolytic treatment would do to human tissue repair. They do, however, show why a therapy aimed at a broad cellular state requires careful control over which cells are removed, when they are removed, and what the surrounding tissue needs to recover.
Early human studies measure pieces of the promise
The review describes several early human findings, but they address different levels of the question. In one example, low-dose everolimus, a rapamycin derivative, enhanced the immune response to influenza vaccination in older adults. That is an immune-function outcome: it suggests that a treatment may alter how the aging immune system responds to a defined challenge.
The MILES study offers a different kind of result. The review reports that metformin produced transcriptional changes in human tissues consistent with patterns associated with caloric restriction, mitochondrial efficiency, and reduced inflammation. This is a molecular finding, not a demonstration that participants avoided multiple diseases or retained independence for longer.
Those distinctions are central to interpreting geroscience. A stronger vaccine response and a change in gene expression can both be valuable clues, but neither alone establishes durable disease prevention. The more ambitious endpoint would be a measurable delay in several age-related conditions, accompanied by preserved physical and cognitive function over years.
That endpoint is difficult to build into a trial. Disease-specific medicines can often be tested against one defined outcome. A geroprotective intervention is intended to influence several conditions at once, so researchers have considered composite outcomes such as those discussed in connection with TAME. The review presents this as part of a wider effort to test whether aging itself can be addressed through clinically meaningful measures.
Epigenetic clocks, proteomic signatures, and immune profiles may help estimate biological age, but the review emphasizes that promising biomarkers are not yet established substitutes for long-term health outcomes. A marker can move before a patient feels better, remain unchanged despite a useful effect, or change without leading to fewer illnesses. The central challenge is connecting molecular movement with years of real-world function.
The longer the treatment, the higher the safety bar
A treatment intended for otherwise healthy people must meet a demanding benefit–harm standard. Many older adults live with several conditions, take multiple medicines, and have different levels of functional reserve. Sex, genetic background, lifestyle, and existing illness can also influence both response and risk. A regimen that is tolerable in one group may not be suitable for another.
Rapamycin and related rapalogues show why dosing and safety cannot be separated from the longevity question. The review describes adverse effects including stomatitis, hyperlipidemia, delayed wound healing, edema, and infection risk. It also notes that chronic daily dosing is not tolerated in the studies discussed, which has led researchers to examine intermittent schedules. Such findings do not amount to a preventive treatment recommendation; they show how much optimization is required before a drug can be considered for long-term use in broadly healthy populations.
The same issue applies across the field. A possible benefit that appears after years of treatment must be weighed against harms that may be uncommon but consequential when millions of people are exposed. Reliable biomarkers, representative participants, clinically meaningful endpoints, and long follow-up are therefore not administrative details. They determine whether an apparent change in aging biology is safe and useful outside an experimental setting.
Access is another part of the translation problem. Advanced gerotherapeutics, regenerative approaches, or personalized interventions could initially reach wealthy groups first. If the gains from targeting aging are available only to a privileged minority, the result could widen health disparities rather than reduce age-related illness across society.
What targeting aging could mean for healthy later life
The most important potential benefit is not a dramatic reversal of appearance. It is a later life with fewer overlapping chronic illnesses, more resilience, and a longer period in which people can live independently. That could reduce illness-related pressure on families and health services as well as improve the daily experience of older adults.
This future remains conditional. It depends on interventions producing sustained clinical gains rather than isolated changes in biomarkers, while avoiding harms that accumulate during prolonged use. It also depends on trials showing that benefits extend across the varied populations who age in the real world, and on health systems making effective approaches available beyond a privileged minority.
The historical movement from elixirs to geroscience has therefore changed the question more than it has settled the answer. Aging mechanisms may be experimentally modifiable, but the public-health value of doing so will be measured in fewer disabling diseases and more years of healthy independence.
Key Sources
- Primary source: From Elixirs to Geroscience: A Historical and Molecular Perspective on Anti-Aging Medicine.
DOI or Journal Page · Review or Meta-Analysis · 2025-12-10
Keep exploring