
Research Signal – Source date 2021-07-06
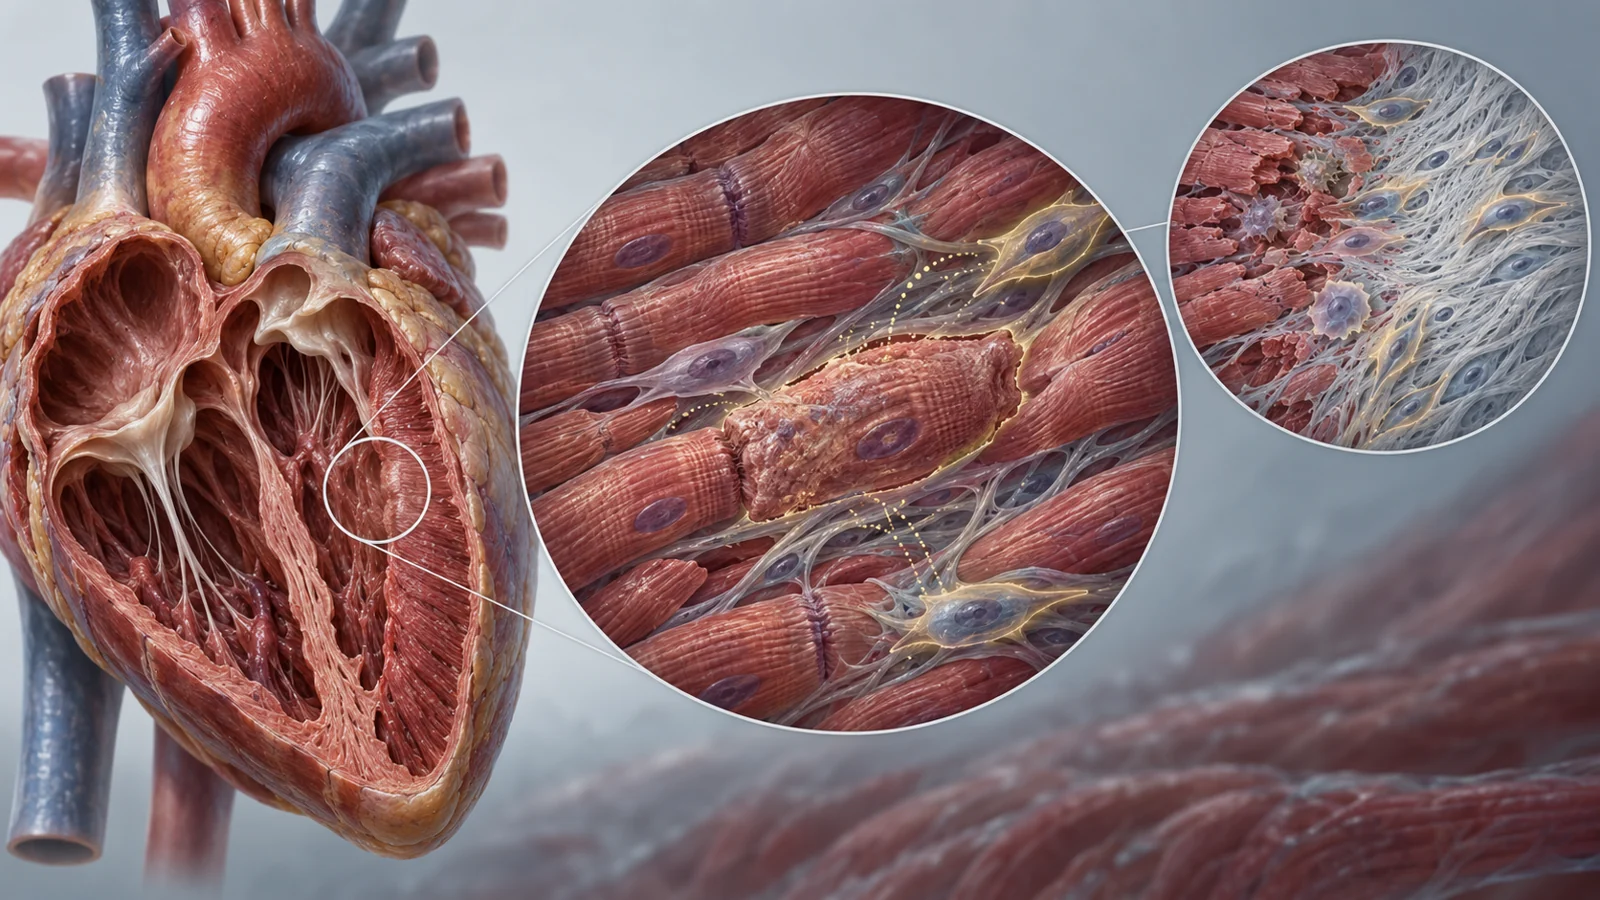
An aging heart faces a difficult tradeoff. Cells altered by long-term stress may disrupt the tissue around them, yet removing heart-muscle cells is not obviously safe because adult hearts have limited ability to replace lost muscle. Senolytics are drugs designed to exploit that tension by preferentially clearing senescent cells, a state associated with stress, damage responses and inflammatory signaling.
A July 2021 review, Senescence and senolytics in cardiovascular disease: Promise and potential pitfalls, brings together the early cardiovascular evidence. Its mouse studies suggest that reducing senescent-cell activity can improve some measures of heart function and remodeling. They also show why a useful treatment would need to do more than remove cells. It would have to clear the right cells, at the right time, with an exposure that does not interfere with repair or create unacceptable toxicity.
Aging changes the heart’s cellular neighborhood
Cellular senescence is commonly described as an irreversible loss of the ability to divide. That definition is not enough to explain what happens in the heart. Cardiomyocytes, the muscle cells that contract, are largely post-mitotic, but they can still develop senescence-associated changes after accumulating stress. The review discusses telomere-associated DNA-damage foci linked to mitochondrial dysfunction and oxidative stress in aging cardiomyocytes.
A senescent cell is not simply inactive. It can remain metabolically active and release a mixture of inflammatory cytokines, chemokines, growth factors and matrix-remodeling enzymes known as the senescence-associated secretory phenotype, or SASP. In cardiac tissue, the review describes senescent cardiomyocytes producing signals that can influence nearby muscle cells and fibroblasts. In laboratory work, those signals were associated with changes such as hypertrophy and fibroblast differentiation, processes relevant to the remodeling of heart muscle.
Senescent cells can also become unusually resistant to apoptosis, the programmed cell-death process that normally removes unwanted cells. Senolytics attempt to target the survival networks that help these cells persist. The pathways discussed in the review include members of the Bcl-2 family, p53 and p21-related signaling, PI3K and other pro-survival systems. Blocking parts of those networks can make senescent cells more vulnerable to apoptosis than healthy proliferating or quiescent cells.
The word “preferentially” matters. Senolytics are not meant to be a general cell-killing treatment, and senescent cells are not a single uniform population. The review emphasizes that identifying them in living tissue is difficult because no single marker captures every senescent cell. A combination of markers is usually needed, and different drugs may affect different cell types. Those biological details help explain why one cardiovascular result cannot automatically be extended to every aging heart.
The mouse results measured different things
The clearest comparison in the review comes from studies of naturally aged mice treated with different senolytic approaches. In 24-month-old mice, repeated short courses of navitoclax reduced senescence-associated features in cardiomyocytes, lowered components of the SASP, reduced cardiomyocyte hypertrophy and interstitial fibrosis, and lowered left-ventricular mass. Functionally, the reported improvement was in diastolic function, meaning the heart’s ability to relax and fill. Systolic function, the pumping phase, did not change in those studies.
That distinction is important for readers because “better heart function” can hide different physiological measurements. A heart may pump out a similar proportion of blood while becoming better or worse at relaxing between beats. The navitoclax findings therefore point to a specific change in age-associated remodeling and filling performance, not to a generalized restoration of youthful cardiac function.
A separate study of aged mice used a single dose of dasatinib plus quercetin, often abbreviated D&Q. The review reports an improvement in ejection fraction, a measure of systolic performance, without a change in cardiac mass. The authors discuss a possible vascular explanation: senolytic activity involving endothelial cells might improve vascular relaxation. But the study did not quantify senescent-cell numbers within the heart, so that proposed mechanism was not directly demonstrated.
The two results cannot be ranked as if they were head-to-head trials. The compounds differed, as did the dosing schedules, the biological targets that may have been affected and the methods used to assess cardiac function. The review notes that imaging and echocardiographic assessments, along with differences in treatment conditions and cell-type specificity, could contribute to the contrasting outcomes. Navitoclax’s effect on diastolic function and D&Q’s reported effect on ejection fraction are therefore separate observations, not evidence that one is the winning senolytic.
The review also describes a different experiment involving ischemia and reperfusion. In mice, temporary blockage of a coronary artery was followed by restoration of blood flow. Navitoclax was started four days after the injury. As reported by the review, treatment reduced the senescent-cell burden, improved left-ventricular function, reduced adverse remodeling and scar size, and increased myocardial vascularization. Several inflammatory, profibrotic and anti-angiogenic signals were also reduced.
Those findings make the idea more interesting, but they do not turn the four-day start into a clinical treatment window. Nor do the short follow-up periods answer whether the functional changes persist. In one set of aged-heart studies, improvement was assessed about five weeks after treatment. Longer-term cardiac adaptation, survival and the consequences of clearing cells that cannot readily be replaced remained open questions.
After injury, timing becomes part of the treatment
A heart attack creates a sequence rather than a single problem. Damaged muscle cells die, immune cells remove debris, inflammation helps organize the injured area and a scar gradually provides structural support. Early inflammation and scar formation can become harmful when excessive or persistent, but they also have necessary roles in stabilizing a weakened ventricle.
This is why preventing senescence and eliminating cells after senescence develops are different interventions. Blocking the formation of senescence could alter the tissue’s response from the beginning. A senolytic, by contrast, is intended to kill cells after they have entered a senescent state. The timing of that clearance determines which cells are present, what signals they are producing and what repair phase the heart has reached.
The review uses transforming growth factor beta, or TGF-β, to illustrate the problem. Early interruption of TGF-β signaling after a heart attack was associated with worse cardiac dysfunction and higher mortality in the cited work, while later disruption could reduce fibrosis and hypertrophic remodeling. In the ischemia–reperfusion mouse experiment, senolytic treatment reduced TGF-β along with other signals. A reduction in an inflammatory or fibrotic signal may look beneficial when remodeling is excessive, but the same pathway can participate in the transition toward repair.
Scar is another example. After extensive muscle loss, the infarcted region is mechanically weak. A sufficiently strong scar helps preserve the structure of the ventricle. The review notes that excessive inflammation and matrix-degrading activity can contribute to poor healing, but it also raises a theoretical concern that clearing senescent myofibroblasts or cardiomyocytes near the infarct could weaken the repair response and increase susceptibility to rupture. The mouse result showing a smaller scar is therefore not automatically equivalent to a safer or stronger heart.
Age adds another complication. Patients who experience a heart attack are often older and may already have accumulated senescent cells before the injury. An older heart may also have less regenerative capacity and more stem-cell dysfunction. The same intervention could therefore clear a larger population of senescent cells in an older heart while leaving fewer resources for replacement or repair. A treatment that helps a younger experimental animal after a defined injury cannot be transferred unchanged to that setting.
The drug is part of the risk
Some hazards arise from the biology of cell clearance. Others belong to the particular drug used to achieve it. Navitoclax inhibits Bcl-XL in platelets, making thrombocytopenia its dose-limiting toxicity. The review describes platelet counts recovering after treatment stopped in cancer settings and notes that some studies did not report clinically relevant bleeding, but those observations come from different treatment contexts.
Dasatinib brings a different safety profile. In prolonged daily treatment for chronic myelogenous leukemia, the review reports thrombocytopenia in more than 40% of patients, along with platelet dysfunction that can contribute to bleeding. It also describes potentially relevant cardiac effects, including QT prolongation, arrhythmia and palpitations in a portion of treated patients, with rare reports of severe heart failure or ventricular dysfunction. The review notes that navitoclax did not show significant cardiac toxicity in the cited setting, but that contrast does not make either drug’s risk profile interchangeable with a short senolytic course.
Exposure is therefore part of the proposed solution. Because senescent cells may take a long time to accumulate, the review discusses a “hit-and-run” strategy in which a brief, intermittent treatment might remove enough of them to produce a lasting tissue benefit while limiting cumulative toxicity. A preclinical suggestion that clearing roughly 30% of senescent cells can be beneficial is not a validated cardiovascular dosing rule. Intermittent treatment still requires its own evidence on platelet effects, cardiac effects, wound healing and longer-term function.
The translation challenge is consequently two-dimensional. Researchers must determine whether removing senescent cells improves human cardiac performance, and they must determine whether the drug can do so without impairing the coordinated response to injury. The mouse studies provide reasons to investigate both questions, not a ready-made treatment schedule.
What this could change
For older people, the most valuable future capability would be a treatment that preserves the heart’s ability to relax and fill while limiting the chronic remodeling that makes that job harder. The same approach could potentially support recovery after a heart attack if it reduced harmful signaling without weakening the early inflammatory and scar-forming response.
That possibility depends on several conditions holding at once: the mouse improvements would need to translate into durable human functional benefit; treatment would need to be timed around repair rather than simply applied whenever senescent cells are detected; and the chosen drug or delivery strategy would need acceptable platelet and cardiac safety. If those conditions can be met, senolytics could become a way to improve how an aging heart functions without asking it to replace large amounts of lost muscle. In July 2021, that remained a plausible cardiovascular capability under investigation, not an established therapy for patients.
Key Sources
- Primary source: Senescence and senolytics in cardiovascular disease: Promise and potential pitfalls.
DOI or Journal Page · Review or Meta-Analysis · 2021-07-06
Keep exploring