
Research Signal – Source date 2025-03-27
The immune system is supposed to help keep tissues orderly. Immune cells can recognize and remove cells that have become dangerous or no longer function normally. Yet aging changes that cleanup system. As immune defenses weaken, some cells that have stopped dividing may remain in tissues, release inflammatory signals and contribute to damage elsewhere in the body.
A review published on March 27, 2025, in Cells examines this tension through the biology of cellular senescence and immunosenescence. Cellular senescence is a state in which a cell permanently stops dividing. Immunosenescence is the age-related decline in immune-cell number, function and responsiveness. The review brings together findings from cell experiments, human tissue, genetically altered and naturally aged mice, disease models and macaques. These settings point to a possible treatment strategy, but they do not all measure the same outcome.
The cleanup system changes with age
Senescence is not simply a defect. A cell entering senescence can help prevent a precancerous cell from continuing to multiply, and senescent responses can participate in tissue repair. The problem arises when senescent cells persist instead of being cleared. They can release a collection of inflammatory and tissue-remodeling substances known as the senescence-associated secretory phenotype, or SASP. Persistent SASP activity can help maintain chronic inflammation.
Aging also changes the immune system’s composition and performance. The review describes fewer or less effective immune cells, weaker immune memory and a shift in which T and B cells dominate, with memory cells replacing some of the more flexible naive cells. Factors including genetics, exercise, nutrition, the gut microbiota and infections may influence this process.
Under healthier conditions, immune cells can detect and remove senescent cells. When immune cells themselves become senescent or otherwise lose effectiveness, they may be less able to perform that task. The result is a self-reinforcing relationship: persistent senescent cells promote inflammatory conditions, while an aging immune system becomes less capable of restoring tissue balance. The important question is whether immune dysfunction merely accompanies aging or can help drive changes in other organs.
When immune aging reaches beyond immune tissues
One mouse experiment discussed in the review was designed to test that question. Researchers selectively deleted the Ercc1 gene in blood-forming cells. Because Ercc1 encodes a DNA-repair protein, this manipulation increased endogenous DNA damage within the immune system while focusing the initial defect on hematopoietic cells.
The altered mice developed signs of premature immune aging, but the effects were not confined to immune tissues. They also showed increased aging and damage in non-lymphoid organs. Cell-transfer experiments added another layer to the result: spleen cells from the altered mice, or from aged normal mice, accelerated aging-related changes when transferred into young mice. Young immune cells had the opposite effect in the reported experiments, mitigating those changes in recipient animals.
This does not show that immune aging alone explains human aging. It does show the experimental logic behind a causal contribution. By changing the immune compartment and then observing consequences in other organs, the researchers tested whether aging immune cells could act as active participants in systemic decline rather than as passive markers of it.
Recognition decides whether clearance can happen
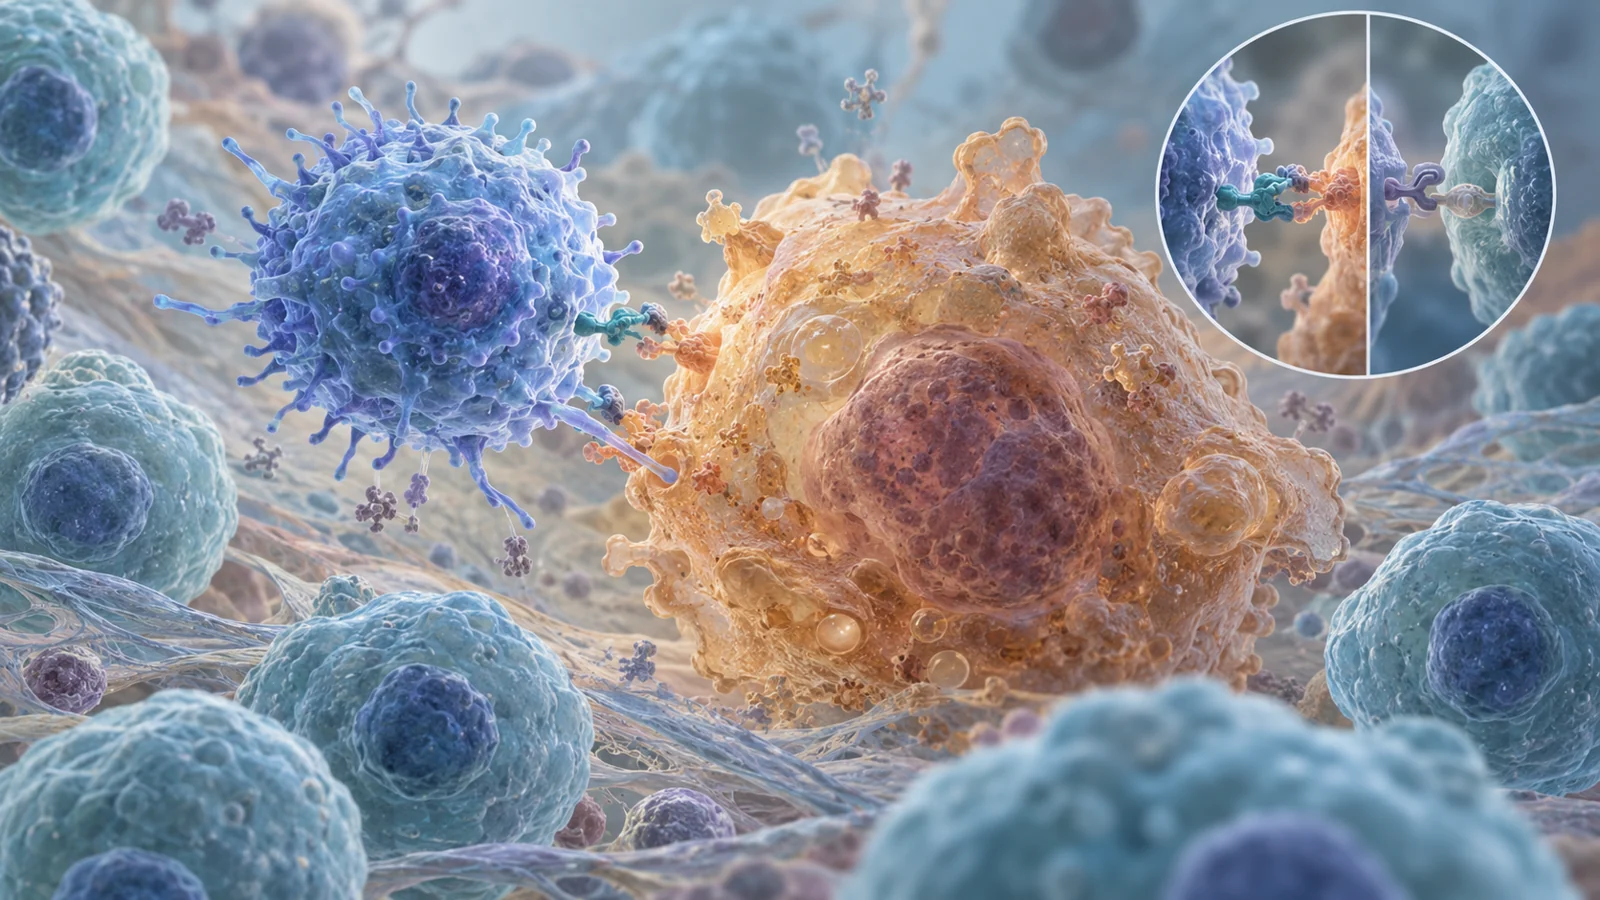
Even an active immune system cannot remove a cell it cannot recognize. The review describes a human-skin example in which recognition appears to depend on a particular combination of signals. In skin samples from people of different ages, keratinocytes expressed the chemokine CXCL9, which helped recruit CD4-positive cytotoxic T cells. Senescent fibroblasts displayed HLA class II together with a cytomegalovirus glycoprotein B antigen. The T cells could then recognize and target those cells through the presented antigen.
This finding comes from human tissue and cell-level investigation. It does not establish that every senescent cell carries the same recognizable marker. Senescent cells are heterogeneous, and the review cautions that a universal senescent-cell antigen is unlikely to exist. A useful immune target in one setting may therefore be absent or inaccessible in another.
The review also discusses a separate checkpoint-related example in cell and mouse experiments. Some senescent cells expressed the immune checkpoint ligand PD-L1, which can help them resist T-cell surveillance. These PD-L1-positive cells accumulated with age. In naturally aged mice and in mice with nonalcoholic steatohepatitis, antibodies against PD-1 reduced the population of PD-L1-positive cells and improved several age-related phenotypes in a way that depended on activated CD8-positive T cells.
The two examples illustrate different parts of the same problem. The human-skin work concerns how senescent cells can become visible to a particular T-cell response. The checkpoint work concerns a separate mechanism of resistance to T-cell surveillance, with clearance in the mouse experiments depending on activated CD8-positive T cells. Neither supplies a universal recognition system for all senescent cells.
Clearance can be chemical or engineered
One route to senescent-cell removal uses small-molecule senolytics. These compounds aim to interfere with the survival pathways that protect senescent cells from programmed cell death. The review lists natural and synthetic candidates, including dasatinib, quercetin, fisetin, piperlongumine and navitoclax. Their appeal is that they may be administered as drugs, but their targets and selectivity can vary.
The review presents engineered T cells as a more targeted strategy. In one set of mouse experiments, uPAR-positive senescent cells accumulated during aging. Chimeric antigen receptor, or CAR, T cells designed to recognize uPAR eliminated those cells. Treatment improved mobility in aged mice and improved metabolic dysfunction in aged mice and mice fed a high-fat diet. Because T cells can persist and retain memory, the reported strategy was tested as a single administration with longer-lasting effects in those animal settings.
Another approach used NKG2D-CAR T cells. NKG2D ligands were reported to increase on several types of stress-induced senescent cells, including cells produced by DNA damage, replicative exhaustion, oncogene activation or tumor-suppressor disruption. Engineered cells directed at those ligands killed senescent cells in laboratory experiments. Mouse and macaque versions were then used in aging animals, where the review reports reduced senescent-cell numbers without severe side effects in the described experiments.
These studies do not form a single head-to-head comparison. The uPAR work offers functional outcomes in mice, including mobility and metabolic measures. The NKG2D work extends target-directed clearance into another animal setting and emphasizes reduction of senescent cells. Small-molecule senolytics use a different route altogether, interfering with survival pathways rather than programming an immune cell to recognize a surface target.
What the human result actually shows
The review also recounts a clinical observation involving dasatinib plus quercetin in patients with diabetic nephropathy. The reported finding was a reduction in senescent-cell burden in adipose and skin tissue. That is important because it places senolytic treatment beyond cell culture and animal models. It is still a tissue-level result, however.
A lower measured burden of senescent cells is not the same endpoint as improved mobility, improved metabolic function, restored immune performance or longer life. The mouse CAR T-cell studies reported functional changes in specific animal models; the diabetic-nephropathy observation concerned senescent-cell burden in selected human tissues. Those outcomes should remain separate when judging how far the field has progressed.
Selectivity is the central difficulty. Senescent cells can contribute to disease when they persist, but senescence also has protective roles. A therapy that removes cells based on a marker or survival pathway may affect healthy cells that share part of that biology, or it may remove senescent cells before their useful role is complete. The review notes that many natural senolytics have incompletely defined targets and that small molecules can produce off-target effects, including damage to healthy cells and unwanted immune responses.
Engineered immune therapies face a different problem. Their effectiveness depends on finding a target that is sufficiently present on harmful senescent cells and sufficiently absent from cells that should remain. The diversity of senescent cells makes a single universal target unlikely. Animal tolerability also cannot establish long-term safety in people, and the current findings do not show that engineered T cells are clinically superior to small-molecule senolytics.
What this could change
A successful version of this approach could eventually help older adults preserve mobility and metabolic health by removing selected senescent cells that contribute to tissue dysfunction. The mouse findings make that possibility concrete: clearance was linked not only to fewer senescent cells but, in one model, to better movement and metabolic outcomes.
For that benefit to reach people, those functional effects would need to persist in human disease while treatment preserves the useful roles of senescence and avoids damaging healthy tissues. The human tissue finding with dasatinib plus quercetin shows that senescent-cell burden can be reduced in a clinical setting, but it does not yet supply the same evidence as improved mobility or metabolic health. The field’s next promise therefore lies in selective, durable immune surveillance—not in treating every senescent cell as an enemy.
Key Sources
- Primary source: Recent Advances in Aging and Immunosenescence: Mechanisms and Therapeutic Strategies.
DOI or Journal Page · Review or Meta-Analysis · 2025-03-27
Keep exploring