
Research Signal – Source date 2021-08-01
Diabetes research often treats weight, blood glucose, and insulin sensitivity as closely connected problems. A different possibility asks whether improving the behavior of fat tissue could help even when body weight itself does not change: remove some cells that have become permanently stalled after stress, and reduce the inflammatory signals they release.
That is the premise explored in the August 2021 review “Senolytics: Potential for Alleviating Diabetes and Its Complications.” The review brings together mechanistic reasoning, experiments in cells and animals, early human findings, and proposals for clinical trials. The evidence summarized here points to a plausible therapeutic direction, but it does not establish that senolytic treatment improves diabetes outcomes in people.
How metabolic stress can make a cellular problem spread
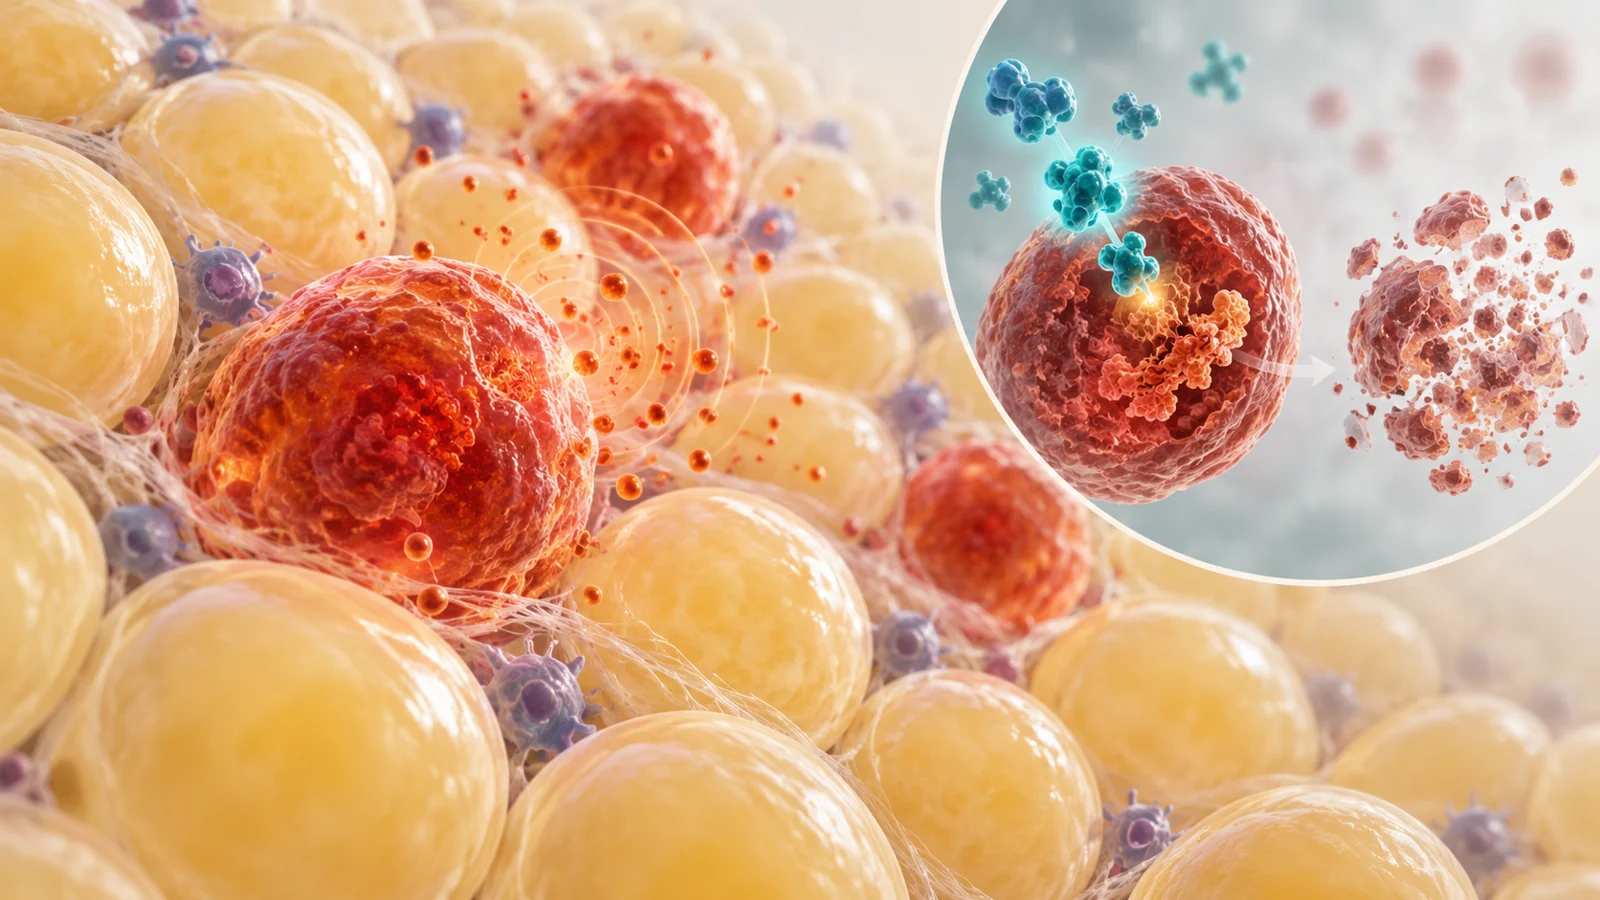
Cellular senescence is a state in which a cell stops dividing after stresses such as high glucose, saturated lipids, reactive oxygen species, DNA damage, or telomere shortening. The cell remains active rather than simply disappearing. Some senescent cells become enlarged and release a mixture of inflammatory factors, cytokines, chemokines, tissue-remodeling enzymes, lipids, and other signals known as the senescence-associated secretory phenotype, or SASP.
A small population can therefore have effects beyond the cells themselves. In adipose tissue, metabolic stress may help create senescent cells, while the signals from those cells can alter nearby tissue and contribute to further dysfunction. The diabetic state may also generate additional senescent cells through continued exposure to high glucose and lipids. The review describes this as a reinforcing loop: more stress can produce more senescence, and senescent-cell signaling can make the surrounding environment less healthy.
Senolytics are designed to act on cells after they have entered this state. They exploit survival systems that help senescent cells resist programmed cell death, rather than trying to prevent all senescence from occurring. That distinction matters because senescence can also be protective. By limiting the division of damaged or potentially cancerous cells, it can serve as a brake on dangerous growth, and senescent cells can contribute to early wound healing. Clearing every senescent cell would therefore be a biologically crude goal; the therapeutic aim is to remove harmful cells while preserving useful roles.
What changed in obese mice
The most tangible metabolic findings in the review come from diet-induced obese mice. When senescent cells were cleared, adipose tissue contained smaller fat cells, and fat distribution shifted toward subcutaneous depots rather than visceral ones. Lipid accumulation in muscle and liver also decreased. These changes were associated with improved insulin sensitivity, even though the animals did not lose body weight.
That combination is important because it separates two ideas that are often treated as interchangeable. A metabolic intervention can change where fat is stored and how fat tissue functions without producing a smaller number on the scale. In these experiments, the proposed value of senescent-cell clearance was not simply weight reduction. It was a change in the tissue environment linked to how the body handled insulin and excess lipid.
The reported effects extended beyond metabolism. In obese mice, senescent-cell clearance was also associated with improvements in outcomes including microalbuminuria, diastolic cardiac dysfunction, and fatty liver. Other experimental studies discussed by the review found changes in conditions such as vascular dysfunction, atherosclerosis, and osteoarthritis. These findings broaden the question from “Can this lower glucose?” to “Can changing a damaged tissue environment reduce several consequences of metabolic disease?” They remain findings from experimental animals, and the fact that weight did not fall in the mouse experiments does not establish that people would experience the same pattern.
Early human evidence shows tissue changes
The review also discusses an open-label phase 2 study involving people with diabetic kidney disease. In that study, senolytic therapy was associated with a lower senescent-cell burden in adipose tissue, along with reductions in macrophages, crown-like structures, and circulating SASP-related factors. These measurements matter because they show that the biological target can be reached in human tissue and that related inflammatory features can change.
They are not the same as demonstrating better kidney function, improved diabetes control, fewer complications, or an easier daily life. The study’s tissue and blood findings provide an early human indication that senolytic treatment can alter the environment in which metabolic disease develops, but they do not by themselves establish a clinical benefit for people with diabetes. Nor does the review’s account of this study turn the review into a newly reported human trial.
This is the central translation point. Animal experiments suggest that changing senescent-cell burden can be followed by meaningful metabolic and organ-level effects. The early human result shows changes in tissue biology and circulating secretory factors. A controlled trial still has to determine whether those biological changes translate into outcomes that matter to patients, and how the benefits compare with established diabetes care.
Why treatment might come in bursts
The proposed treatment pattern is unusual compared with a medicine taken continuously. Senolytics are intended to remove already formed senescent cells by weakening the pathways that keep them alive. Because a brief exposure may be enough to trigger their removal, the review describes a possible “hit and run” approach in which treatment is given intermittently rather than every day.
That schedule could reduce the time during which a drug acts on other tissues and might make treatment easier to follow. It could also limit some effects associated with continuous drug exposure. But intermittent treatment is not automatically simple. Senescent cells can reaccumulate, and diabetes involves ongoing metabolic stresses that may continue to create them. The best interval could differ between diseases, tissues, drugs, and patients.
Dasatinib and quercetin illustrate the tradeoff. They were among the first senolytic combinations identified by looking for drugs that interfere with senescent-cell survival pathways. Dasatinib has known toxicities, including pleural effusions and pulmonary hypertension, while quercetin can cause kidney toxicity at higher doses or when combined with other nephrotoxic agents. Intermittent dosing may help manage exposure, but it does not remove the need to study drug-specific risks. There are also theoretical concerns about removing senescent cells when their functions are useful, including during wound healing or tissue regeneration.
The therapeutic question is therefore more precise than whether senolytics “work.” Researchers need to determine which senescent-cell populations should be targeted, which drug or combination reaches them, how often treatment should be repeated, and what level of clearance is safe in a particular tissue.
Why complications come before prevention
The review proposes beginning with selected diabetes complications rather than immediately testing whether senolytics can prevent diabetes from developing. Prevention studies would require long observation and would expose people who may not yet have a serious complication to a treatment whose long-term safety is still uncertain.
A complications-first strategy could focus on problems such as diabetic wounds or kidney disease, where tissue dysfunction is clinically important and where a trial might assess a meaningful outcome within a more manageable timeframe. This does not mean existing care has no value. It means that an additional treatment aimed at senescence-related dysfunction may be easiest to evaluate where current options leave important needs unresolved.
If controlled trials showed meaningful benefit and an acceptable safety profile in such complications, later studies could examine prevention. Those studies might ask whether senolytic treatment delays insulin resistance in obesity or reduces the development of diabetic kidney disease. The sequence matters: prevention is a more distant possibility that depends on first showing that targeted clearance helps people and does not create unacceptable harm.
What this could change
For people with diabetes, the long-term opportunity is a treatment class aimed at removing harmful senescent cells and reducing the effects of their signals on surrounding tissues. If controlled trials show that selective senolytic treatment improves complications such as diabetic wounds or kidney disease with acceptable safety, patients could eventually have options directed at tissue dysfunction alongside glucose management. Preventive use could follow only after its own evidence is established. The practical promise is not a shortcut around diabetes care, but the possibility of addressing some of the cellular conditions that make its complications harder to manage.
Key Sources
- Primary source: Senolytics: Potential for Alleviating Diabetes and Its Complications.
DOI or Journal Page · Review or Meta-Analysis · 2021-08-01
Keep exploring