
Research Signal – Source date 2021-09-06
Bone aging raises a deceptively simple question: if some cells help drive deterioration, could removing them protect the skeleton?
A review published on September 6, 2021, examines that possibility through research on senescent cells, a population of cells that accumulates in several tissues with age and releases signals that can affect its surroundings. The drugs designed to clear them are called senolytics. In mouse experiments discussed by the review, removing selected senescent cells improved measures of bone loss and bone structure. But those findings describe a biological possibility, not an established treatment for osteoporosis.
Osteoporosis already had approved treatments, including bisphosphonates, denosumab, parathyroid hormone-related medicines and others. The senolytic idea asks a different question from simply slowing bone loss with an existing drug: could changing the cellular environment that contributes to deterioration help preserve the skeleton? Answering that question requires separating aging-related mechanisms from other causes of bone loss, and separating a promising target from a safe medicine.
Aging changes the neighborhood inside bone
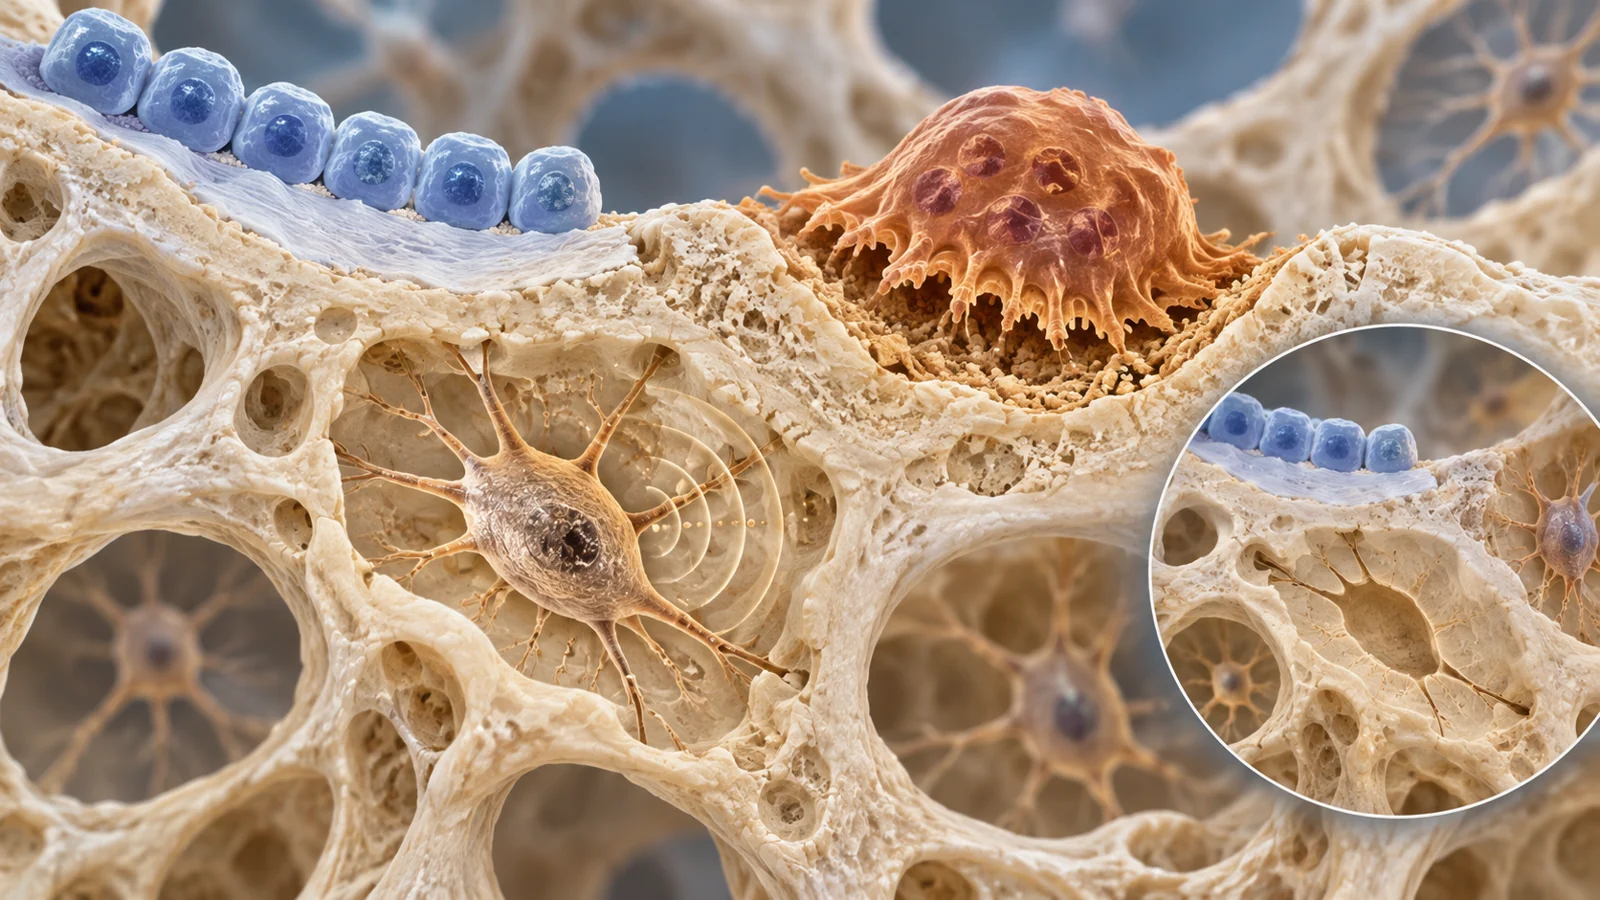
Bone is maintained by several cell populations with different jobs. Osteoblasts build new bone. Osteoclasts remove it. Osteocytes are embedded within the bone and help coordinate activity in the surrounding tissue. Healthy skeletal strength depends on the balance among these roles, not on one cell type acting alone.
The review describes evidence that aging changes this local environment. In mice, the senescence marker p16Ink4a increased with age in osteoblastic-lineage cells and bone-marrow hematopoietic populations. Other markers, including p21Cip1 and p53, increased more prominently in osteocytes or myeloid cells. Older mice also showed signs of DNA-damage-related cellular stress in osteocytes, along with increased expression of genes associated with the senescence-associated secretory phenotype, commonly abbreviated as SASP.
SASP is a collection of signals released by senescent cells. These signals can influence nearby cells, so a senescent cell is not merely a passive remnant inside aging bone. A cell with senescent characteristics may alter the conditions in which bone-forming, bone-removing and immune cells operate. In the review’s animal evidence, increased RANKL expression in osteocyte-enriched bone fractions and higher circulating RANKL were associated with aging, raising a possible connection between osteocyte senescence and increased bone resorption.
Human tissue findings provide an important but narrower piece of the picture. Bone biopsies from older women showed increased senescence markers and SASP-related gene expression in the bone microenvironment. Those observations show that senescence-associated features can be detected in human aging bone. They do not show that clearing the marked cells would improve those women’s bone mass, prevent fractures or make an osteoporosis treatment effective.
The experiment that moved beyond correlation
Finding age-associated markers is not the same as showing that the marked cells contribute to bone loss. The more consequential experiments described in the review attempted to remove a selected population and then observe what changed.
One approach used INK-ATTAC mice, an engineered system in which administration of a synthetic compound activates a caspase mechanism that triggers cell death in p16-positive cells. In plain language, the model gave researchers a way to remove a subset of cells carrying a senescence-associated marker. It was not a method for eliminating every senescent cell in the body, and it was not a directly transferable human treatment.
In old mice receiving this intervention, detailed skeletal measurements showed less trabecular and cortical bone loss. The bone surface also contained fewer osteoclasts, the cells that remove bone, and more osteoblasts on endocortical surfaces, where new bone can be formed. The pattern is biologically informative because it links cell removal with changes in both sides of the remodeling process.
The result adds something that a biopsy marker cannot provide. It supports a causal contribution by the targeted p16-positive cells in that particular mouse model. It still leaves open which senescent populations matter most, whether the same balance exists in people, and whether removing cells with similar markers would produce the same effects across different diseases or treatments.
Bone loss does not have one biological cause
The word osteoporosis can make different routes to skeletal weakness sound like one process. The review’s evidence argues for more careful separation.
Sex-steroid deficiency, such as the loss of estrogen after menopause, is a major cause of bone loss. Yet the experiments summarized in the review did not find that ovariectomy or orchidectomy increased senescence or SASP signaling in mice. Estrogen treatment in elderly postmenopausal women also did not change the senescence markers measured in bone biopsies. These findings do not rule out every relationship between hormones and senescence, but they caution against assuming that all hormone-related bone loss is driven by the same senescent-cell pathway.
Chemotherapy-induced bone loss presents a different route. In mice treated with doxorubicin, senescence markers increased in sorted bone-resident cells and, to a lesser extent, in several other cell populations. Removing p16-positive senescent cells in that setting alleviated trabecular bone loss, reduced osteoclasts and preserved osteoblasts. Inhibiting the p38MAPK-MK2 pathway to suppress SASP activity also partially alleviated the bone loss.
The contrast matters. A treatment aimed at senescent cells might be especially relevant when DNA damage and treatment-related cellular stress create a high senescent-cell burden. That possibility cannot be extended automatically to every form of osteoporosis simply because the final problem is reduced bone mass. Similar-looking skeletal outcomes can arise from different biological routes.
A target is not yet a safe medicine
The word senolytic describes an intended action, not a guarantee that a drug will remove only harmful cells. Candidate compounds can affect healthy cells, and the timing of exposure can change the result.
The review discusses dasatinib plus quercetin as an early pharmacological senolytic combination used intermittently in old mice. It contrasts this kind of hit-and-run exposure with senomorphic treatment, which aims to suppress the secretions of senescent cells rather than kill the cells themselves. A senomorphic approach may require continuing exposure, while intermittent senolytic dosing could limit some off-target effects. That is a research strategy, not proof that intermittent treatment is safe.
Navitoclax, also called ABT-263, makes the tradeoff concrete. It can clear senescent cells in some experimental settings, but it also affects non-senescent cells and has been associated with platelet toxicity and transient thrombocytopenia. In the cited mouse study, daily treatment of old animals caused trabecular bone loss and impaired the function of osteoprogenitors. A compound intended to protect bone therefore produced an adverse skeletal effect under one exposure schedule.
The lesson is not simply that one drug failed. It is that the biological target and the usable medicine are separate problems. Selectivity, dose, schedule, tissue distribution and the role of the targeted cells all matter. Clearing a marker-positive population in an engineered mouse is not equivalent to administering a senolytic to an older person with several causes of bone fragility.
Senescent cells may also help repair tissue
Senescence is not always a permanently harmful state. The review describes circumstances in which temporary senescent cells contribute to useful biology, including protection against malignant transformation, embryonic tissue patterning and wound healing. In skin wounds, senescent endothelial cells and fibroblasts can release signals that help coordinate repair, after which they may be cleared.
That evidence creates a specific question for bone healing. Fracture repair involves inflammation, new blood-vessel formation and the differentiation of bone stem cells. Aging can impair these processes, but the role of senescent cells during fracture healing remains unresolved. Removing them might improve the environment in some situations, or it might interfere with a temporary function needed for repair.
A rat skull-defect experiment offers an intriguing but separate example. In a model involving local inflammation and stress-induced premature senescence, treatment with dasatinib plus quercetin reduced senescence-associated staining and increased bone formation in the defect. A locally delivered green-tea-derived compound also reduced senescence markers and produced an even higher bone-formation level in that experiment.
A skull defect in a rat is not the same as a fragility fracture in an older person. The model shows that senescence-targeting approaches can be investigated in regeneration, but it does not settle whether clearing cells would improve bone union, slow it or disrupt useful repair signals after a human fracture.
What targeting aging cells could mean for fracture prevention
The long-term appeal of this research is practical. A treatment that selectively changed the aging bone environment could, in principle, help older adults retain skeletal strength and remain mobile and independent for longer. Lower fracture risk would be the meaningful clinical benefit, because fractures can alter walking, posture, daily activity and the ability to live independently.
That benefit remains conditional on several biological pieces fitting together: the treatment would need to act on the relevant senescent cells, avoid damaging bone-forming precursors and other healthy tissues, work for the particular cause of bone loss, and preserve the temporary cellular responses that help repair injury. The experiments reviewed in 2021 make the possibility more concrete by showing that cell clearance can change bone biology in mice. They do not yet show reduced fractures or improved osteoporosis outcomes in humans.
If selective and well-tolerated senolytic treatment eventually meets those conditions, it could add a new way to protect aging skeletons alongside existing approaches. Its significance would not be that aging cells had been erased wholesale, but that a carefully controlled change in the bone microenvironment might help people keep the strength, mobility and independence that fragile bones threaten.
Key Sources
- Primary source: The role of senolytics in osteoporosis and other skeletal pathologies.
DOI or Journal Page · Review or Meta-Analysis · 2021-09-06
Keep exploring