
Research Signal – Source date 2025-07-17
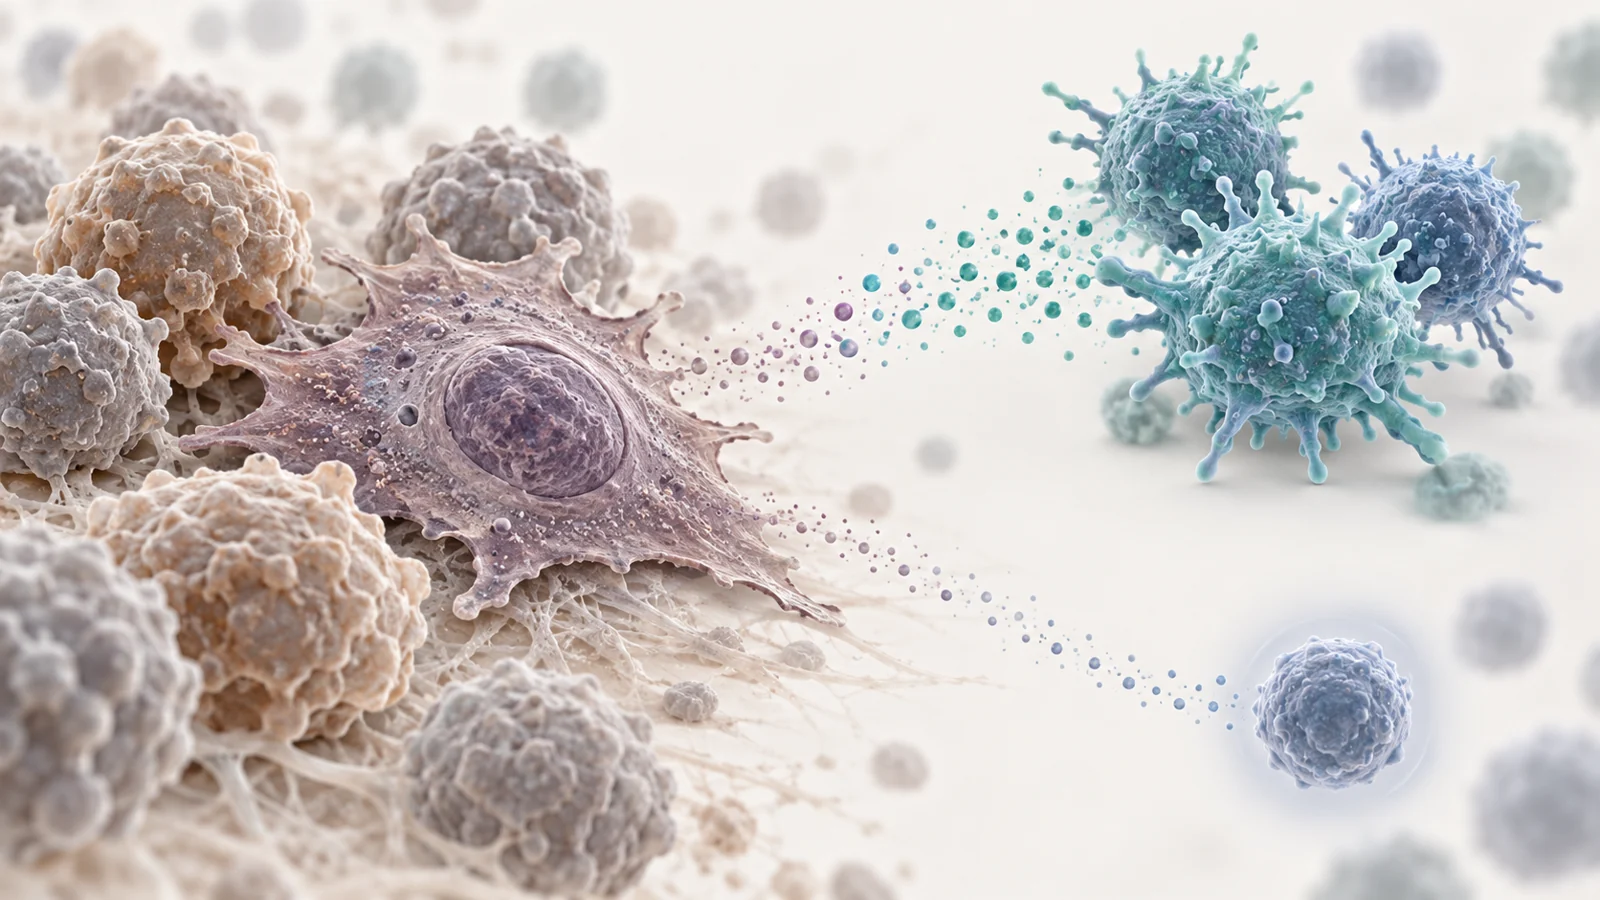
Cells that have stopped dividing can still influence what happens around them. Some release a changing mix of inflammatory molecules that calls immune cells into nearby tissue. In a tumor, that response may help the body recognize abnormal cells. If the secretions persist, however, they can also reshape the neighborhood in ways that help cancer evade immune attack.
A review published on July 17, 2025, examines this double role of the senescence-associated secretory phenotype, or SASP. It brings together mechanistic research and examples of proposed treatments; it is not a new treatment trial. Its central challenge is that the same broad process can contribute to immune surveillance in one context and immune suppression in another.
A changing neighborhood around senescent cells
Senescent cells have stopped dividing, often after stress or damage, but they remain active. Their SASP is not one substance. It is a mixture that can include interleukins and other cytokines, chemokines, growth factors, and enzymes that alter surrounding tissue. The mix varies with the cell, the tissue, and what caused senescence.
Some of these molecules act on nearby cells, passing the senescence state along. Others affect immune cells directly or change the signals those immune cells encounter. For example, the review describes CXCL1 as one factor that can prompt neighboring cells to become senescent. Meanwhile, factors such as CCL2 can draw myeloid-derived suppressor cells and regulatory T cells into the tumor environment. These populations can weaken the activity of cells that would otherwise attack a tumor.
The result is not a simple switch from “good” inflammation to “bad” inflammation. A local immune response depends on which cells are present and which SASP components they encounter. Early on, inflammatory signals such as IL-1α, IL-6, and IL-8 can recruit M1 macrophages, Th1 cells, and natural killer (NK) cells. These cells may help clear senescent cells and tumor cells. With persistent inflammation, the balance can shift: immune-suppressing cells accumulate, while the effectiveness of T cells and NK cells may fall.
Time and tissue change the balance
The effect of SASP depends partly on when it is measured. The review describes senescence as a process in which secretions change over time. Early and later phases can have different dominant factors; Notch signaling, for example, is discussed as part of the shift between early and later SASP components. A snapshot of one molecule may therefore miss how the local environment is evolving.
The cause of senescence matters too. Cancer treatments that damage DNA can produce a different SASP profile from CDK4/6 inhibitors, according to the review. Tissue conditions—including oxygen, metabolism, and nutrient availability—also shape which factors appear. A tumor in a tissue with many NK cells faces a different immune environment from one in a tissue with fewer of them.
These differences help explain why the same intervention might have different consequences across cancers. Suppressing an inflammatory pathway could reduce a tumor-supporting SASP in one setting, yet interfere with immune surveillance in another. In particular, the review notes that cGAS–STING signaling can contribute to SASP and chronic inflammation, but it can also support anti-tumor surveillance. Its role depends on the biological setting; turning it down cannot be assumed to have one uniform effect.
How chronic signals can blunt T-cell attack
One route to immune escape involves PD-L1, a molecule that can restrain T-cell activity. The review describes several pathways through which inflammatory conditions in the aging tumor microenvironment can raise PD-L1 expression. For instance, IL-6 can activate a STAT3-linked signaling axis associated with increased CD274, the gene that encodes PD-L1. TNF-α can promote its transcription through NF-κB. Other pathways described in the review connect DNA damage and interferon signaling to PD-L1 regulation.
At the same time, SASP factors can alter which immune cells reach the tumor. CCL2 can recruit suppressive myeloid cells and regulatory T cells, while IL-6 and IL-8 are associated in the review with changes that can impair NK-cell and mature CD8+ T-cell activity. Together, these routes offer a reason to consider checkpoint inhibitors, which aim to release restraints on immune attack, alongside strategies directed at senescent cells or their secretions.
That rationale does not mean every tumor with inflammatory signals will respond to a checkpoint drug, or that lowering SASP will reliably improve the response. The relevant signals, immune cells, and timing vary across tumors.
Quieting secretions or removing their source
The treatment approaches discussed in the review take two distinct directions. Senomorphics aim to change what senescent cells secrete while leaving the cells in place. Senolytics aim to eliminate senescent cells, thereby removing a source of SASP. Each approach has a different trade-off.
Quieting secretion may avoid the consequences of removing cells that still have useful roles in tissue. But a drug aimed at one factor, such as IL-6, may leave other parts of the SASP active. The review also cautions that broad suppression of pathways such as NF-κB could impair immune functions; suppressing cGAS–STING may, in some settings, weaken anti-tumor surveillance. Dose and context matter as well.
Removing senescent cells may more directly reduce their secretions, but those cells are not automatically harmful in every tissue. The review discusses concerns that clearing them in older tissues could disrupt tissue structure or function. A strategy that eliminates a cellular population therefore needs selectivity and a clear understanding of what that population is doing in the particular tumor environment.
The review also describes combining senescence-directed approaches with PD-1 or PD-L1 checkpoint treatment. The intended logic is to reduce a source of immune suppression while also easing a brake on immune cells. Whether that pairing helps depends on which part of the process is limiting immune attack in a given tumor.
A mouse result and a separate clinical picture
One cited mouse experiment illustrates the combination rationale. In a lung cancer model, researchers first used a 223Ra/Ba-based treatment described as inducing senescence, then administered anti-PD-L1. The review reports longer survival and suppression of distant tumors in that model. This is evidence from mice, not a result in people, and the treatment sequence is a specific experimental example rather than proof that senescence-directed combinations work broadly.
The review discusses clinical IL-6-targeting findings separately. It notes that targeting IL-6 or its receptor alone, or alongside chemotherapy, had not significantly improved outcomes in cited solid-tumor trials. It also describes a report in recurrent epithelial ovarian cancer in which tocilizumab, an IL-6 receptor antibody, combined with carboplatin and doxorubicin was associated with increased M1 macrophage polarization and T-cell effector activity. These examples concern different settings and outcomes; they do not establish a general clinical benefit from suppressing SASP.
Why a SASP test is not yet a treatment selector
SASP components can help describe senescent cells, but the review says that the mixture alone is not enough to identify them definitively. Many of the same proteins occur in other cell types, and the composition changes with tissue and the cause of senescence. A measurement of one factor may not tell clinicians which cells produced it, what other signals are present, or whether immune surveillance is being helped or hindered.
This makes patient selection a central challenge. A useful match would have to account for the tumor type, its surrounding tissue, the immune cells present, the cause and stage of senescence, and the treatment being considered. The review points to more precise, tissue-specific markers and better understanding of timing as research needs, but it does not supply a validated rule for identifying patients who would benefit across cancers.
What this could change for cancer immunotherapy
If researchers can identify which senescent-cell signals are driving immune escape in a particular tumor, treatment could eventually be matched to that local problem: quieting harmful secretions, clearing their source, or pairing one of those approaches with checkpoint therapy. That could make immune treatment more effective for some patients while avoiding disruption of useful surveillance in others. Reaching that capability will require reliable ways to distinguish senescent cells and clinical studies that show which combinations help which patients.
Key Sources
- Primary source: Immunoregulatory mechanisms in the aging microenvironment: Targeting the senescence-associated secretory phenotype for cancer immunotherapy.
DOI or Journal Page · Review or Meta-Analysis · 2025-07-17
Keep exploring