
Research Signal – Source date 2022-05-26
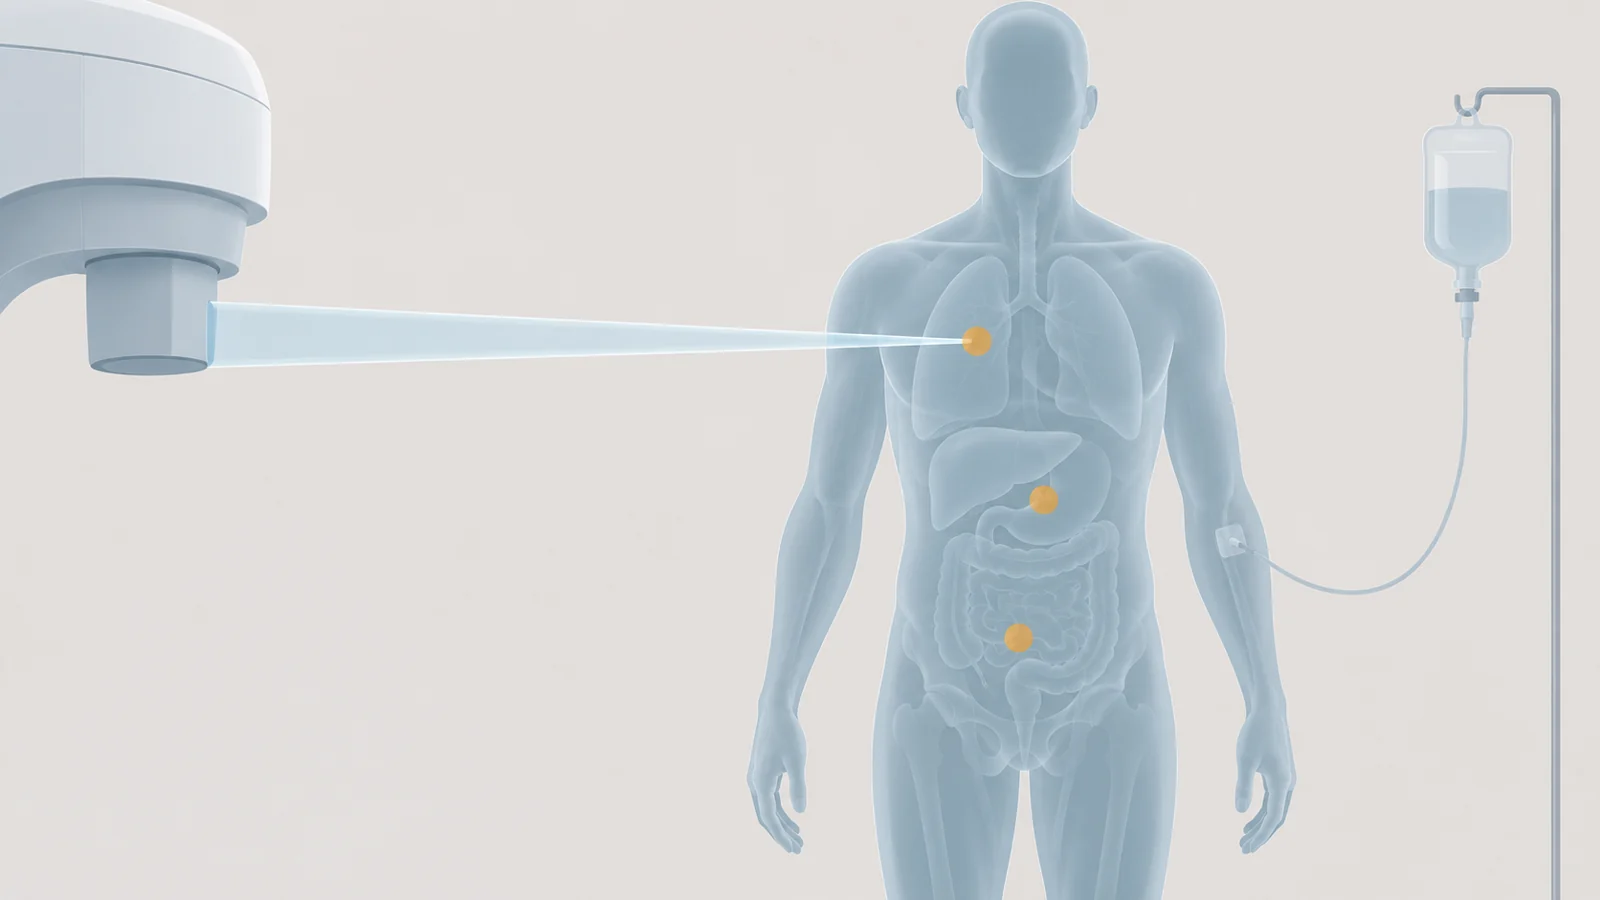
A few cancer spots can grow while a person is receiving immunotherapy, even when the treatment is still part of their care. In a retrospective study, doctors irradiated up to five growing spots in selected patients who were continuing immune checkpoint inhibitors, a type of treatment that helps the immune system recognize cancer. The study describes what happened afterward and which patient or tumor features were associated with different outcomes. It cannot show whether radiation itself improved survival or whether keeping the same drug was better than changing treatment.
A selected group with limited growth
The researchers screened 1,423 patients treated between 2010 and 2020 and identified 120 who met the study criteria. Each had radiation to five or fewer progressing lesions while receiving an immune checkpoint inhibitor. The median number of progressing lesions was one. Lung cancer and melanoma were the most common cancer types in the group.
That selection matters when reading the results. The 120 people were not a representative sample of everyone whose cancer grows during immunotherapy; they were the patients who fit this study’s criteria and received radiation for a limited number of growing sites. The screened-to-eligible count describes how the study group was assembled, not how common this pattern is among patients generally.
The study also excluded people whose systemic treatment was changed after radiation but before their cancer progressed. That design choice narrows what the analysis can tell us about the treatment decision that often follows limited progression.
Three outcomes answer different questions
Local control concerns what happened at the spots that received radiation. Progression-free survival measures how long people remain alive without their cancer worsening. Overall survival measures time until death from any cause. These measures describe different parts of a patient’s course and should not be treated as interchangeable.
In this selected group, the reported median progression-free survival was 6.41 months, and median overall survival was 29.80 months. These are observations among the patients studied, not estimates of how much radiation extended either measure. The study’s retrospective design cannot separate the effect of radiation from other differences among patients or their cancers.
The associated clues varied by outcome
For local control at irradiated lesions, the researchers found associations with the local response to radiation and with whether the irradiated lesions were newly developed. For progression-free survival, the reported predictors were the best response to radiation and a higher tumor PD-L1 score. PD-L1 is a marker measured in tumor tissue; here, its association is a clue from this analysis, not a stand-alone rule for choosing treatment.
Overall survival had a different set of associations. It was associated with the combined volume of the progressing lesions and with how long a patient had received immunotherapy before oligoprogression—growth at a limited number of sites while other treatment continues. The findings do not mean that any one of these features can reliably predict an individual patient’s outcome.
Cancer type, the site that received radiation, and the radiation modality were not associated with local control, progression-free survival, or overall survival in this analysis. That is a result within this particular selected cohort; it does not establish that those factors never matter in other patients or settings.
The treatment comparison remains unresolved
The practical question is whether treating a few growing spots with radiation while continuing immunotherapy can be preferable to switching systemic treatment. This study does not answer it. Because the analysis was retrospective, patients were not randomly assigned to those competing strategies. And by excluding patients whose systemic treatment changed after radiation but before progression, the researchers did not compare the full set of treatment paths needed to establish which choice produces better outcomes.
The reported associations can help describe which features tracked with outcomes in this group, but they do not validate radiation response, PD-L1 score, or lesion volume as clinical decision rules. The supplied evidence also does not provide a quantified comparison of treatment harms, so it cannot establish a safety tradeoff between the approaches.
What this could make possible
For someone with one growing cancer spot during immunotherapy, a dependable, evidence-guided choice could make it clearer whether to irradiate that spot and continue the drug or change systemic treatment. That could help clinicians and patients choose a next step that better fits the likely course of the disease, without assuming that one strategy works for everyone.
This study offers a starting point for that future: it followed a selected group with limited progression and found different features associated with local control, progression-free survival, and overall survival. A dependable choice would require comparative evidence that tests the treatment paths directly. One meaningful milestone would be a prospective comparison of radiation with continued immunotherapy versus a change in systemic treatment, measuring progression, survival, and harms.
Key Sources
- Primary source: Retrospective Review of Outcomes After Radiation Therapy for Oligoprogressive Disease on Immune Checkpoint Blockade.
DOI or Journal Page · Review or Meta-Analysis · 2022-05-26
Keep exploring