
Research Signal – Source date 2025-10-04
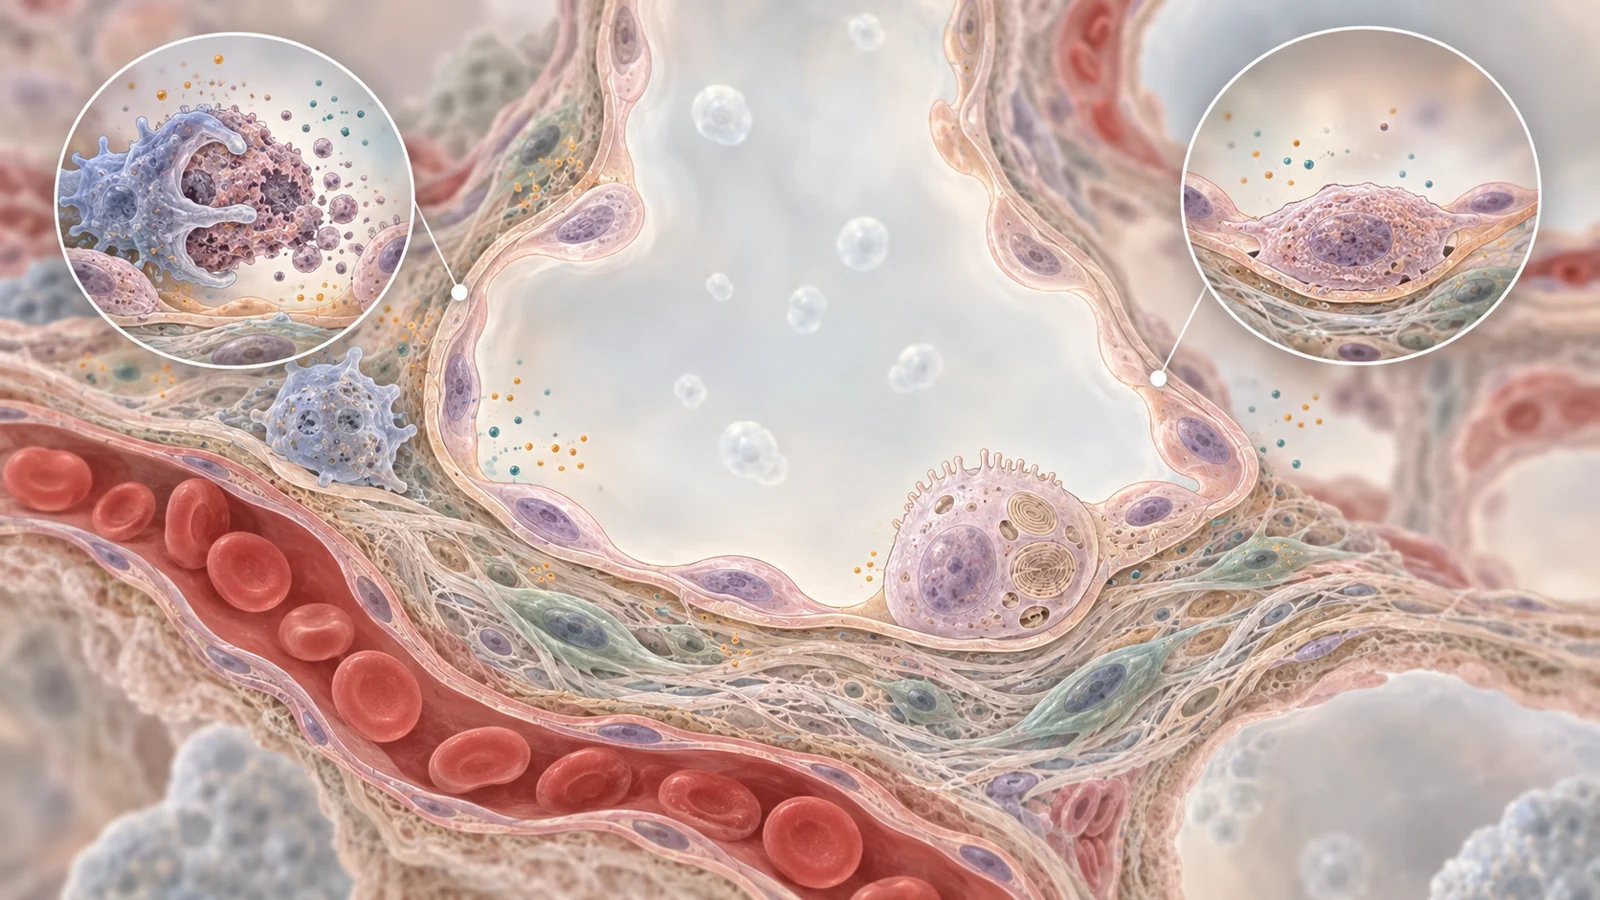
Cellular senescence is often described as a shutdown: a cell stops dividing, usually in response to stress, damage or other biological pressures. But the cell does not become inert. It can remain metabolically active, resist cell death and release a mixture of signaling molecules known as the senescence-associated secretory phenotype, or SASP.
That combination creates a therapeutic dilemma in the lung. Short-lived senescence can help limit tissue injury, support repair and suppress tumor formation. Persistent senescent cells, by contrast, can contribute to continuing inflammation, fibrotic remodeling and poor regeneration. A review published on October 4, 2025, examines why the difference matters, especially as researchers investigate drugs that either remove senescent cells or alter what they release.
The central issue is not simply whether senescent cells are present. It is which cells have entered the state, where they are located, how long they have remained there and what signals they are producing.
Senescence has different roles over time
A temporary senescent response can be part of the lung’s response to injury. A cell that stops dividing may prevent damaged genetic material from being passed on, while signals from the local tissue help coordinate repair. The same broad biological program becomes more problematic when senescent cells persist and accumulate.
Persistent cells may release inflammatory cytokines, chemokines, growth factors and matrix-remodeling enzymes. The review describes examples including IL-6 and IL-8, as well as matrix metalloproteinases. These signals can influence neighboring cells and the structure around them, so the effects of senescence may extend beyond the original cell.
The timing is important because removing every senescent cell would not necessarily be desirable. Some senescent states may be transient or associated with useful protective work. The practical goal is more selective: identify the persistent, damaging populations and intervene without disrupting senescence’s short-term roles in repair and tumor suppression.
A lung is not one senescent cell population
The review emphasizes that senescence in lung disease extends across several cell types. Fibroblasts help maintain and remodel the tissue framework. Alveolar type II epithelial cells, often called AT2 cells, help replenish the lining of the air sacs. Endothelial cells, immune cells and alveolar type I cells can also develop senescence-associated features.
Those identities change the problem. A senescent fibroblast may release signals that promote inflammation and extracellular-matrix remodeling. In idiopathic pulmonary fibrosis, the review describes senescent AT2 cells with a secretory profile associated with fibrotic signaling and impaired regenerative responses. If AT2 cells lose part of their progenitor function, the air-sac lining may receive less regenerative input, particularly in distal lung regions that turn over slowly.
The review also describes different secretory patterns in chronic obstructive pulmonary disease and post-COVID-19 lung fibrosis. Airway epithelial cells in COPD are associated with signals including IL-6, IL-8, CCL2 and MMP-12. In post-COVID-19 fibrosis, epithelial signals such as IL-1β, CCL2 and TGF-β resemble some of the patterns discussed in pulmonary fibrosis.
These examples do not turn senotyping into a routine clinical test. Senotyping means characterizing distinct senescent states and profiles rather than treating all senescent cells as interchangeable. Researchers still need to determine how those states vary across lung compartments, how they change from early to late senescence and which combinations of markers correspond to harmful activity in living patients.
Single-cell RNA sequencing, spatial transcriptomics, metabolomic profiling and computer-assisted tissue analysis are among the approaches the review identifies as useful for studying that complexity. Their role is to make cell identity, location and function more visible. The unresolved question is how to translate that information into a reliable way to select and monitor treatment.
Removing cells and quieting their signals are different strategies
Senolytics are intended to promote the death of senescent cells. Their rationale comes from a survival problem: senescent cells can remain alive despite accumulated damage and the potentially self-toxic burden of their secretions. To do so, they may depend on senescent-cell anti-apoptotic pathways, sometimes called SCAPs.
A senolytic can temporarily disable one or more of those defenses, leaving a vulnerable cell less able to resist its internal damage or surrounding pro-death signals. The specific defenses vary among senescent cell types. Pathways involving BCL-2 family proteins, PI3K and AKT, p53 and related regulators are among the survival dependencies discussed in the review. Differences in those dependencies help explain why a candidate drug may affect one senescent population more than another.
Senomorphics, also called senostatics, take a different route. They aim to reduce harmful SASP activity while leaving the senescent cell in place. Because the SASP contains hundreds of possible components, intervention can occur at several levels of production and secretion. In principle, this could dampen inflammatory or fibrotic signals without requiring cell removal.
The tradeoff is that the SASP is not uniformly harmful in every setting. Some signals may participate in immune recruitment or tissue repair. Broadly suppressing pathways such as mTOR, NF-κB or ATM could also affect functions beyond SASP regulation. Long-term treatment therefore raises questions about immunity, metabolism and cancer risk, while the appropriate degree of suppression may differ according to the cell type and cause of senescence.
The two approaches also create different measurement problems. A senolytic program needs evidence that the relevant cells have been reduced. A senomorphic program needs evidence that the harmful secretory activity has changed in the intended tissue. The review identifies a shortage of reliable, non-invasive biomarkers for senescence in human lungs, making both treatment selection and monitoring difficult.
Early patient findings need careful attribution
The review places an early human example in that wider context. It describes an open-label pilot of intermittent dasatinib plus quercetin in people with idiopathic pulmonary fibrosis, a progressive disease involving lung scarring. The study reported improvements in physical-performance measures including gait speed and chair-rise times.
Those results are relevant, but they answer a narrower question than whether a lung senolytic treatment has cleared senescent cells. The review states that direct clearance of senescent cells in the lung was not assessed in the pilot. The reported changes therefore do not, by themselves, show that senescent cells were removed from lung tissue, that fibrosis was reversed or that lung function was durably restored.
A separate study discussed in the review involved people with diabetic kidney disease. In that population, researchers measured changes in senescence-related markers in subcutaneous adipose-tissue biopsies after dasatinib plus quercetin, along with changes in circulating SASP factors. Those observations concern a different disease setting and a different tissue. They cannot be transferred directly into evidence of senescent-cell clearance inside human lungs.
Keeping these findings attached to their population, tissue and endpoint matters. A physical-performance change may be clinically interesting without identifying the biological pathway responsible. A change in markers in adipose tissue may support a treatment effect in that tissue without demonstrating what happened in a diseased lung. The review’s broader message is that plausible mechanism, measurable biomarker change and meaningful patient benefit are related but separate steps.
A promising target still has to reach the right tissue
Senescence biology can point to a target without solving the delivery problem. A drug may act on a relevant survival or secretory pathway in laboratory models, yet still be difficult to administer at a concentration that reaches diseased lung regions while remaining tolerable elsewhere in the body.
The review identifies navitoclax as one example of the safety challenge. Its off-target blood-related toxicity has constrained clinical development, a particular concern for older people and those living with multiple health conditions. This illustrates the difference between a biologically plausible target and a practical treatment. Selectivity must apply not only to the intended cell state but also to the exposure experienced by other tissues.
Localized approaches, including inhalable senotherapeutics and advanced delivery systems, are described as research directions for improving lung exposure and limiting systemic effects. Nanotechnology and other delivery strategies may eventually help concentrate treatment where it is needed. They have not, however, resolved the questions of distribution, dosing, long-term safety or whether the targeted cells can be identified reliably in individual patients.
For lung disease, a useful treatment may ultimately require several forms of precision at once. Researchers would need to distinguish harmful from temporary senescence, identify the affected cell population, reach the relevant lung compartment and show that the intervention changes an outcome patients feel or live with. The right choice might be cell removal in one context, SASP modulation in another or a combination that is tested carefully rather than assumed to be interchangeable.
What targeted treatment could mean for damaged lungs
For people living with chronic obstructive pulmonary disease or pulmonary fibrosis, the prospective benefit is preservation: treatments directed at damaging cellular processes could help protect functioning lung tissue and its capacity for repair.
That possibility depends on several conditions still under development. Researchers must identify actionable senescent cell states, deliver treatment at a tolerable exposure and demonstrate durable benefit in patients. The review’s 2025 perspective supports cautious interest in that path, not a conclusion that senolytics or senomorphics have already restored damaged lungs. The promise lies in matching intervention to the biology of the cell, the location of the damage and the outcome that matters to the person receiving treatment.
Key Sources
- Primary source: Heterogeneity of Cellular Senescence, Senotyping, and Targeting by Senolytics and Senomorphics in Lung Diseases.
DOI or Journal Page · Review or Meta-Analysis · 2025-10-04
Keep exploring