
Research Signal – Source date 2022-08-29
For people with advanced lung cancer that has spread to bone, denosumab may already be one option for bone-targeted care. Could the choice of that drug also affect how well immunotherapy controls the cancer? In a 2022 chart review, patients who received denosumab with an immune checkpoint inhibitor had a reported median progression-free survival of 378 days, compared with 190 days for patients who received another bone-targeted drug with immunotherapy. Across all four treatment groups, however, the study did not establish a statistically significant difference.
Progression-free survival is the time patients live without their cancer worsening. The gap in those two reported medians is an intriguing observation, not evidence that denosumab caused longer cancer control. The comparison included different treatment combinations and was not randomized.
Four treatment combinations in patient records
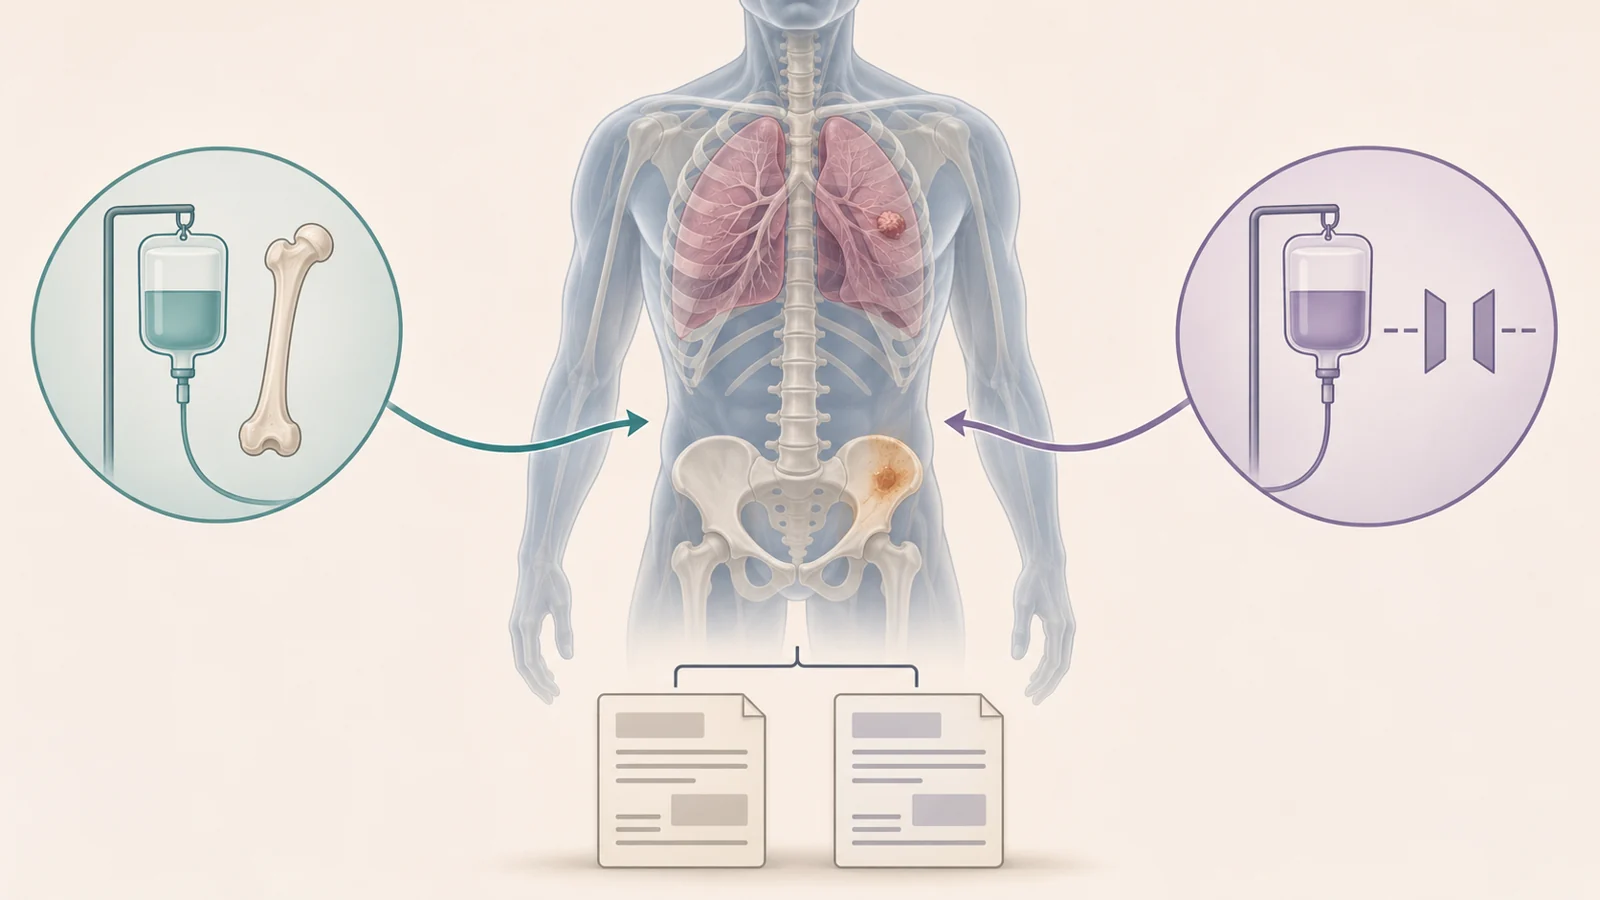
Researchers at the Chinese National Cancer Center reviewed charts for patients with non-small cell lung cancer and bone metastases treated between December 2020 and December 2021. Of 410 patients who received bone-targeted therapy, 171 met the study’s eligibility criteria. The analysis compared four groups: denosumab with immune checkpoint inhibitors (40 patients); the other bone-targeted drugs labeled “phosphates” with immune checkpoint inhibitors (74); denosumab without immune checkpoint inhibitors (15); and phosphates without them (42).
The four-way comparison was designed to help separate two questions. Comparing denosumab plus immunotherapy with phosphates plus immunotherapy asks whether outcomes differed when the bone-targeted drug changed while immunotherapy was used. The groups without immunotherapy provide comparisons for denosumab and phosphates in the absence of that treatment. Because doctors’ choices determined which treatment patients received, the design can reveal associations in this hospital’s records, but it cannot establish that one drug combination produced an outcome.
The groups were uneven in size, particularly the denosumab-without-immunotherapy group. Patients also differed in recorded characteristics: adenocarcinoma, a lung cancer subtype, was more common in the two groups without immunotherapy, while PD-L1 expression, a tumor marker relevant to immune treatment, was more common in the two groups receiving it. Those differences make a simple comparison harder to interpret.
The overall tumor-control comparison was inconclusive
The objective response rate—the share of patients whose tumors shrank enough to meet the study’s response criteria—was 47.5% with denosumab plus immunotherapy, 43.2% with phosphates plus immunotherapy, 33.3% with denosumab without immunotherapy, and 40.5% with phosphates without it. The four-group comparison was not statistically significant (p = 0.799).
Median progression-free survival was 378, 190, 170 and 172 days in those same groups, respectively. Although the first figure was higher, the overall comparison did not meet the study’s threshold for statistical significance (p = 0.115). That result means the records did not provide strong enough evidence to distinguish a treatment effect from chance or other differences between patients. It does not show that the treatments work equally well.
To reduce the influence of tumor mutations on the comparison, the authors also examined a subgroup they called “non-driver.” It included patients without EGFR, HER2, ALK, ROS1, MET, RET or BRAF mutations, while retaining patients with KRAS mutations and those without the listed mutations. In that exploratory analysis, progression-free survival differed significantly across the four treatment groups (p = 0.045); the denosumab-plus-immunotherapy group’s median was not reached by the analysis cutoff, compared with 225, 170 and 133 days in the other groups.
This subgroup result is a reason to investigate the possibility further, not a result that applies to every patient with lung cancer and bone metastases. The subgroup was part of a small, nonrandomized study, and the authors also reported that the apparent advantage in the separate wild-type and KRAS analyses did not reach statistical significance.
A biological rationale, not a measured explanation
Denosumab blocks RANKL, a molecule involved in the normal process of bone turnover. RANKL also interacts with immune cells, so the authors discuss a possible connection between bone-targeted treatment and the immune environment around a tumor. They describe earlier laboratory and mouse-model findings in which blocking this pathway alongside immune checkpoint treatment was associated with stronger antitumor activity.
That rationale helps explain why the clinical comparison was worth asking. This chart review measured patient outcomes—tumor response, time before progression, skeletal-related events and adverse events. It did not measure whether changes in immune cells or the RANKL pathway explained the outcomes. The proposed biological synergy therefore remains an interpretation to test, rather than a mechanism demonstrated in these patients.
Bone complications and side effects were separate outcomes
Skeletal-related events are complications involving cancer in the bones. They were recorded in 5% of patients receiving denosumab plus immunotherapy, 10.8% receiving phosphates plus immunotherapy, 13.3% receiving denosumab without immunotherapy, and 11.9% receiving phosphates without immunotherapy. The difference across groups was not statistically significant (p = 0.733).
Adverse events were reported in 27.5%, 39.2%, 26.7% and 28.6% of the respective groups, also without a significant difference (p = 0.742). These outcomes address bone complications and treatment harms, not whether tumors were controlled. With small groups and nonsignificant comparisons, the study cannot establish that the treatments provide equal bone protection or have equivalent safety. Nor does it show that denosumab prevents skeletal events better.
Why the apparent advantage needs a stronger test
Treatment assignment was not random. The authors note that physician preferences and denosumab’s higher cost could have influenced who received it. The small and uneven groups leave the estimates vulnerable to chance, while differences in tumor type and PD-L1 expression could also affect comparisons. Various immunotherapy and phosphate products were used, adding further variation.
Follow-up was limited for the denosumab-plus-immunotherapy group: the median was 198 days, shorter than its reported median progression-free survival of 378 days. The authors also did not investigate RANK or RANKL as patient biomarkers, so these records cannot identify whether either molecule could help predict who might benefit. Together, these constraints leave open whether the observed pattern reflects the combination, the patients selected for it, or both.
What this could change
A person receiving immunotherapy for lung cancer that has spread to bone already faces a choice among bone-protecting treatments. If prospective evidence eventually shows that one option also improves cancer control, clinicians could weigh that demonstrated effect alongside bone outcomes when discussing treatment choices. This study contributes an observed association from a four-group comparison; it does not prove that denosumab adds a cancer-control benefit.
A nearer milestone would be a prospective comparison that follows comparable patients long enough to report planned outcomes for progression-free survival, skeletal-related events and adverse events, including a clearly defined analysis of patients without the specified driver mutations. Any change in treatment decisions would depend on independent confirmation of a benefit and a clear accounting of its risks.
Key Sources
- Primary source: Efficacy and safety of concomitant immunotherapy and denosumab in patients with advanced non-small cell lung cancer carrying bone metastases: A retrospective chart review.
DOI or Journal Page · Peer-Reviewed Paper · 2022-08-29
Keep exploring