
Research Signal – Source date 2022-04-17
Checkpoint inhibitors—drugs that target signals controlling immune activity—are already used in several cancers of the urinary and male reproductive systems. A review published on April 17, 2022, describes these medicines as approved for use alone or alongside other treatments, with associated improvements in patient outcomes. Yet people with these cancers do not all respond in the same way, and clinicians still lack a dependable way to predict an individual response from the diagnosis alone.
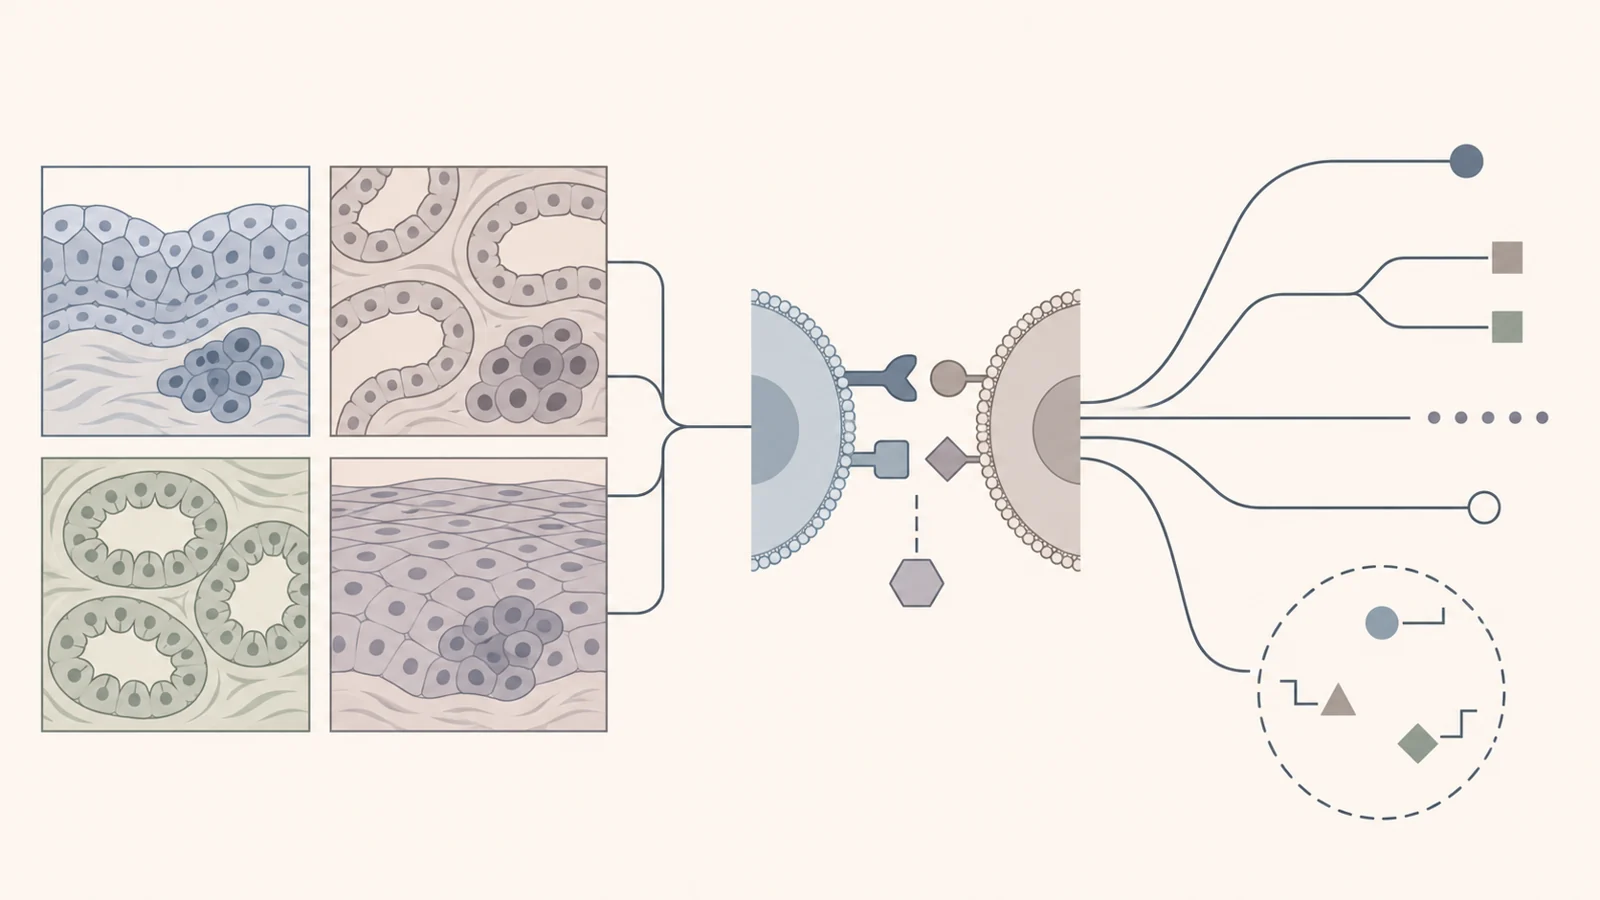
The review surveys evidence in urothelial cancer, renal cell cancer, prostate adenocarcinoma and penile squamous cell cancer. It brings together settings where the same broad drug family has a clinical role, while emphasizing that response can differ across tumors and people. Its central question is therefore not simply whether immunotherapy exists for these cancers, but why its effects vary and what might help anticipate them.
One drug family, several cancer settings
Checkpoint inhibitors act on immune control pathways. The review discusses drugs aimed at PD-1 or its partner PD-L1, as well as CTLA-4. These signals help regulate immune activity; targeting them can alter that control. The drugs may be used as monotherapies, meaning on their own, or in combinations with other agents.
The four cancer types in the review are distinct clinical contexts, not interchangeable examples of one disease. Urothelial cancer, renal cell cancer, prostate adenocarcinoma and penile squamous cell cancer differ in their tumor biology and in how they interact with the immune response. A broad label such as “genitourinary cancer” therefore cannot, by itself, tell a clinician which approach will suit a particular person. The review summarizes evidence across these settings, rather than establishing one shared treatment rule or ranking their benefits.
Why responses can diverge
The authors point to three likely contributors to different responses. Tumors vary at the molecular level. They also vary in how much they engage with the immune response. And patients bring individual factors that may shape how treatment works for them.
These influences can overlap. A medicine aimed at an immune control signal does not act in a uniform biological setting: the tumor and its relationship with immune activity matter, as do characteristics of the person receiving treatment. The review identifies these as plausible explanations for variation, while its abstract does not provide cancer-specific response estimates to quantify how much each factor contributes.
This complexity makes a predictive biomarker attractive. A biomarker is a measurable feature that could help indicate whether a treatment is more or less likely to work. If reliable, it could support a more individualized discussion about whether a checkpoint inhibitor is a reasonable option, rather than relying on the cancer category alone.
Candidate markers have not settled the choice
The review describes several candidate biomarkers for predicting response, but calls them imperfect. That leaves an important gap between finding a feature that may be associated with response and having a test that reliably guides treatment for an individual patient. The supplied review evidence does not validate a particular marker as a dependable patient-selection test.
The distinction matters in practice because a useful marker would need to predict response accurately enough to inform a real clinical decision. The review captures a field with approved drugs and growing clinical evidence, but with response prediction still under development. Its findings are a synthesis of published work, not a new treatment trial or a personalized estimate for any patient.
How this could shape the future
For someone discussing immunotherapy for a specific genitourinary cancer, a dependable prediction could make the conversation more informative than a broad diagnosis alone: clinicians might better explain the likelihood that a checkpoint drug will help that person. The review offers a starting point for that possibility—responses vary, and candidate markers remain imperfect—but realizing it would require further validation and integration into clinical care. The drugs are already in use; more dependable matching of treatment to patient is the possible advance.
A nearer milestone would be testing a candidate marker before treatment to see whether it predicts response in one cancer, then repeating that result in separate patient groups. If that result held up and proved useful in care, it could strengthen the path toward individualized treatment discussions. Until then, the review supports interest in prediction without establishing a reliable test for choosing patients.
Key Sources
- Primary source: Use of immunotherapy in clinical management of genitourinary cancers – a review.
DOI or Journal Page · Review or Meta-Analysis · 2022-04-17
Keep exploring