
Research Signal – Source date 2026-01-01
An older immune system can remain persistently inflamed while struggling to control a respiratory virus. The apparent contradiction becomes clearer when we separate the tasks involved. Clearing particles from an airway, detecting an invading virus and producing antibodies require different processes. Ongoing inflammatory activity does not guarantee that any of those processes will work well.
A narrative review, Immunosenescence and susceptibility to respiratory viruses, brings these changes together with their clinical consequences, focusing on adults aged 65 and older. Immunosenescence means the age-related decline and remodeling of immunity. Its frequent companion, inflammaging, is chronic, low-grade inflammation that can persist between infections.
The authors connect these mechanisms to an uneven landscape of practical options. Adapted influenza vaccines have comparative evidence of clinical benefit. Biomarkers that might guide individual care remain a developing prospect. Attempts to remove senescent cells have produced differing results in infected mice. Understanding those distinctions helps explain what can already improve protection and what still requires translation into human benefit.
Several defenses can falter at once
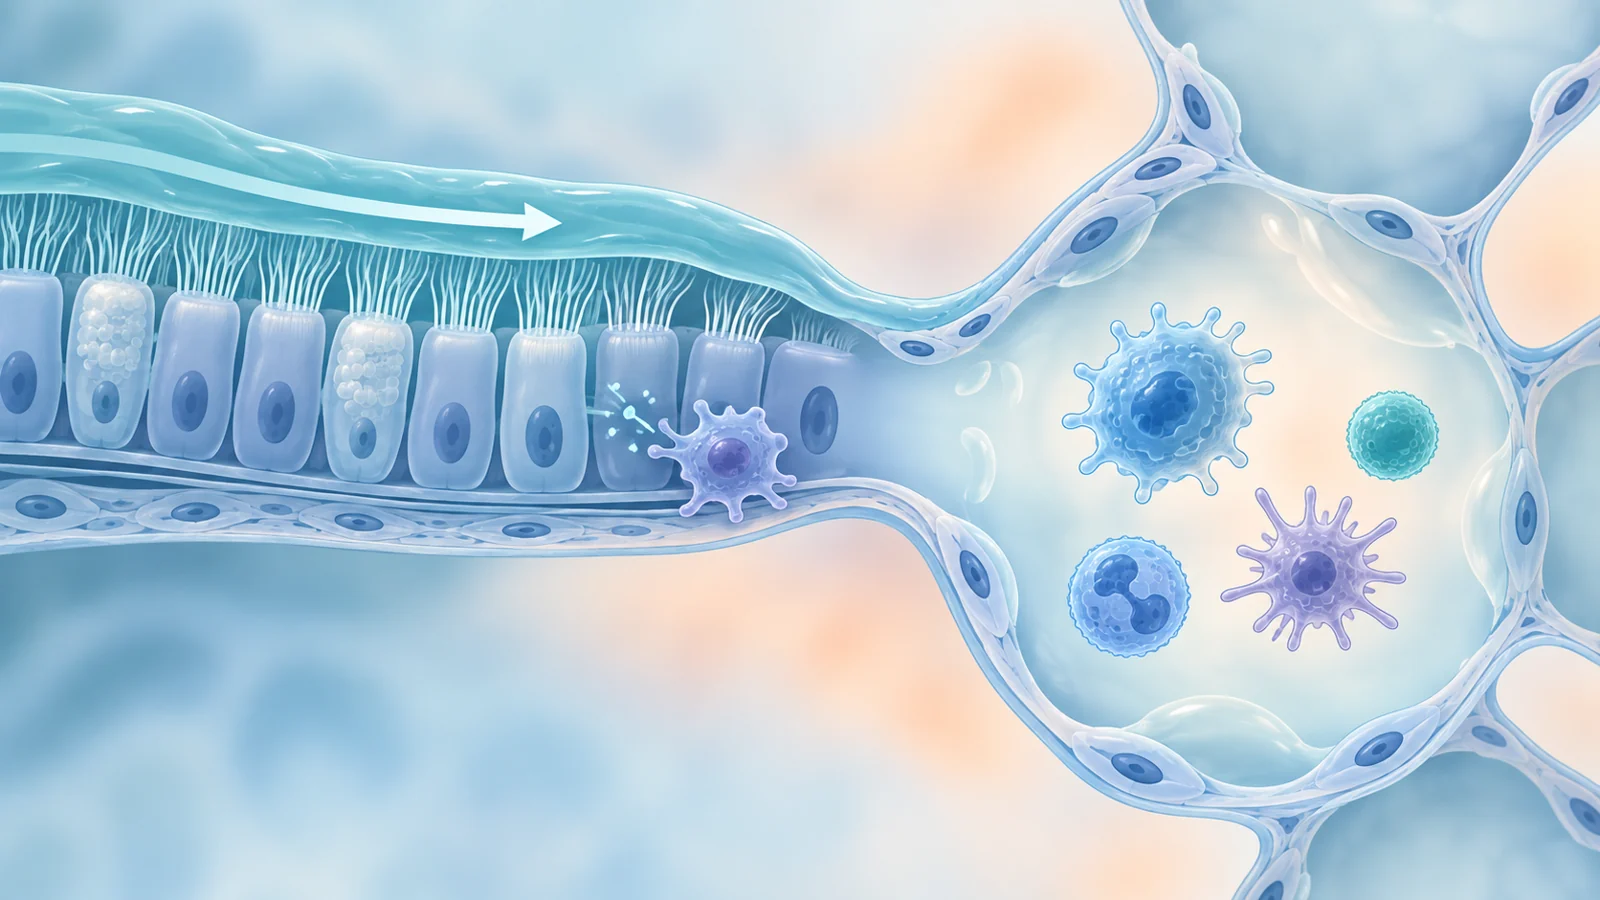
Protection begins before immune cells recognize a virus. Mucus and beating cilia—the tiny moving projections on airway cells—help carry inhaled particles out of the respiratory tract. With age, cilia can beat less efficiently, mucus clearance can decline and coughing may become less effective. Together, these changes can give infectious particles greater access to the lower airways.
The lungs themselves also change. They lose elasticity, blood flow supplying airway tissues can decrease, and tissue repair becomes less efficient. These physical changes help explain why respiratory vulnerability cannot be reduced to a single immune defect.
Once a virus reaches susceptible cells, early warning matters. Type I and type III interferons are signaling proteins involved in the initial antiviral response. The review describes evidence that these responses become blunted with age. In one mechanism it discusses, defects in virus-sensing pathways inside monocytes reduce the interferon response after detection. Other findings suggest that age-related changes in specialized dendritic cells can diminish their ability to produce type I interferon.
Recognition presents another challenge. The thymus, an organ that supports T-cell development, shrinks with age. The pool of naive T cells—cells available to respond to unfamiliar targets—declines, while the repertoire of targets T cells can recognize becomes less diverse. Some T-cell populations expand less effectively when called into action. These shifts can constrain responses to newly encountered viral threats.
B cells, which produce antibodies, also undergo changes. Processes that refine an antibody’s binding and switch the type of antibody produced can become impaired. The consequence can be a response with reduced antibody quality or quantity, contributing to slower viral clearance.
Meanwhile, inflammatory activity can remain elevated. The review discusses possible contributors including mitochondrial dysfunction, impaired disposal of damaged cellular material and the accumulation of cells that release inflammatory substances. These processes help explain how persistent inflammation can accompany failures in clearance, warning and recognition.
Their importance varies between people. Frailty, chronic disease, lung function and lifelong exposures also shape risk. Some immune changes may reflect adaptation to those exposures; the independent contribution of each change to an individual’s susceptibility remains an active research question.
Vaccine formulation can make a clinical difference
Age-related changes in immune recognition help explain why some vaccines generate weaker responses in older adults. They also provide a rationale for changing the formulation. More antigen can give the immune system a stronger stimulus, while an adjuvant can enhance the response to the antigen by supporting immune activation and presentation.
High-dose influenza vaccines offer a concrete example. The formulations discussed in the review contain four times as much hemagglutinin antigen as standard-dose vaccines. Hemagglutinin is an influenza surface protein that the immune system can learn to recognize.
A stronger measured immune response, however, is a different endpoint from fewer illnesses or hospitalizations. The review summarizes evidence addressing both. It cites a systematic review and meta-analysis in which a high-dose inactivated trivalent influenza vaccine had 15.9% relative effectiveness against influenza-like illness compared with standard-dose vaccination, with a 95% confidence interval of 4.1–26.3%. That is a relative comparison between formulations, not a 15.9-percentage-point reduction in every recipient’s chance of illness.
The authors also describe lower hospitalization rates in comparisons of high-dose with standard-dose vaccination. For influenza vaccines containing the MF59 adjuvant, the evidence they summarize indicates greater effectiveness than standard-dose inactivated vaccination and effectiveness similar to high-dose vaccination.
These findings show how an adaptation to immune aging can be assessed against outcomes people experience. They do not imply identical protection across viruses, seasons or individuals. Frailty and exposure history can influence vaccine performance alongside chronological age.
Treatment depends on timing and target
Once infection begins, the clinical problem changes over time. Early in illness, an available antiviral targets replication of the responsible virus. The review emphasizes early initiation, particularly for people at high risk of complications, as a way to limit the replication cycle and viral burden.
Severe disease may bring additional problems that reducing viral replication alone cannot resolve. Older patients can need respiratory support, treatment of secondary bacterial infections and management of cardiovascular complications. The review also describes immune-modulating treatments used in severe COVID-19, including corticosteroids and drugs targeting particular inflammatory signaling pathways.
An intervention’s usefulness depends on the pathogen, the illness stage and the process being treated. A medicine that modifies a damaging host response in one setting cannot be assumed to improve another viral infection. The varied therapies discussed in the paper should therefore be understood in their disease-specific contexts, rather than as a common regimen for an aging immune system.
For older adults, this timing problem can be compounded by atypical symptoms that delay diagnosis. Recognizing illness and coordinating care are consequently part of the challenge alongside choosing a drug.
An inflammatory marker is only part of a person’s risk
Chronological age groups people with very different reserves and vulnerabilities. A useful test would need to add information that improves an individual decision—for example, identifying who is likely to benefit from a particular preventive strategy.
The review describes numerous candidate immune and inflammatory measurements. In a systematic review of 44 studies that it cites, interleukin-6 and C-reactive protein were the markers most consistently associated with frailty. Findings involving T-cell subpopulations were less conclusive, with small samples and differences between methods limiting interpretation.
An association with frailty does not by itself show that a marker predicts the outcome of a future respiratory infection. Nor does it show which treatment will improve that outcome. Those are separate questions requiring evidence about prediction and the consequences of acting on the measurement.
The authors discuss classifying patients by patterns of immune function and developing biomarker panels to guide interventions. They also identify limited longitudinal biological data. Following people over time matters because a measurement taken during severe illness may have a different meaning from the same measurement before infection.
The synthesis itself draws on varied evidence. Its methods describe free PubMed searches through September 10, 2025, reference searching and independent screening by two authors. Included material spans human research, reviews, guidelines and relevant animal and laboratory studies. That search date describes the reported PubMed search; it does not make every finding equally mature or directly applicable to clinical care.
Removing senescent cells has to improve illness outcomes
Cellular senescence is a stable arrest of the cell-division cycle. Senescent cells can contribute to inflammatory activity, and senolytics are compounds intended to remove them. This makes senolytics relevant to immune-aging research, although cellular senescence is only one part of the broader changes affecting an older immune system.
The review places two mouse findings side by side. In a SARS-CoV-2 infection setting, reducing the burden of senescent cells improved immune responses and reduced mortality. In a separate study involving influenza in aged mice, senolytic compounds reduced immune-cell infiltration without improving infection outcomes.
That distinction matters. Changing the number of immune cells entering tissue is a biological effect; whether the animal fares better is a further question. An apparently favorable change in an inflammatory measurement cannot substitute for an improvement in illness.
The separate experiments do not establish why their results differed. They also do not establish that senolytic treatment is safe or improves respiratory infection outcomes in older humans. The review’s broader concern about older adults being underrepresented in clinical trials reinforces the need for evidence from the people an intervention is meant to help.
What this could change
A more individualized approach could connect prevention and care to the vulnerabilities that matter for a particular older person. Comparative vaccine evidence already shows that formulation can affect protection. If future biological predictors reliably identify additional differences in response—and strategies based on those predictors improve outcomes—vaccine selection and scheduling could become better matched to individual needs.
The practical benefit would extend beyond avoiding an acute infection. Respiratory illness in older adults can be followed by loss of function and greater care needs. If more effective prevention and coordinated geriatric, respiratory and infectious-disease care reduce severe episodes and complications, more people could preserve independence after illness, while hospitals face fewer admissions and demands for intensive support.
That prospect links immune biology to a concrete goal: fewer infections that interrupt an older person’s ability to live as they did before becoming ill.
Key Sources
- Primary source: Immunosenescence and susceptibility to respiratory viruses: a state-of-the-art review.
DOI or Journal Page · Peer-Reviewed Paper · 2026-01-01
Keep exploring