
Research Signal – Source date 2026-06-12
As the body ages, some cells enter senescence. They stop dividing, but they do not necessarily become inactive. Many remain metabolically active and release inflammatory and tissue-remodeling signals known as the senescence-associated secretory phenotype, or SASP. When senescent cells accumulate, those signals can contribute to chronic inflammation, fibrosis and declining tissue function.
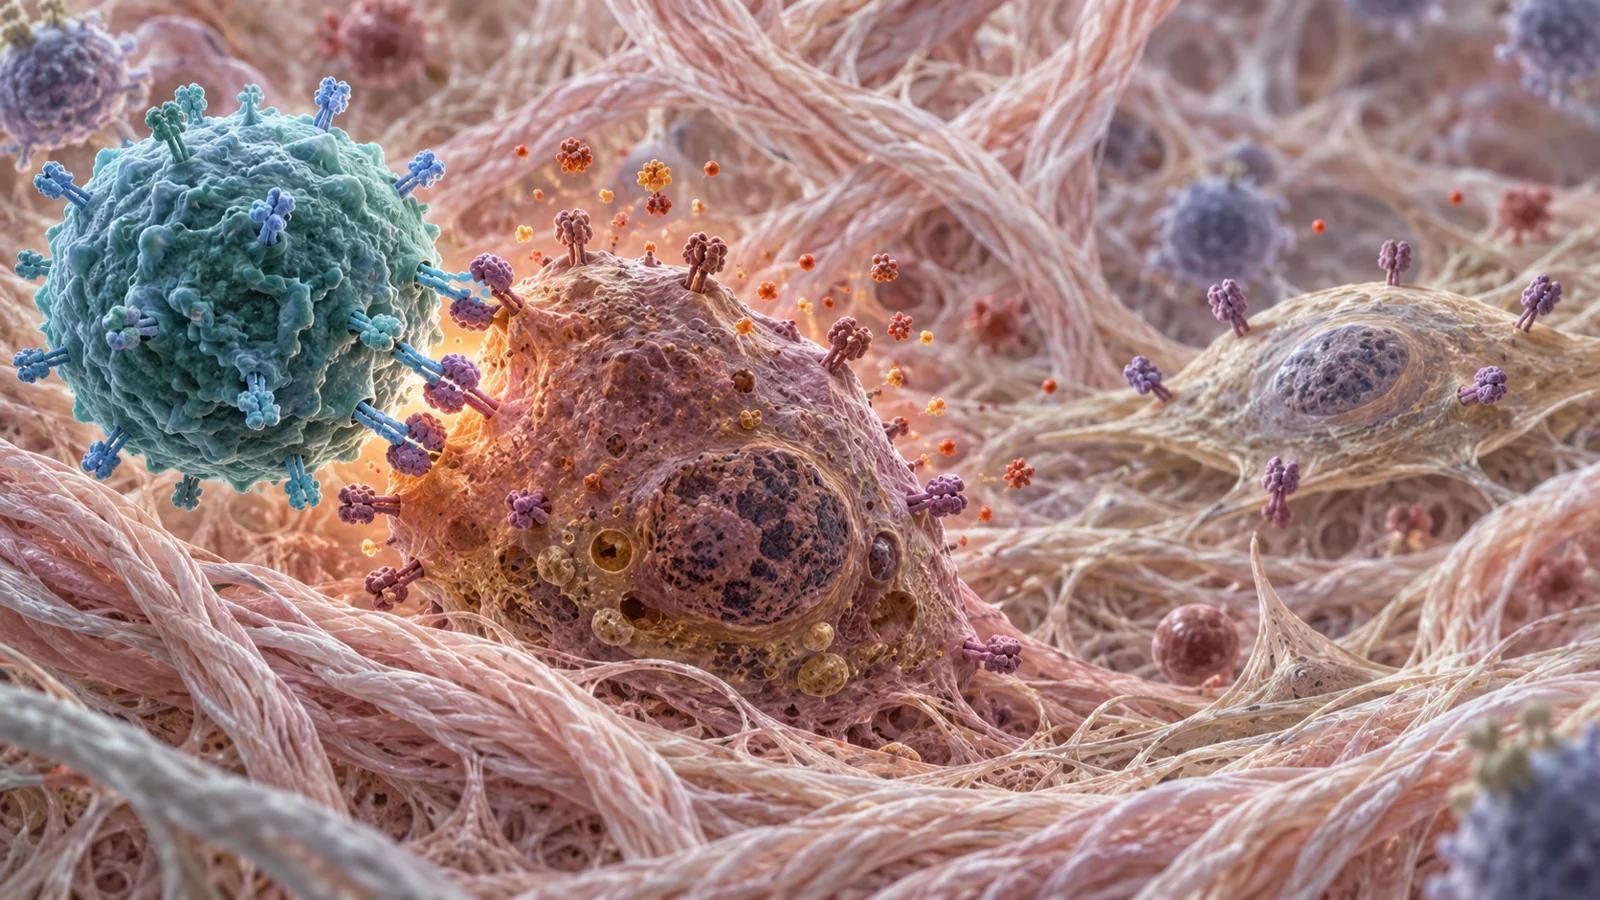
Senolytic drugs aim to clear senescent cells, including by targeting the pathways that keep them alive. The June 12, 2026 review Chimeric Antigen Receptor T Cells as Living Therapeutics Targeting Senescence and Age-Related Diseases considers a different approach: giving T cells engineered receptors that recognize surface features associated with senescent or fibrosis-producing cells.
The idea borrows from cancer immunotherapy, where chimeric antigen receptor T cells are designed to recognize a chosen marker and then activate the T cell against the cell carrying it. In aging research, the attraction is not simply stronger cell killing. It is the possibility of directing a living population of therapeutic cells toward a difficult, changing tissue problem. The evidence assembled in the review, however, remains preclinical or exploratory for senescence-directed treatment.
A living treatment starts with the right surface target
A CAR T cell is built from several linked parts. An external binding component recognizes an antigen, while hinge and membrane sections position the receptor and internal signaling domains activate the T cell. The design can be adjusted for different targets, multiple antigens or added control systems. For senescence research, the first question is therefore biological: which surface feature identifies a harmful cell closely enough to make selective clearance plausible?
The review uses urokinase-type plasminogen activator receptor, or uPAR, as one important example. Studies summarized in the paper used uPAR-directed CAR T cells to target senescent hepatic stellate cells in mouse models of liver fibrosis. In aged or high-fat-diet mouse models, the review also reports improved metabolic function after a single dose of uPAR-directed CAR T cells. These findings make uPAR interesting because the targeted cells were connected to both a specific tissue pathology and broader metabolic changes.
The target still changes the meaning of the result. uPAR is also found on some normal cells and on cells involved in repair. A uPAR-directed treatment could therefore be clearing a relevant senescent population in one setting while carrying a risk of damaging useful cells in another. The mouse findings support the possibility of targeted clearance; they do not show that every uPAR-bearing cell is senescent or that the same design would be safe in older people.
Fibroblast activation protein, or FAP, illustrates a different route. FAP is associated with activated fibroblasts and has been used to direct CAR T cells against cells that produce or sustain fibrosis. The review describes animal studies in which FAP-directed CAR T cells reduced fibrotic tissue and improved organ function. That is an important antifibrotic finding, but it is biologically distinct from proving senescence-selective clearance. Activated fibroblasts can participate in repair, and removing fibrosis-producing cells is not automatically the same as removing senescent cells.
Persistence could change the dosing equation
A conventional senolytic drug is administered, acts for a period of time and then leaves the body or loses activity. Because senescent cells can accumulate again, the review contrasts that intermittent pattern with the possibility that infused CAR T cells might remain active and continue surveillance after treatment. A surviving therapeutic cell population could, in principle, provide more sustained clearance than a short drug exposure.
That possibility is conditional on the cells. They must survive in the recipient, reach the relevant tissue, recognize the intended target and remain functional in an environment that may be inflamed, nutrient-poor or otherwise hostile. The review presents durability as a potential advantage, not a guaranteed property of a single infusion. Long-term persistence could also make an error more consequential if the receptor recognizes cells that should have been left intact.
The practical tradeoff is equally important. CAR T treatment requires individualized cell preparation, expansion, quality control and administration. The review contrasts that complex and costly process with the relative convenience of a small-molecule or biologic drug. A treatment that lasts longer may reduce repeated dosing, but it does not remove the manufacturing burden. For age-related diseases that are not immediately fatal, the balance between durability, control, cost and everyday tolerability would be central to whether the approach is useful.
The hardest problem is deciding which cells to remove
Senescence is not simply a label for cells that are always harmful. Senescent cells can contribute to tissue repair, embryonic development and immune regulation in particular contexts. Candidate markers are also imperfect. FAP can appear on fibroblasts involved in healing, uPAR can occur on normal or repairing cells, and NKG2D ligands can rise in infected, inflamed or transformed cells. Even senescence-associated beta-galactosidase can be present in cells with high lysosomal activity.
This makes the therapeutic goal more precise than clearing every cell that carries a senescence-associated signal. The receptor has to distinguish a damaging population from a temporarily useful one, and the treatment has to be controllable if that distinction fails in a particular tissue. The review discusses several engineering approaches for managing that risk.
Some designs aim to control receptor activity. The review describes drug-regulated systems, including a signal-neutralizing inhibitory protease approach, as ways to turn CAR activity down when the controlling drug is withdrawn. Other designs create a separate emergency route for eliminating the therapeutic cells themselves. Inducible caspase 9 and herpes simplex virus thymidine kinase are discussed as suicide-gene strategies that could rapidly terminate CAR T-cell activity during severe toxicity or tissue damage.
These are safety mechanisms under development, not proof that harmful clearance can always be prevented or reversed. Controlling a receptor and destroying the cells that carry it are also different interventions. A switch may reduce future activity, while a suicide gene may remove the treatment population; neither makes target selection unnecessary.
The recipient is part of the treatment
The quality of the engineered cells begins before infusion. Aging changes the T-cell population, with fewer naive cells and more memory, effector or senescent-like cells. Proliferation and secretory function can decline, and telomere shortening can limit the replicative capacity of cells collected from older donors. A CAR design that performs well in a laboratory may therefore behave differently when manufactured from an aged person’s blood.
The review discusses proposed preparation strategies intended to improve that starting material. These include selecting younger or higher-quality T-cell subsets, using interleukin-7-based culture, applying low-dose mTOR inhibition and transiently delivering telomerase reverse transcriptase mRNA. They are engineering and manufacturing options described by the review, not demonstrated clinical solutions for rejuvenating patient-derived CAR T cells.
The tissue receiving the cells presents another obstacle. Aging environments can contain inflammatory SASP signals, increased immune-checkpoint activity, low oxygen, high lactate, limited nutrients and elevated reactive oxygen species. Such conditions may weaken T-cell survival or activity after administration. The review therefore considers approaches such as adding cytokine receptors or locally releasing factors including interleukin-15 and interleukin-12 to help the cells persist and function.
Animal models cannot resolve all of these questions. Accelerated-aging mice reproduce some features of aging through an artificial process, while naturally aged mice develop only some of the complex, multisystem problems seen in older people. The review proposes combining humanized mouse systems with patient-derived senescent-cell models and using nonhuman-primate aging models for longer-term safety work. These proposals reflect the gap between observing clearance or reduced fibrosis in mice and establishing a controllable treatment for human aging-related disease.
The studies summarized in the review therefore support a carefully bounded conclusion. Engineered T cells can be designed to recognize candidate surface targets, and several animal studies link target-directed cell removal with changes in fibrosis or metabolism. Cancer treatment experience and early safety work in adjacent applications do not establish clinical benefit for senescence-directed therapy. Nor do the animal findings show that the treatment improves health, extends life or reverses aging in people.
What targeted cell clearance could change for fibrotic disease
Fibrotic disease offers a possible early setting for testing whether selective cell clearance can produce a meaningful human benefit. The review highlights conditions such as idiopathic pulmonary fibrosis as potential areas of focus because persistent fibrotic activity can damage organ function and limit daily life. If a controllable CAR T-cell treatment could remove the cells that sustain that damage while preserving cells needed for repair, the downstream goal would be better breathing, movement or other organ-specific function rather than an abstract change in an aging marker.
Reaching that outcome would require more than a positive mouse experiment. The target would need to distinguish harmful from useful cells, the engineered population would need to function in aged tissue, and clinicians would need reliable ways to stop or limit activity when necessary. The review argues that future studies should therefore measure organ function, functional capacity and patient-reported quality of life alongside biological indicators. From the June 2026 perspective, targeted living-cell therapy remains a conditional route toward preserving everyday function in fibrotic disease, not an established anti-aging treatment.
Key Sources
- Primary source: Chimeric Antigen Receptor T Cells as Living Therapeutics Targeting Senescence and Age-Related Diseases.
DOI or Journal Page · Review or Meta-Analysis · 2026-06-12
Keep exploring