
Research Signal – Source date 2022-03-02
In studies of late-stage non-small cell lung cancer, some trials found survival gains from adding immunotherapy among people with a smoking history. Several observational studies instead found longer survival among former or current smokers than among never-smokers when everyone studied had received immunotherapy. The pattern is striking, but it is not a rule for choosing treatment: the studies compared groups, and they did not establish that smoking history can predict what will happen to an individual.
A systematic review published in 2022 gathered evidence from 18 randomized trials and 16 observational studies. Its search covered research from 2013 through January 2021. The two kinds of studies approached the question differently, so their results help explain the puzzle from separate angles.
The smoking pattern appeared in two kinds of studies
In 8 of 15 randomized trials reporting smoking-stratified results, at least one survival measure favored adding immunotherapy for people who had smoked. Among 12 trials that grouped participants as ever-smokers or never-smokers, 6 found a statistically significant improvement for ever-smokers. Two of those six also found significant improvement for never-smokers. Three other trials separated current, former, and never-smokers; two reported significant gains for former smokers, while neither found a significant difference for current or never-smokers.
Observational studies showed a related pattern among people who all received immunotherapy. Of 13 studies reporting results by smoking status, 8 found a statistically significant survival difference. Seven found that current or former smokers lived longer or had more time before their cancer worsened than never-smokers. One small study of patients receiving a particular combination treatment found the reverse pattern for progression-free survival.
These counts are not a pooled estimate of how much benefit smoking history adds. The studies used different treatments, patient groups, and outcome analyses, and the review could not combine them in a meta-analysis. The counts describe how often individual studies reported statistically significant results, not the size or consistency of a single overall effect.
Treatment benefit and survival among treated patients are different questions
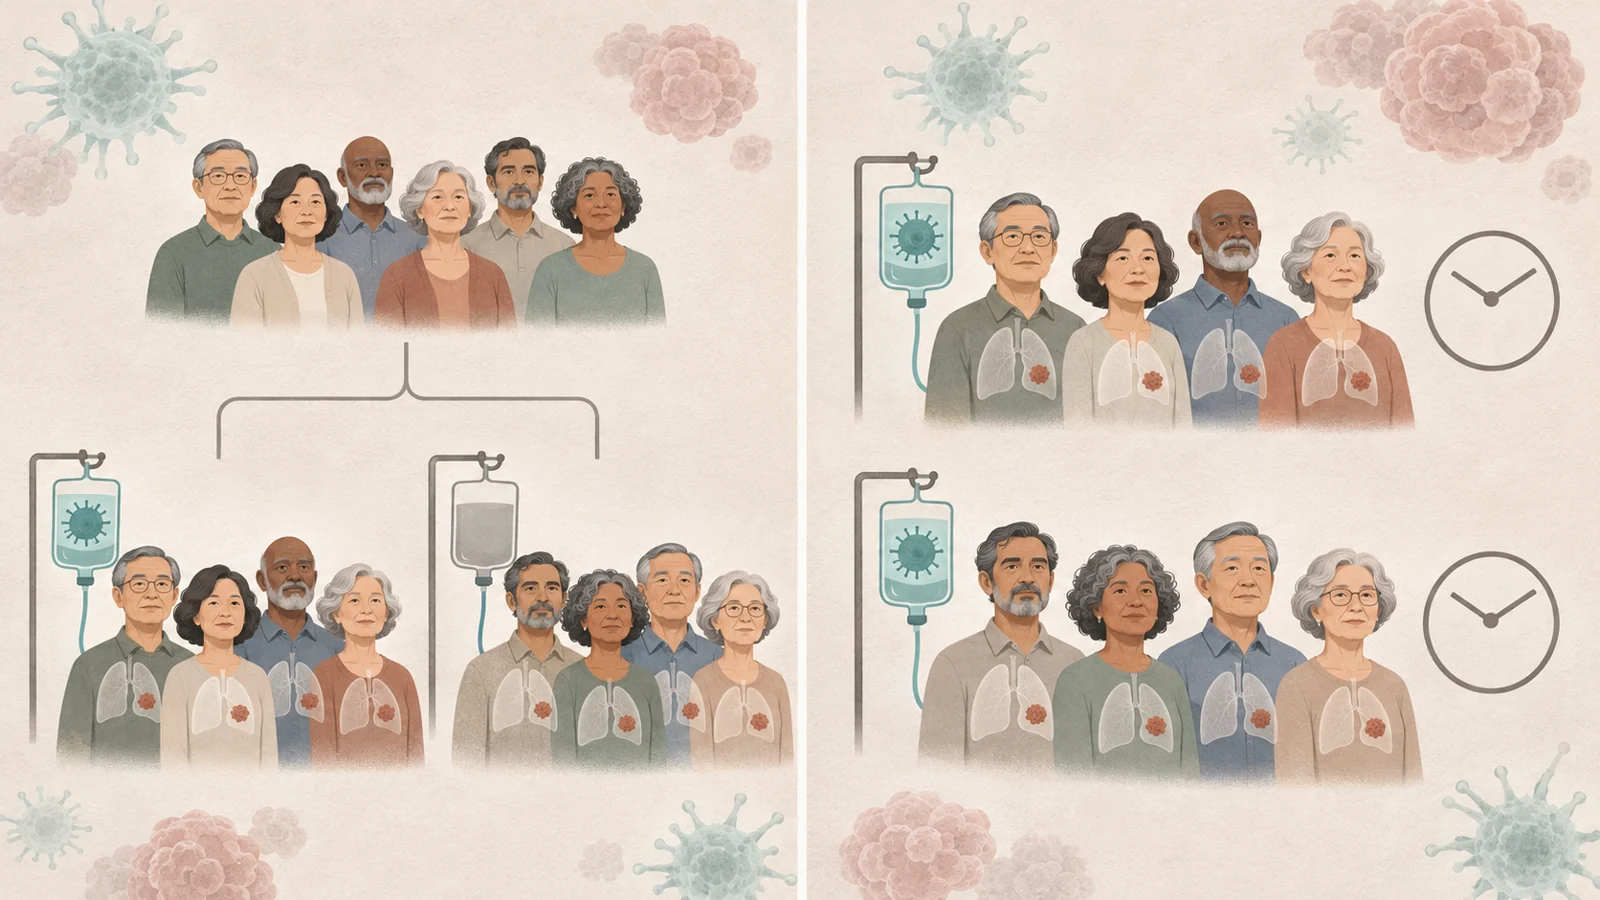
A randomized trial can compare a group offered immunotherapy with a control group that receives another treatment or treatment approach. If the immunotherapy group does better within a smoking subgroup, the result suggests a benefit from adding immunotherapy in that trial and subgroup. Overall survival measures time until death from any cause; progression-free survival measures time until the cancer worsens or another defined event occurs. A hazard ratio summarizes how those events compare over time between groups.
An observational study of immunotherapy recipients asks something else: among patients who all received immunotherapy, did one subgroup have longer survival than another? That comparison does not show whether immunotherapy itself caused the difference. Age, health, disease features, treatment line, and other factors may differ between groups, and each study adjusted for a different set of factors—or did not report those adjustments consistently.
For example, a trial might find that adding immunotherapy improves outcomes for ever-smokers compared with its control group. An observational study might find longer survival for former and current smokers than for never-smokers among people receiving immunotherapy. The first compares treatment strategies within a subgroup; the second compares patient subgroups after treatment. Both can be informative, but they cannot be read as the same estimate of treatment benefit.
A possible biological explanation remains a hypothesis
The review’s authors suggested one possible reason for the smoking pattern: tumors in people with a smoking history may carry more mutations. Some mutations can make tumor cells easier for the immune system to recognize, potentially giving immune-based treatment more targets to act on. The review cited prior research to motivate this explanation, but it did not test the mechanism in the studies it summarized. Smoking history is also a rough proxy for tumor biology, not a measurement of the features of any one person’s cancer.
The pattern had meaningful exceptions. Two trials of combination treatment reported statistically significant survival improvement among never-smokers: KEYNOTE-189 evaluated pembrolizumab with pemetrexed, and PACIFIC evaluated durvalumab with chemoradiotherapy. These exceptions make it unsafe to assume the same smoking-related pattern across treatment regimens. A subgroup pattern seen across some studies should not be assumed to hold for every drug or combination.
Age results depended on how the question was asked
Age illustrates the difference between the two study designs. Among 17 randomized trials reporting age-stratified results, 10 found a statistically significant overall- or progression-free-survival improvement with immunotherapy for patients younger than 65. In trials that divided participants into younger and older groups, significant gains appeared more often among those under 65 than among those 65 and older.
Yet observational comparisons among immunotherapy recipients usually did not find a significant survival difference by age. Only 4 of 13 such studies found better survival for younger patients. A younger patient group can have a different baseline outlook from an older one, while the trial comparison asks whether adding immunotherapy improves outcomes relative to a control within each age group. Those are not interchangeable findings.
The review also found no statistically significant trial improvement for patients older than 75 in the studies that reported that subgroup. That absence is not proof that immunotherapy offers no benefit to older patients. Subgroup analyses can be less precise when fewer people are included, and a result that does not cross a statistical threshold cannot by itself show that the treatment effect is zero.
Sex results differed across studies
In 17 randomized trials reporting results by sex, 10 found a statistically significant survival improvement for men and 6 for women. Those totals can sound like a broad difference, but nearly every trial’s estimate for men pointed toward improvement, while results for women were less consistent. The trials were testing different treatments, and a count of significant findings does not establish that sex changes immunotherapy’s effect.
KEYNOTE-189 is one example of why the regimen deserves attention: it tested pembrolizumab with pemetrexed and reported a particularly strong survival result for women in that trial. Other trials found significant gains for women with different combinations, including atezolizumab with carboplatin and durvalumab with chemoradiotherapy. These individual results are reasons to examine treatment context, not grounds to generalize a specific combination’s outcome to all patients.
Among observational studies, 12 of 14 found no statistically significant survival difference between men and women receiving immunotherapy. The largest study did find longer survival among women. Overall, the trial and observational results do not resolve whether sex modifies treatment benefit, and the review noted that studies used inconsistent methods for adjusting their comparisons.
Race comparisons were too sparse for a clear answer
Only 5 randomized trials reported survival results by race, and just 3 observational studies examined race among immunotherapy recipients. In the trials, one study found a statistically significant improvement with immunotherapy; reported benefits for Asian and White participants were similar in size, though only the result for White participants reached statistical significance. The observational results were mixed.
Small and unrepresentative subgroup samples limit what those comparisons can tell us. The review noted that non-White patients were underrepresented in the trials that reported race, and some studies grouped everyone who was not White into a single category. That leaves too little detail and statistical power to draw a dependable comparison of treatment benefit across racial groups. Better representation and clearer reporting would improve the evidence itself.
What this could change
For someone with advanced lung cancer and their oncologist, the longer-term possibility is more dependable evidence about which immunotherapy regimen works best across patient and tumor characteristics. That could make treatment choices more closely matched to the biology of a cancer and the person receiving care, rather than relying on a broad clue such as smoking history. Immunotherapy is already used in this setting; the potential advance is more reliable matching, built on evidence that separates treatment benefit from differences in survival among patients who were treated.
Getting there depends on further trials, inclusive recruitment, and more consistent analysis. One observable step would be studies that prespecify and adequately power comparisons of treatment benefit across characteristics such as smoking status and race, while reporting treatment regimens and adjustment methods in ways that can be compared. Such evidence could show whether the patterns in this review hold across specific treatments and patient groups—and make future decisions less dependent on uncertain subgroup signals.
Key Sources
- Primary source: Association of Personal Characteristics and Effectiveness of Immunotherapy in Late-Stage Non-Small Cell Lung Cancer: A Systematic Review.
DOI or Journal Page · Review or Meta-Analysis · 2022-03-02
Keep exploring